
Kyphoplasty vs Vertebroplasty: What Is the Difference and Which Do You Need?
Kyphoplasty and vertebroplasty are both minimally invasive procedures. In each one, bone cement is injected into a fractured vertebra to relieve pain and make the bone stable. The main difference is the balloon. In kyphoplasty, a small balloon is used to restore some of the lost height of the vertebra before the cement goes in. In vertebroplasty, the cement is injected directly. Your surgeon or spine specialist decides which is best, based on scans of your fracture.
Key points
- Both procedures treat vertebral compression fractures by injecting bone cement into the broken vertebra.
- Balloon kyphoplasty first inflates a small balloon to try to restore height, then fills the space with cement.
- Vertebroplasty injects the cement directly, with no balloon step.
- Accurate scans of your spinal alignment before the procedure, ideally taken while you are standing, help your specialist plan the best approach.
- ScanAlign does not perform either procedure. We provide the standing whole-body scan that helps guide your specialist's decision.
What are kyphoplasty and vertebroplasty?
Both are minimally invasive procedures used to treat vertebral compression fractures. These are small breaks in the bones of your spine. They are most common in people with osteoporosis. They can also be caused by an injury or, less often, by tumours affecting the bone.
When a vertebra collapses, it can cause severe back pain, loss of height and a rounded upper back (sometimes called a dowager's hump). If the pain does not get better with rest, painkillers and a back brace, a specialist may suggest one of these cement procedures.
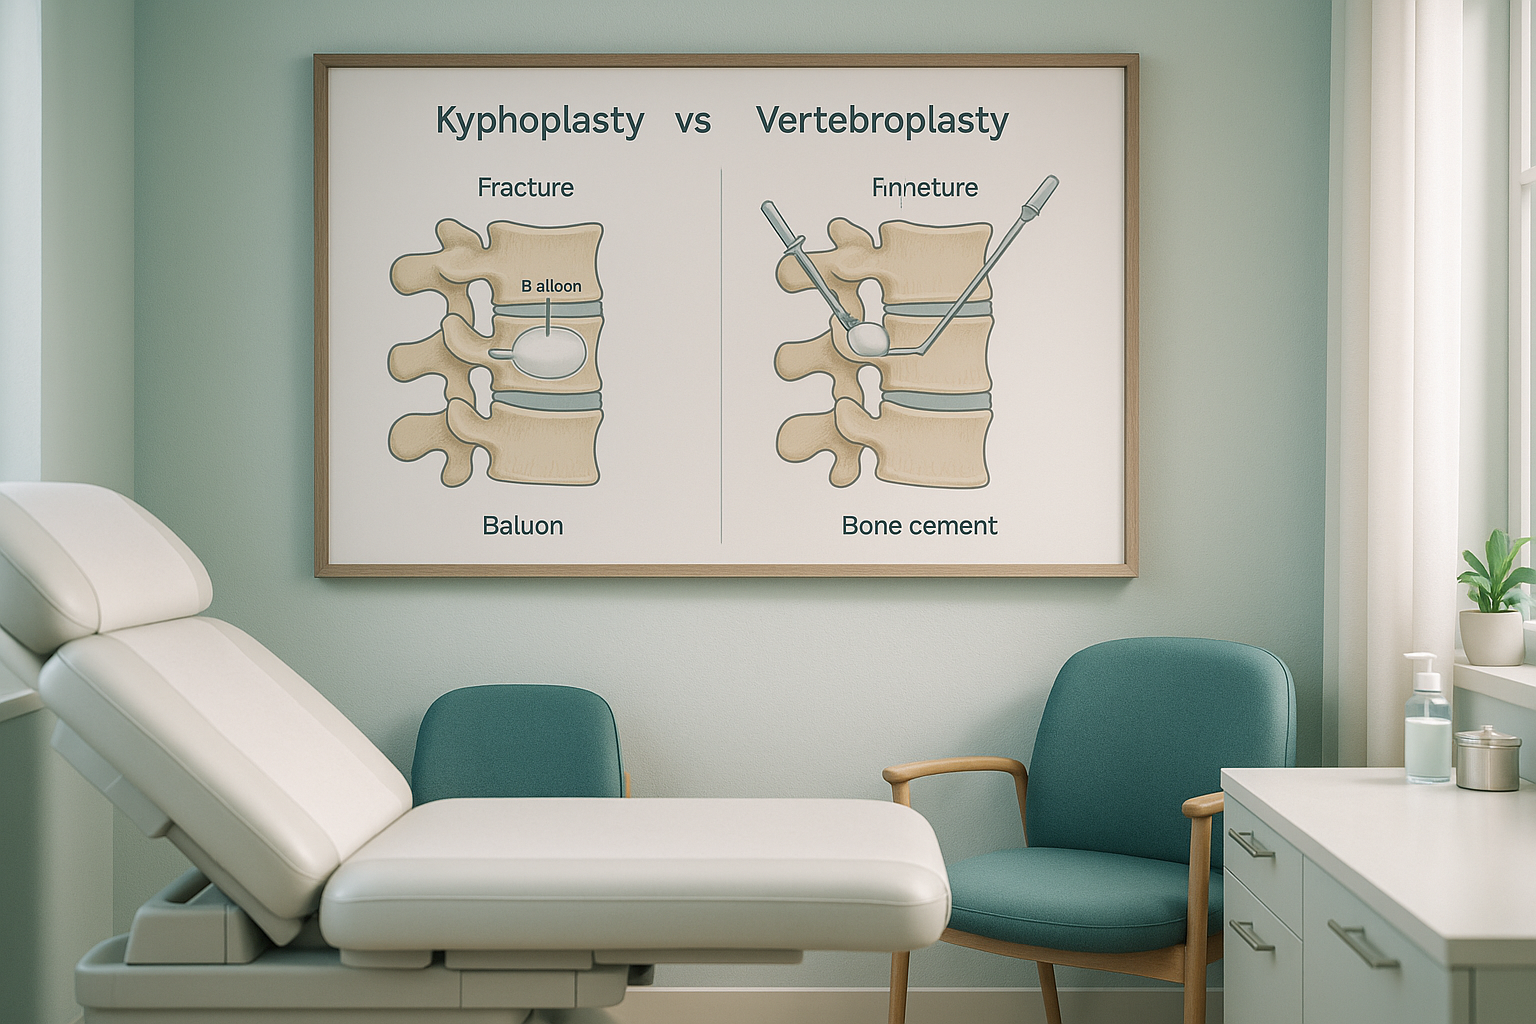
What is the difference between kyphoplasty and vertebroplasty?
The main difference is the balloon step. In vertebroplasty, bone cement is injected straight into the fracture through a needle. In balloon kyphoplasty, a small balloon is put in first. The balloon is gently inflated to make a space and lift the collapsed bone back towards its original height. Then the balloon is taken out and the space is filled with cement.
| Feature | Vertebroplasty | Balloon kyphoplasty |
|---|---|---|
| Balloon step | No | Yes, inflated to restore height |
| Restoring height | Limited | May partly restore the height of the vertebra |
| Risk of cement leaking | Slightly higher | Slightly lower (the space is made first) |
| Procedure time | Generally shorter | Slightly longer |
| Anaesthesia | Local or light sedation | Local or light sedation (sometimes general) |
| Pain relief | Often quick | Often quick |
Both procedures are usually done as a day case or with a short overnight stay. Recovery is usually quick. Most people can walk the same day and go back to light activities within a few days. Your specialist will give you advice for your own case.
Which procedure is better for you depends on several things. These include how old the fracture is, how much height has been lost, and the overall alignment of your spine. That last point, alignment, is where the quality of your scans before the procedure really matters.
How do you know if you have a vertebral compression fracture?
A vertebral compression fracture can happen suddenly or come on slowly. Some people feel a sharp pain after a minor fall, or even just from bending forward. Others notice a slow ache in the middle or lower back that keeps getting worse. Here are the most common signs.
A sharp pain in the middle or lower back that starts after bending, lifting or a minor fall.
You seem to be getting shorter over time, or your clothes fit differently.
A visible curve or hump forming in the upper spine, sometimes called a kyphotic curve.
Discomfort that gets worse when your spine carries your weight as you stand or walk, and eases when you lie down.
A note on soft-tissue scans. EOS shows bones, joints and alignment clearly. If your specialist needs to check for nerve compression, disc problems or soft-tissue damage around the fracture, MRI is usually the better tool. The two types of scan work well together.
Urgent symptoms. If you develop sudden numbness or weakness in your legs, or lose control of your bladder or bowels, get urgent medical help immediately. Contact your doctor, call your local emergency number, or go to the nearest emergency department. These symptoms can mean pressure on the spinal cord and need emergency assessment.
Why does a standing scan matter before a fracture procedure?
A standing scan gives your specialist a true picture of how your spine behaves under your own body weight. This matters because lying-down scans can hide the real extent of a compression fracture.
When you lie flat for a standard X-ray, CT or MRI, gravity is no longer pressing down through your spine. Your muscles relax, and a partly collapsed vertebra may look more intact than it really is. When you stand, the fracture carries load. The collapse becomes clearer, and its effect on your overall spinal alignment can be measured properly.
Your spine is a connected chain from your head to your pelvis. A single collapsed vertebra changes the curve above and below it. Your body makes up for it by shifting weight, tilting the pelvis or rounding the upper back further. These changes can cause pain in areas far from the fracture itself. A whole-body standing scan captures all of this in a single view.
EOS imaging does this with about 90% less radiation than a standard X-ray, around ten times less. You stand naturally during the scan, so the image shows your real, everyday alignment. This gives your surgeon the information needed to decide whether kyphoplasty or vertebroplasty is the right choice, and to plan the procedure accurately.
Before you start a treatment, or change the one you are on, it is worth getting a detailed diagnosis. Knowing whether the cause sits in the pelvis, the legs or the spine changes what will actually help.
If you have been told you have a compression fracture and want a clear picture of your whole spinal alignment before seeing a specialist, a standing EOS scan at our London clinic can help.
Book a free video consultationFrequently asked questions
Neither is better for everyone. Balloon kyphoplasty may be preferred when there is a chance to restore the height of the vertebra. Vertebroplasty may suit older or more stable fractures. Your spine specialist decides based on your scans and clinical assessment.
Most people are up and walking the same day. Light activities can usually start again within a few days. Full recovery varies, but many people feel significant pain relief within the first week. Your specialist will give you advice for your own case.
The cement used (polymethylmethacrylate, or PMMA) has been used in orthopaedic surgery for decades. There is a small risk of the cement leaking. This is why accurate scans before the procedure are important, so the needle placement can be planned carefully.
Yes. EOS produces high-quality standing images of the whole spine, so compression fractures can be seen in the context of your overall alignment. It shows how the fracture affects the curves above and below it.
No. ScanAlign is a private, self-pay clinic. You can refer yourself and book directly, without a letter from your doctor. We always recommend sharing your results with your doctor or specialist afterwards.
The price for patients travelling from abroad is confirmed during the free video consultation. You can also visit our FAQs page.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. It is one of the lowest-dose skeletal imaging systems available.
When you lie flat, gravity is taken out of the picture. A partly collapsed vertebra may look more intact because it is not carrying weight. A standing scan shows the fracture as it really behaves in your normal daily life.
No. ScanAlign is a diagnostic imaging clinic only. We provide the standing EOS scan that helps your surgeon or spine specialist plan the right procedure for you.
You stand still inside the EOS system for about 15 to 20 seconds while it scans. There is no closed tunnel and no loud noise. You can learn more about the process on our EOS scan overview page.
Get the full picture before your procedure
A standing whole-body EOS scan shows your specialist exactly how a compression fracture is affecting your spinal alignment. This helps them plan the best approach for you.
Book a free video consultationWant to learn more about how standing scans work for spine conditions? Visit our spine imaging page.
Author: Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- National Institute for Health and Care Excellence (NICE). Percutaneous vertebroplasty and percutaneous balloon kyphoplasty for treating osteoporotic vertebral compression fractures. Technology Appraisal Guidance TA279, 2013.
- Defined Procedure Guidance. Interventional procedures guidance: balloon kyphoplasty for vertebral compression fractures (IPG166). NICE, 2006 (reviewed 2012).
- NHS. Vertebral compression fractures and osteoporosis. NHS Inform / NHS UK guidance on spinal fractures.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.