
How Is a Child's Hip Monitored in Cerebral Palsy?
Hip surveillance in cerebral palsy uses regular X-rays to track whether the hip is gradually moving out of its socket. A measurement called the migration percentage tells the specialist team how much the hip has shifted. Catching displacement early gives the team time to act before pain or joint damage develops.
Key takeaways
- Children with cerebral palsy have a high risk of hip displacement, especially at higher GMFCS levels.
- Hip surveillance is a structured programme of repeat X-rays, typically starting in early childhood.
- The migration percentage is the main measure used to track hip position over time.
- EOS imaging uses about 90% less radiation than a standard X-ray, around ten times less, which matters when scans are repeated over years.
- ScanAlign supports ambulant children who can stand briefly. Non-ambulant children usually need supine imaging at their specialist centre.
What is hip surveillance in cerebral palsy?
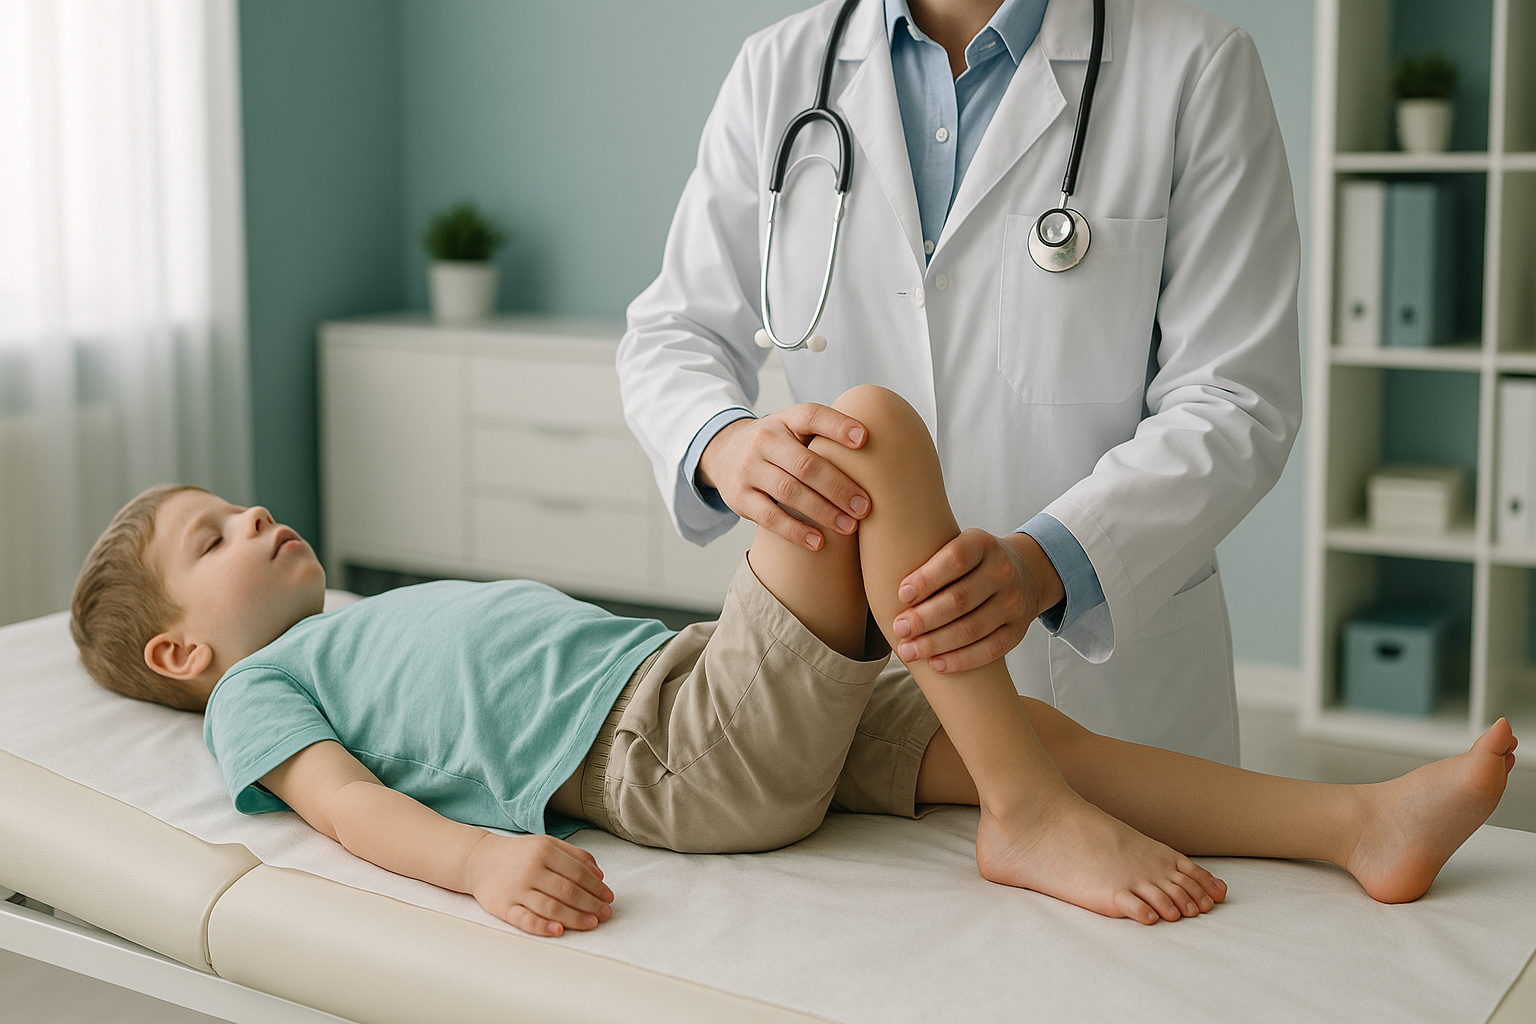
Hip surveillance is a planned programme of regular clinical examinations and X-rays designed to detect hip displacement early. In cerebral palsy, the muscles around the hip joint can pull unevenly because of differences in tone and spasticity. Over time, this imbalance can gradually draw the ball of the thighbone out of its socket.
The programme is led by your child's specialist team, which typically includes a paediatric orthopaedic surgeon, a physiotherapist and a paediatrician. X-rays are taken at set intervals and compared over time, so even very slow changes are spotted before they cause pain, stiffness or loss of function.

Hip displacement in cerebral palsy is not usually caused by an injury. It happens gradually, which is why ongoing surveillance is so important. Related hip conditions in children, such as developmental dysplasia of the hip, also benefit from early detection, though the underlying causes differ.
Why does GMFCS level affect hip displacement risk?
The Gross Motor Function Classification System (GMFCS) grades how independently a child can move, from Level I (walks without restrictions) to Level V (transported in a wheelchair). Children at higher GMFCS levels have greater muscle imbalance around the hip and spend less time weight-bearing, which increases the chance of hip displacement.
Walks independently. Lower risk, but surveillance is still recommended.
Walks with a hand-held aid. Moderate risk of displacement.
Uses wheelchair. Highest risk. More frequent imaging recommended.
Research shows that up to 90% of children at GMFCS Level V develop some degree of hip displacement. Even children who walk independently can be affected, which is why surveillance covers all GMFCS levels, just at different intervals.
What are the signs of hip displacement in cerebral palsy?
Hip displacement often begins without obvious symptoms. By the time pain appears, the hip may already have shifted significantly. That is why imaging is used rather than waiting for symptoms alone.
Discomfort during nappy changes, transfers or sitting that cannot be explained by other causes.
Difficulty spreading the legs apart, or legs that feel stiffer on one side.
Trouble sitting evenly, or a tendency to lean to one side in the wheelchair or chair.
One leg appearing shorter than the other when the child is lying down.
Children with cerebral palsy may also develop scoliosis (a sideways curve in the spine), which can interact with pelvic position and hip alignment. The specialist team monitors both together.
How is hip displacement measured on an X-ray?
The main measurement is the migration percentage. This describes how much of the ball of the thighbone sits outside the edge of the hip socket. A higher percentage means more displacement. The specialist team tracks this number from scan to scan, looking for any trend of increase.
The X-ray is taken with the child positioned in a standardised way so that each image can be fairly compared with the last. Consistency in positioning matters, because even a small change in how the child lies or sits can affect the measurement.
If the migration percentage rises past a certain threshold, the team may discuss further options. These could include changes to physiotherapy, seating, splinting or, in some cases, surgery. ScanAlign does not provide treatment, but the imaging can form part of the information the specialist team needs.
Thinking about your child's next monitoring scan? Our team can discuss whether paediatric imaging at ScanAlign might suit your child's needs.
Book a free video consultationWhy does radiation dose matter when scans are repeated over years?
Because hip surveillance involves regular X-rays, often every six to twelve months over many years, the total (cumulative) radiation dose adds up. Reducing the dose per scan matters. EOS imaging uses about 90% less radiation than a standard X-ray, around ten times less. Over a childhood of monitoring, that difference becomes significant.
Can all children be scanned standing up?
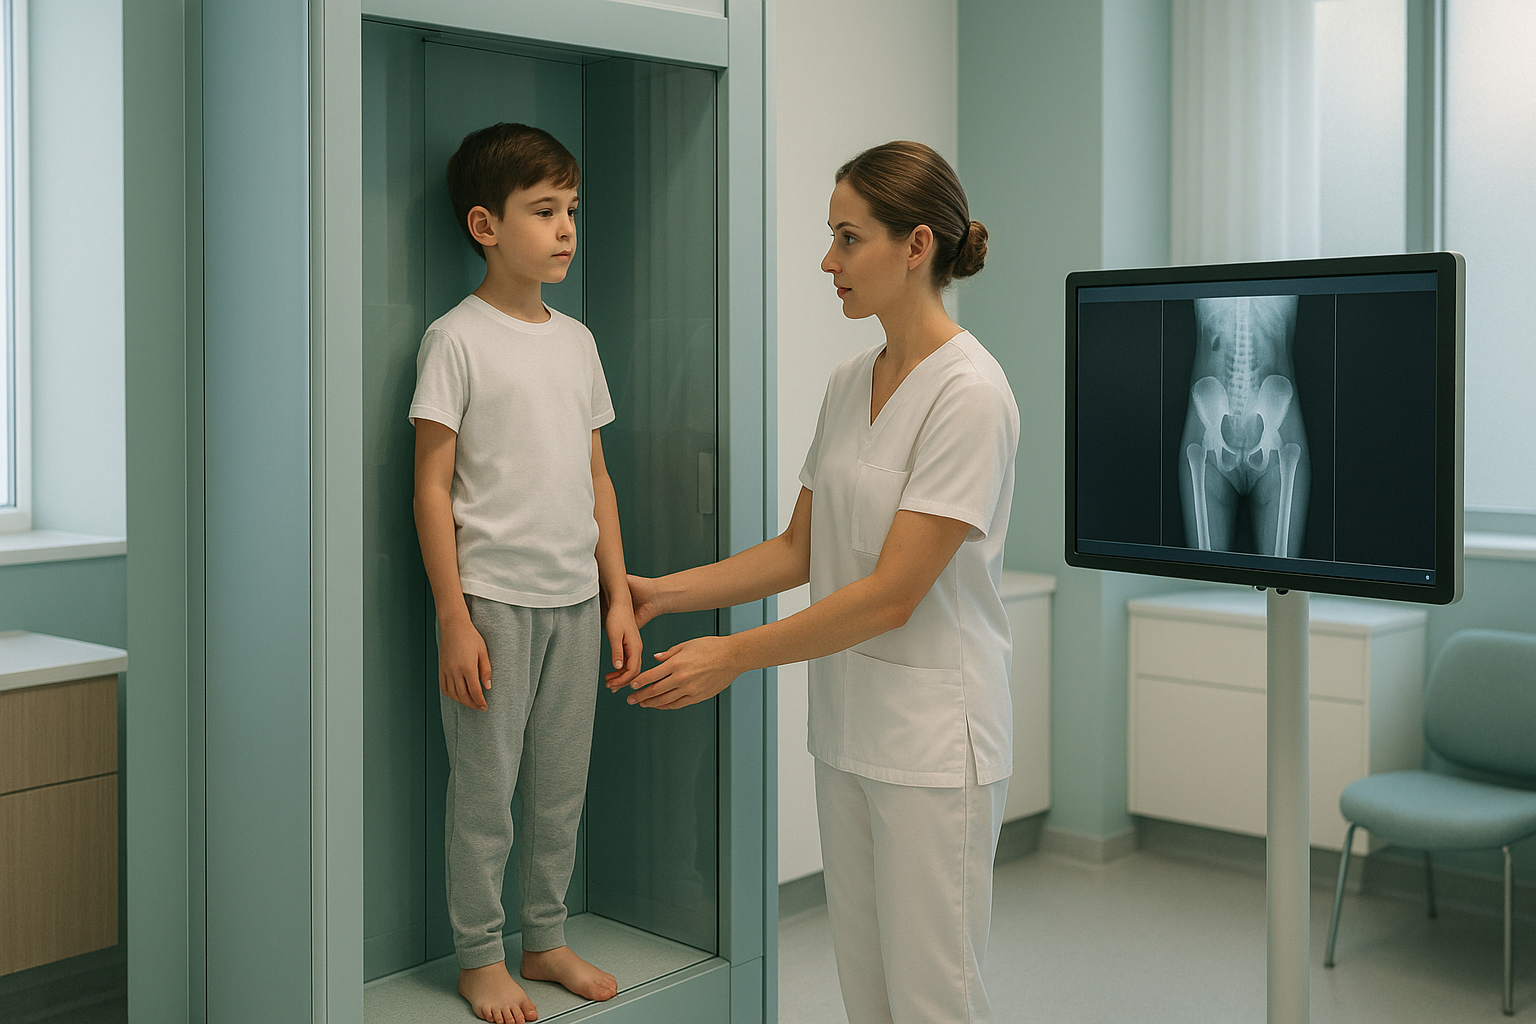
EOS captures images while the person stands upright, which shows how joints and the spine align under the body's own weight. For children at GMFCS Levels I, II and sometimes III, who can stand briefly with support, this can provide valuable information.
However, many children with cerebral palsy cannot stand. Children at GMFCS Levels IV and V, and some at Level III, usually need supine (lying-down) imaging. This is typically done at the child's specialist hospital. ScanAlign, low dose standing imaging, is best suited to ambulant or supported-standing children. During your free video consultation, we will discuss honestly whether our setup is right for your child.
When is MRI more appropriate? EOS shows bones, joints and alignment clearly. For soft tissue, muscles, nerves or the spinal cord, MRI is usually the better tool. Your child's specialist team will decide which imaging is needed at each stage.
What the scan experience is like for a child
The scan itself takes only a few seconds. A parent or carer can stay in the room throughout. The machine is open, not a tunnel, so it tends to be less stressful than other types of imaging. There is no noise and no need to hold still for a long time.
Frequently asked questions
It is a planned programme of regular X-rays and clinical checks to track whether the hip is gradually displacing from its socket. The aim is to catch any change early, before pain or joint damage occurs.
The migration percentage describes how much of the ball of the thighbone sits outside the hip socket on an X-ray. A rising percentage over time suggests the hip is gradually displacing.
The interval depends on your child's GMFCS level and previous results. It is typically every six to twelve months, but your specialist team sets the schedule.
Not always, especially in the early stages. Many children have significant displacement before any pain is noticed, which is exactly why regular imaging is important.
Our EOS system images people in an upright position. Children who can stand briefly, even with support, may be suitable. Children who cannot stand at all usually need supine imaging at their specialist hospital. We discuss this openly in the free video consultation.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. For children who need repeat imaging over many years, this helps keep the cumulative dose low.
No. You can self-refer. However, hip surveillance is usually coordinated by your child's specialist team, so we recommend discussing it with them. We are happy to share our images and reports with your team.
Yes. A parent or carer is welcome in the room throughout the scan. The system is open, not enclosed, and the scan takes only a few seconds.
It can. Children with cerebral palsy may develop scoliosis, a sideways curve in the spine. The specialist team often monitors the spine and hips together because they affect each other.
For information on pricing, please visit our book a monitoring scan page or start with a free video consultation to discuss what your child needs.
Not sure if ScanAlign is right for your child?
Our free video consultation lets you speak with a specialist radiographer who will discuss your child's needs honestly, including whether standing imaging is suitable.
Book a free video consultationWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- Wynter M, et al. "Australian hip surveillance guidelines for children with cerebral palsy." Journal of Pediatric Rehabilitation Medicine, 2014.
- Hägglund G, et al. "Prevention of dislocation of the hip in children with cerebral palsy: 20-year results of a population-based prevention programme." The Bone & Joint Journal, 2005.
- National Institute for Health and Care Excellence (NICE). Cerebral palsy in under 25s: assessment and management (NG62), 2017.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.