
Growth Plate Injury: What Causes It, and Can It Lead to Deformity?
A growth plate injury happens when the soft, developing cartilage near the end of a child's bone is damaged, usually by a fracture. Most heal well. However, if the growth plate is permanently disrupted, the bone may grow unevenly, causing angular deformity or a leg length discrepancy. Long-term monitoring is what catches these problems early.
Key takeaways
- Growth plates (physes) are the weakest part of a growing skeleton and the most vulnerable to fracture.
- Most growth plate fractures heal without lasting problems, but a small proportion lead to physeal arrest.
- Physeal arrest can cause one limb to grow shorter or at an angle compared to the other.
- Regular standing imaging over the years of remaining growth is the only reliable way to spot these changes early.
- Low-dose EOS imaging is well suited to repeated follow-up because it uses about 90% less radiation than a standard X-ray.
What is a growth plate, and why does it matter?
A growth plate, also called a physis, is a layer of cartilage near each end of a child's long bones. It is the area where new bone forms, allowing the limb to lengthen as the child grows. Because the physis is made of softer cartilage rather than solid bone, it is structurally weaker than the surrounding ligaments and bone. That makes it the part most likely to give way under force.
Once a child finishes growing, the growth plates harden into solid bone and are no longer at risk. Until then, any injury to a physis has the potential to disrupt how that bone continues to develop.
What are the long-term signs of growth plate damage?
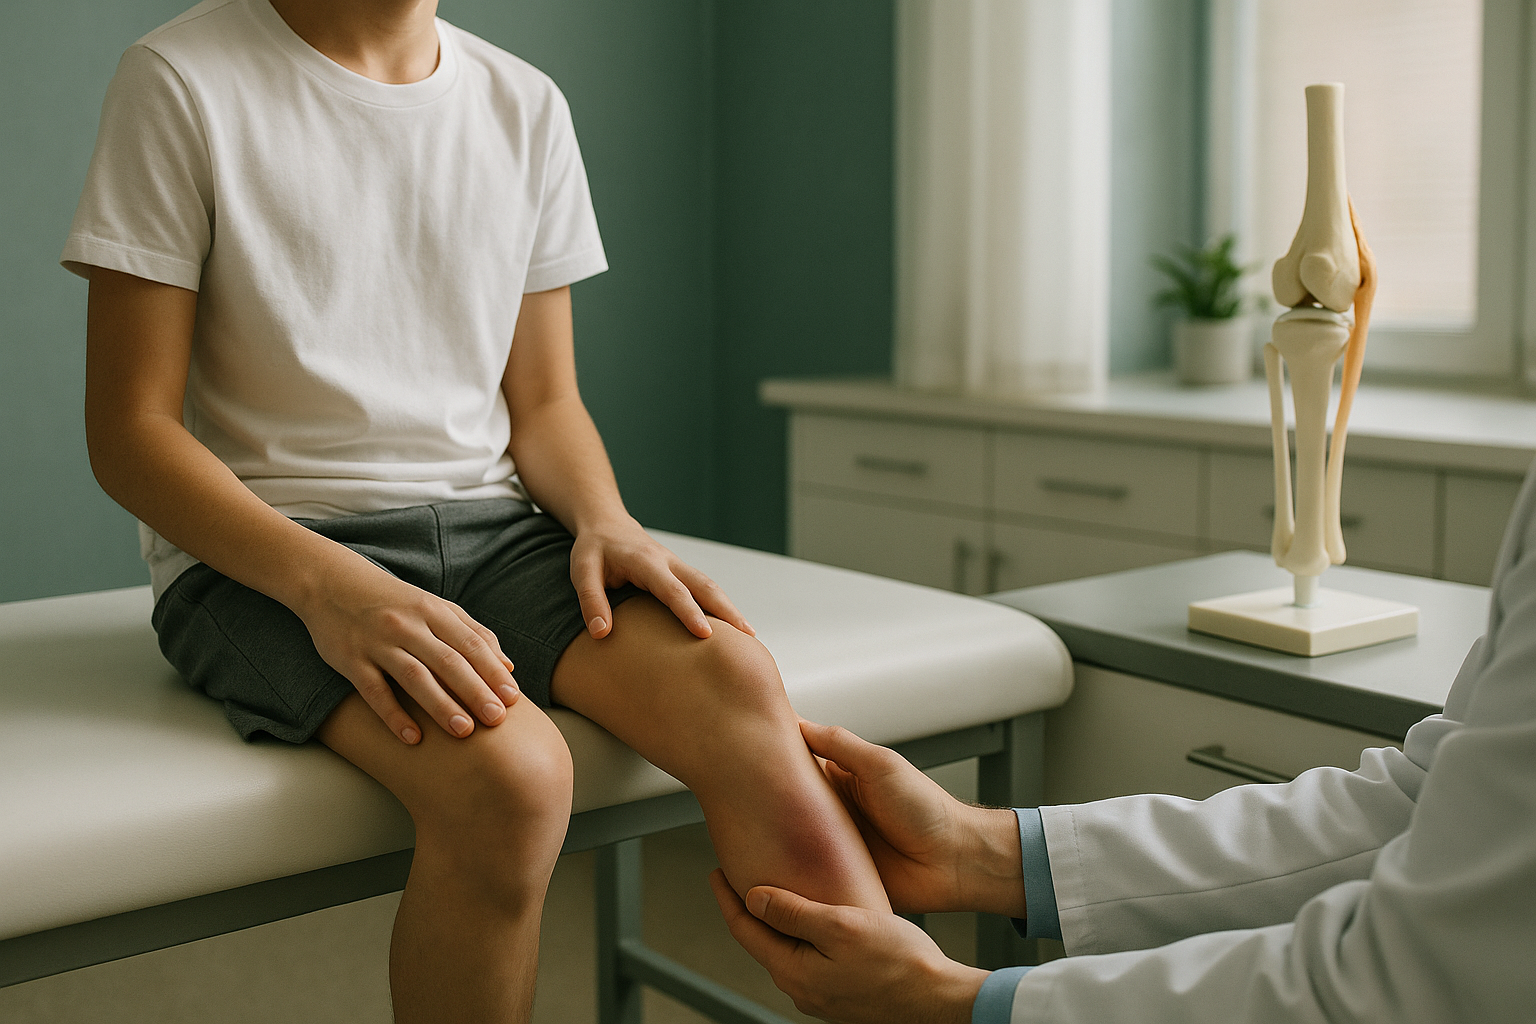
The initial fracture itself is usually treated at the time of injury. The real concern is what happens over the months and years that follow. If part or all of the growth plate stops working, the bone on that side may grow more slowly, or at an angle compared to the healthy side. The signs are often subtle at first and become more obvious as the child grows taller.
Clothes may hang unevenly, or one shoe may wear differently. This can point to a developing leg length discrepancy.
The limb may start to bow inwards or outwards as the damaged side of the growth plate falls behind.
Altered bone shape can change how a joint moves, sometimes causing discomfort during activity.
What causes growth plate injuries and physeal arrest?
Most growth plate fractures happen during sport, play, or accidental falls. The severity depends on how the fracture runs through the physis. Orthopaedic surgeons classify these injuries using the Salter-Harris system, which groups them into types based on the fracture pattern. Higher types carry a greater risk of long-term growth disturbance.
The most common cause. A sudden force, twist, or impact can crack the physis.
Salter-Harris types III, IV, and V involve the joint surface or crush the physis, raising the risk of arrest.
A bony bridge forms across the damaged physis, partially or fully stopping growth on that side.
Not every growth plate fracture leads to physeal arrest. Many heal completely and the child's growth continues normally. The challenge is that arrest can develop silently over many months, which is why ongoing follow-up imaging is so important.
How is a growth plate injury monitored over time?
Monitoring involves periodic imaging of both limbs so the treating team can compare growth on the injured side with the healthy side. The child's orthopaedic surgeon will typically request scans at intervals until the growth plates have fully closed. This can mean years of follow-up, particularly if the injury happened when the child was young and has a lot of growing still to do.
The key measurements taken at each follow-up are limb length and joint alignment. Even small differences, when spotted early, can guide the surgeon's decisions. If a significant discrepancy or angular change is developing, options such as guided growth or, in some cases, corrective surgery can be considered at the right time. Waiting until the problem is obvious can make it harder to treat.
When is MRI more appropriate? EOS shows bones, joints, and alignment clearly. For soft-tissue detail, such as assessing a bony bridge within the growth plate itself, MRI is usually the better tool. Your child's specialist will advise which imaging is needed at each stage.
Why is standing imaging better for growth plate follow-up?
Standing, weight-bearing imaging captures the skeleton as it actually works. When a child lies down for a scan, gravity is removed, muscles relax, and subtle alignment differences can be masked. A standing full-length image of both legs, from hips to ankles, shows the true picture: any developing tilt, bow, or length difference becomes visible in a single exposure.
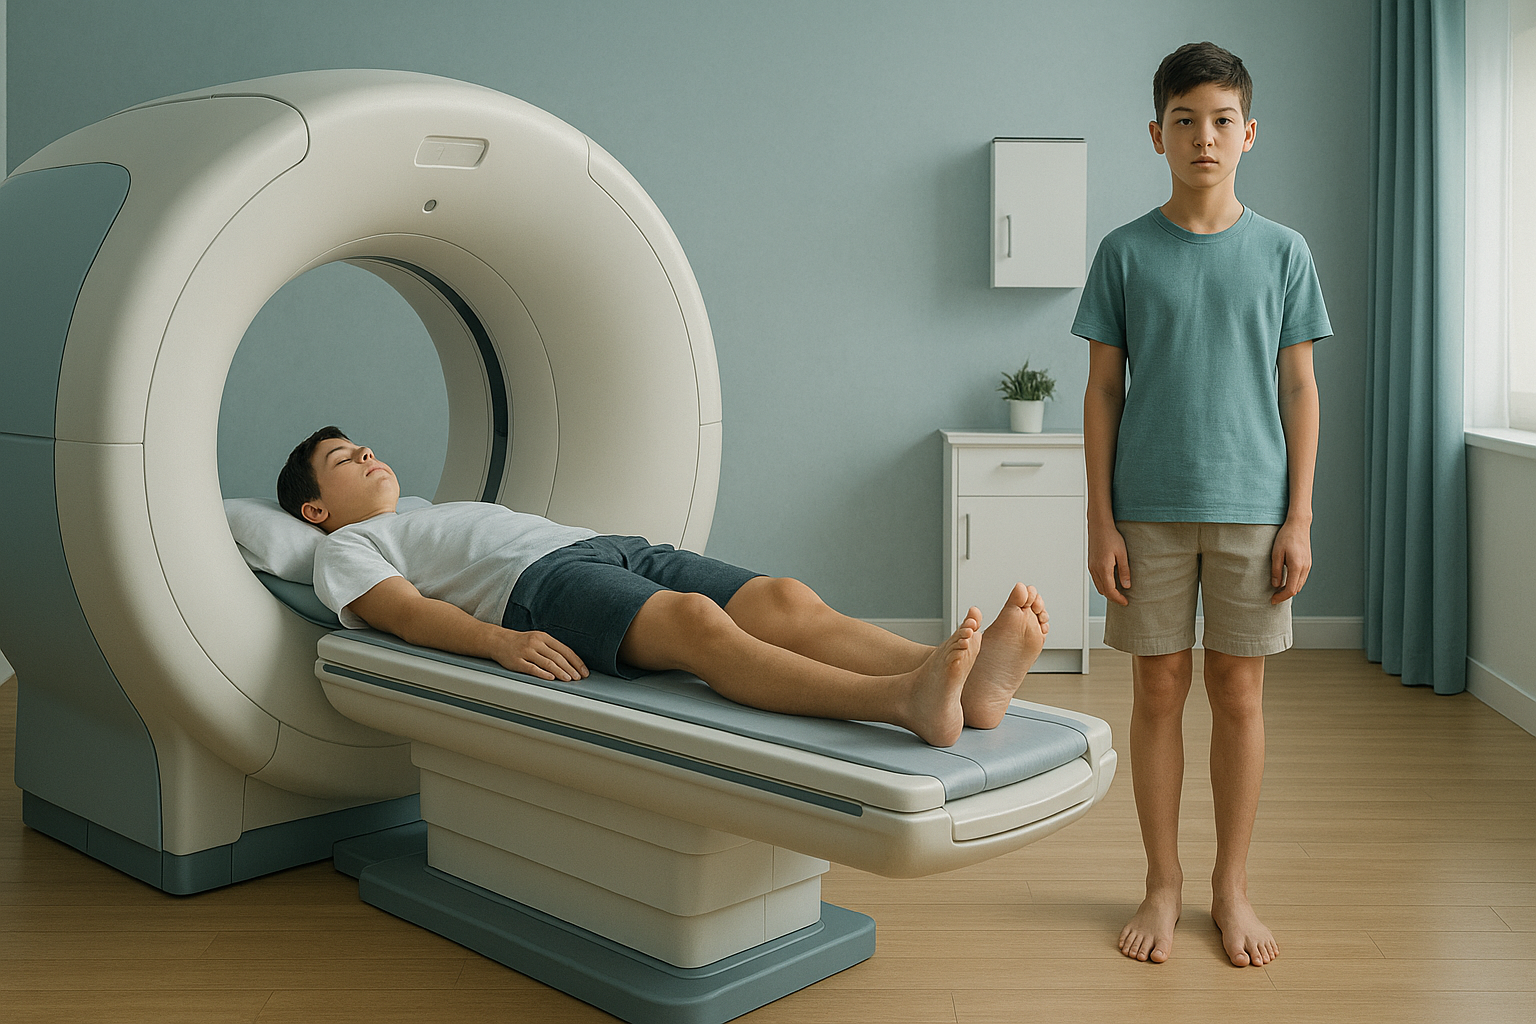
EOS technology is particularly well suited to this kind of repeated follow-up. It uses about 90% less radiation than a standard X-ray, around ten times less. For a child who may need imaging every six to twelve months over several years, keeping cumulative radiation as low as possible matters a great deal.
At ScanAlign, low dose standing imaging, each scan produces a full-length, weight-bearing image of both limbs on a single exposure. This gives the orthopaedic team everything they need to track alignment and length accurately. Learn more about paediatric imaging at ScanAlign.
If your child's surgeon has recommended follow-up imaging after a growth plate fracture, a low-dose standing EOS scan can provide the measurements they need with minimal radiation.
Book a free video consultationWhat can be done if a growth plate injury causes deformity?
If monitoring reveals that a significant angular deformity or limb length difference is developing, the child's orthopaedic surgeon has several options. The right approach depends on how much growing the child has left and how large the problem is.
- Guided growth. A small plate is placed near a healthy growth plate to slow one side temporarily, allowing the limb to straighten as it grows. This works best when there is still meaningful growth remaining.
- Epiphysiodesis. The growth plate on the longer or unaffected leg is deliberately closed at a carefully timed point, allowing the shorter side to catch up.
- Corrective surgery. In more severe cases, the bone may be cut and realigned, or lengthened surgically.
The common thread is timing. All of these decisions depend on accurate, up-to-date measurements of how each limb is growing. That is why consistent follow-up imaging matters so much.
Frequently asked questions about growth plate injuries
No. Most growth plate fractures heal well, and the child's growth continues normally. Only a proportion, particularly the more severe Salter-Harris types, lead to physeal arrest and long-term growth disturbance.
Physeal arrest happens when part or all of a damaged growth plate stops producing new bone. A bony bridge forms across the physis, and the affected area of the bone stops growing while the healthy side continues. This can lead to angular deformity or a shorter limb.
Follow-up usually continues until the child's growth plates have fully closed, which can be into the mid to late teenage years. The younger the child at the time of injury, the longer the monitoring period is likely to be.
It is possible, but not inevitable. If part of the growth plate is damaged, the bone may grow at a slight angle over time. Regular imaging picks this up early so it can be addressed before it becomes a bigger problem.
It is a system used by doctors to describe how a fracture runs through the growth plate. There are five main types. Types I and II are the most common and generally carry a lower risk of growth problems. Types III, IV and V involve the joint surface or crush the physis and carry a higher risk.
EOS captures a full-length, weight-bearing image of both limbs in a single standing scan. This makes it straightforward to compare limb lengths and joint angles accurately. Because it uses about 90% less radiation than a standard X-ray, around ten times less, it is well suited to repeated scans over several years of follow-up.
No GP referral is needed. You can book a free video consultation directly. Many families bring a request from their orthopaedic surgeon, but it is not a requirement.
Yes. EOS uses about 90% less radiation than a standard X-ray, around ten times less. This makes it a particularly good choice for children who need repeated imaging over time, as the cumulative dose stays very low.
EOS is designed to show bones, joints, and alignment. For detailed soft-tissue assessment, including the internal structure of a growth plate, MRI is usually the better tool. Your child's specialist will advise which imaging is needed.
You can book a free video consultation to discuss what scan is right for your child and what is involved.
Concerned about your child's growth after a fracture?
A short, free video consultation with our team can help you understand whether a low-dose standing scan is the right next step.
Book a free video consultationWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- Salter, R.B. and Harris, W.R. (1963). Injuries involving the epiphyseal plate. The Journal of Bone and Joint Surgery (American), 45(3), pp.587-622.
- British Orthopaedic Association. Standards for Trauma and Orthopaedics (BOAST): Children's fractures. Available at: boa.ac.uk
- Deschênes, S. et al. (2010). Diagnostic imaging of spinal deformities: reducing patients' radiation dose with a new slot-scanning X-ray imager. Spine, 35(9), pp.989-994.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.