
Is Spina Bifida Occulta Something to Worry About?
Usually, no. Spina bifida occulta is a small gap in one or more vertebrae at the base of the spine. It is extremely common, affecting up to one in ten people, and the vast majority never know they have it. Most people need no treatment at all. It is often found by chance on imaging done for something else entirely.
Key takeaways
- Spina bifida occulta means part of a vertebra did not fully close during development. The "occulta" means hidden.
- It is usually an incidental spine finding, spotted on an x-ray or scan done for another reason.
- Most people have no symptoms and need no treatment.
- In rare cases, an associated tethered spinal cord may need further investigation.
- If you have new leg weakness, numbness, or bladder or bowel changes, seek urgent medical attention.
What is spina bifida occulta?
Spina bifida occulta is a minor variation in the way one or more vertebrae formed before birth. In a typical spine, each vertebra has a bony arch that closes around the spinal cord to protect it. In spina bifida occulta, that arch did not fully close on one side, leaving a small gap in the bone.
The word "occulta" comes from the Latin for hidden. Unlike the more serious open forms of spina bifida, the spinal cord and nerves are not exposed. The skin over the area is intact. There is no visible opening, and most people live their entire lives without ever knowing about it.
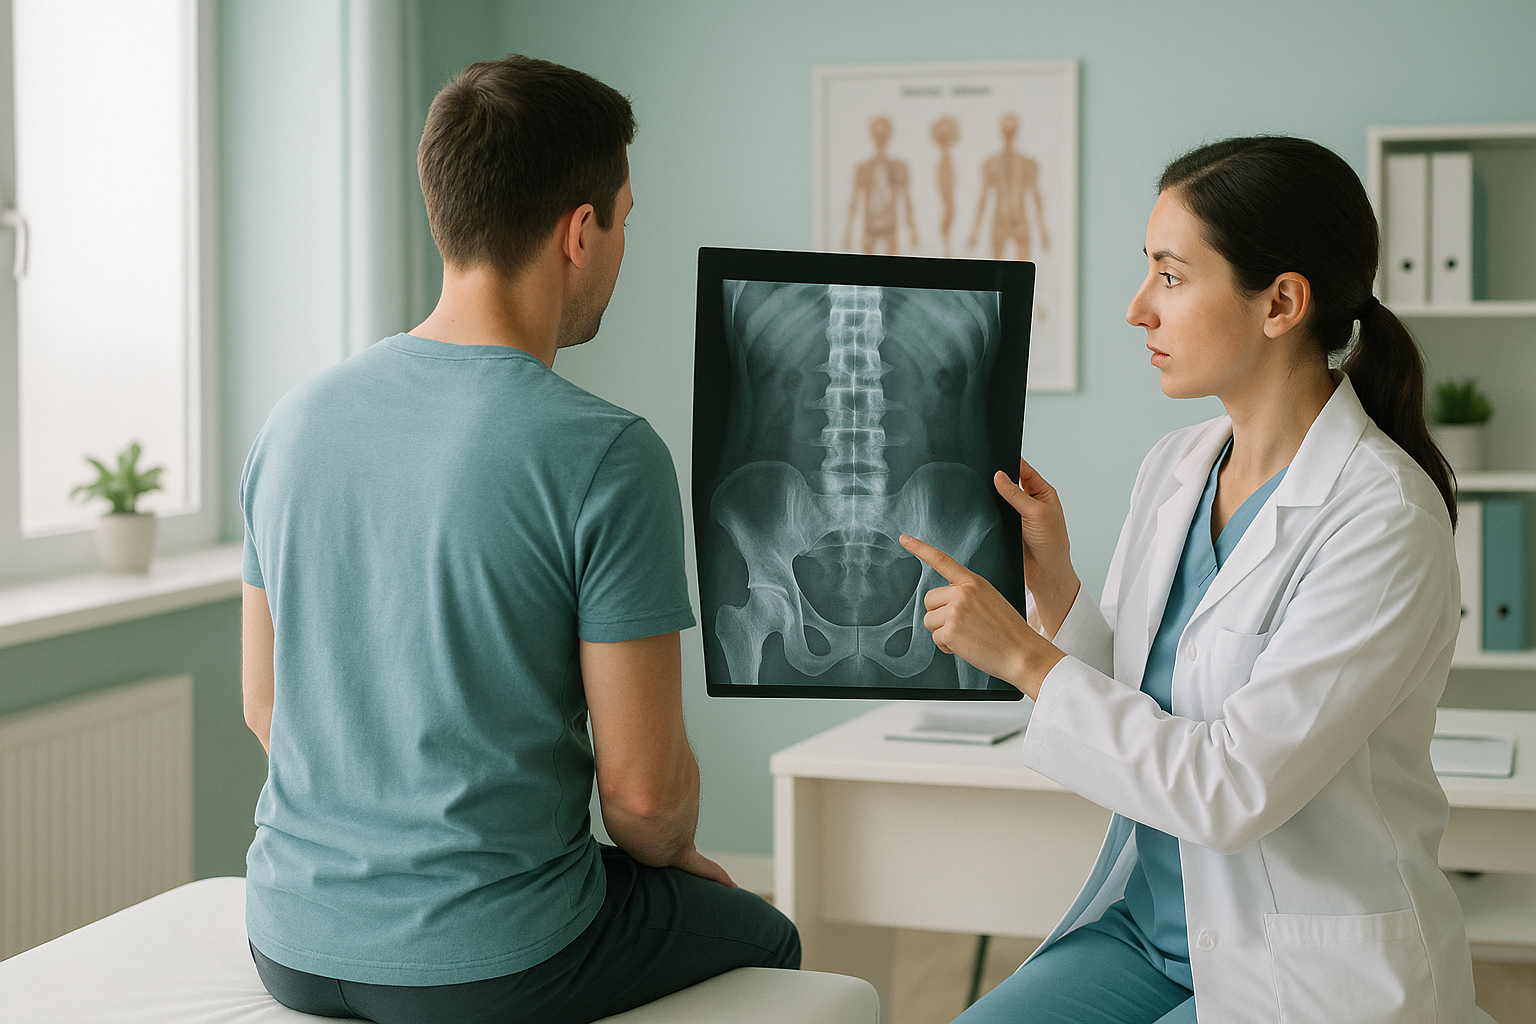
The gap most often appears at the L5 or S1 level, right at the bottom of the spine. It shows up as an incomplete vertebral arch on an x-ray. If you have recently had a full spine x-ray and seen this phrase on your report, the information below will help you understand what it means.
Does spina bifida occulta cause symptoms?
In the vast majority of cases, no. Most people with spina bifida occulta are completely symptom-free. The gap in the bone is simply too small and too well covered by surrounding tissue to cause any problems.
Some people worry that their back pain is caused by it. In most situations, the two are unrelated. Back pain is extremely common, and the presence of an incidental spine finding like this on your report does not mean it is the source of your discomfort.
Most people discover it only when imaging is done for another reason.
If you do have back pain, it is far more likely to have another cause.
Often described on a report as an "incidental finding" with no clinical significance.
What about a sacral dimple in adults?
A sacral dimple is a small indent in the skin at the very base of the spine, just above the crease of the buttocks. Many adults notice one and wonder whether it is connected to spina bifida occulta.
Most sacral dimples are entirely harmless and very common. They are simply a natural skin variation. In some cases, a dimple or other skin marker (such as a small tuft of hair or a patch of different-coloured skin) can sit over an area of spina bifida occulta, but this does not mean anything is wrong.
If the dimple is shallow and close to the surface, it almost always needs no investigation. A deeper dimple, or one accompanied by other skin changes, may occasionally prompt your doctor to arrange further imaging to check the spinal cord beneath, but this is uncommon.
Is spina bifida occulta serious?
For the overwhelming majority of people, it is not serious at all. It is one of the most common incidental findings on spinal imaging. Because the spinal cord and nerves are not affected, and the skin is closed, it behaves as a harmless anatomical variation rather than a medical condition.
The name can cause unnecessary alarm. Hearing "spina bifida" on a report understandably triggers worry, because the open forms of spina bifida are serious conditions. But spina bifida occulta is a very different situation. It is helpful to think of it as a footnote on your report rather than a diagnosis.
- No leg weakness or numbness
- Normal bladder and bowel function
- No progressive foot changes
- Found by chance on imaging
- New or worsening leg weakness
- Numbness spreading in the legs or feet
- Loss of bladder or bowel control
- Sudden severe back or leg pain
Important. If you develop sudden leg weakness, numbness in the saddle area, or any change in bladder or bowel control, contact your GP, call 111, or attend A&E immediately. These are red-flag symptoms that require urgent assessment regardless of any existing findings on your spine.
When does spina bifida occulta need further investigation?
Further investigation is only needed in the rare situation where the spinal cord may be tethered. A tethered cord means the bottom of the spinal cord is attached to the surrounding tissue more than it should be, which can stretch nerves as the body grows and moves. This is uncommon in adults with spina bifida occulta, but it does happen occasionally.
Your doctor may suggest further investigation if you have:
- Progressive leg weakness or changes in walking
- Gradual loss of feeling in the feet or legs
- Bladder problems that have no other obvious cause
- A foot that is gradually changing shape
If none of these apply to you, there is very little reason to pursue additional imaging for a finding of spina bifida occulta on its own.
If you do have ongoing spinal or posture concerns beyond this incidental finding, ScanAlign standing EOS imaging can capture your full spine while standing, which shows how your body actually bears weight. This is a separate consideration from spina bifida occulta itself.
Does spina bifida occulta show up on MRI or x-ray?
It is usually spotted on a plain x-ray as a gap in the bony arch of a vertebra. This is why it is so often described as an incidental finding, because the x-ray was taken for a different reason and the gap simply appears on the image.
When MRI is more helpful. EOS and x-rays show bones, joints and alignment clearly. But if there is any suspicion of a tethered cord or nerve involvement, MRI is usually the better tool. MRI shows soft tissue, the spinal cord and nerves in detail that bone imaging cannot provide. Your doctor will guide you on whether MRI is appropriate in your case.
Frequently asked questions about spina bifida occulta
No. Spina bifida occulta is the mildest form and is very different from the open forms (myelomeningocele or meningocele). In the open forms, the spinal cord or its coverings push through a gap in the spine. In occulta, the skin is closed and the cord is not exposed. Most doctors consider it a normal variation rather than a disease.
Very common. Studies suggest it is present in up to one in ten people. Many never find out because it causes no symptoms and is only discovered if the lower spine happens to be imaged.
In the vast majority of cases, no. Back pain is extremely common and has many possible causes. If you have both spina bifida occulta and back pain, the two are almost always unrelated. Your clinician will look for more likely causes such as muscle strain, disc problems, or posture-related issues.
It means the bony arch of the fifth lumbar vertebra (L5), near the bottom of your spine, did not fully close. L5 and S1 are the most common locations for this finding. On its own, it is considered a normal anatomical variation and is not a cause for concern.
Almost never. Because it is usually asymptomatic, there is nothing to treat. Treatment would only be considered in the rare case of a tethered spinal cord causing progressive symptoms, and that decision would be made by a specialist.
A shallow sacral dimple near the skin surface is very common and harmless. If it is deeper, positioned further from the crease, or accompanied by other skin changes like a tuft of hair, your GP may suggest further assessment, but this is uncommon.
The bony gap itself does not change. It has been there since before birth. In very rare cases where a tethered cord is present, symptoms can progress gradually, but this is the exception and not the rule.
If you have no symptoms, no follow-up scan is needed for this finding alone. If you have separate concerns about your spinal alignment or posture, you could discuss a standing spine assessment with your clinician or book a standing spine scan to look at your overall alignment.
There is some evidence that it can run in families, but the genetics are not straightforward. It is influenced by a combination of genetic and environmental factors during early development. Having it yourself does not necessarily mean family members will have it.
An incidental finding is something spotted on imaging that was not the reason you had the scan. It is an observation, not necessarily a problem. A diagnosis is a confirmed condition that explains your symptoms or needs management. Spina bifida occulta almost always falls into the "incidental finding" category.
Have questions about a finding on your spine report?
Speak with a specialist radiographer to understand what your imaging shows and whether any further assessment would be helpful.
Book a free video consultationSources
- NHS. Spina bifida: overview. nhs.uk (accessed 2024).
- Defined by Fidas A et al. "Prevalence of spina bifida occulta in a clinically normal population." Clinical Radiology, 1987; 36(2): 159-160.
- American Association of Neurological Surgeons. Spina Bifida. aans.org (accessed 2024).
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.