
When Do Steroid Injections Help, and How Long Do They Last?
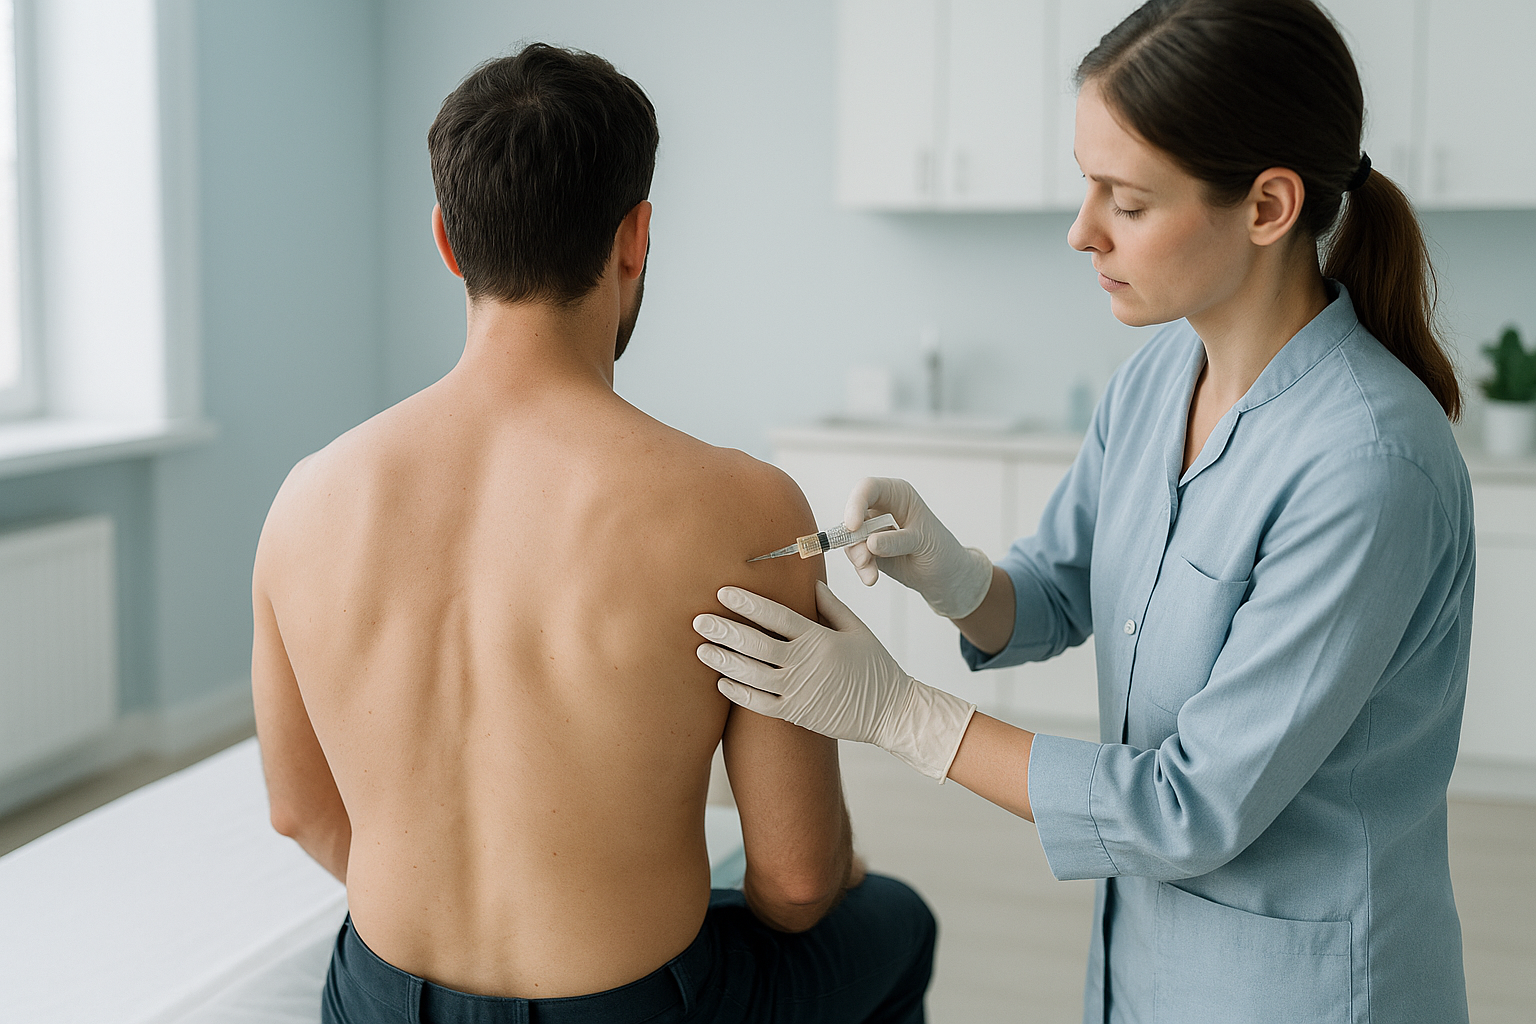
A steroid injection delivers a corticosteroid, usually with a local anaesthetic, directly to an inflamed joint, tendon or nerve root. It can reduce pain and swelling for weeks to months, but it is not a cure. Relief varies by person and condition. Knowing the cause of your pain through proper imaging helps decide whether an injection is the right step.
Key takeaways
- Steroid injections reduce inflammation, they do not fix the underlying cause of pain.
- Relief typically lasts from a few weeks up to several months, depending on the condition.
- Repeated injections carry risks, so most clinicians limit how many you receive per year.
- Accurate imaging before an injection helps confirm the pain source and guide the needle to the right spot.
- Physiotherapy alongside an injection often produces better long-term results than the injection alone.
What is a steroid injection and how does it work?
A steroid injection places a corticosteroid medication directly into an inflamed area of your body. The corticosteroid is a powerful anti-inflammatory, not the same as the anabolic steroids used in sport. It works by damping down the immune response in that specific area, reducing swelling, irritation and pain.
Most injections also contain a local anaesthetic. This numbs the area quickly and can give almost immediate, short-lived relief. The steroid itself takes a few days to a couple of weeks to reach its full effect.
Steroid injections can be therapeutic, meaning they aim to ease pain and help you move. They can also be diagnostic. If an injection into a specific joint takes the pain away, it confirms that the joint is the source of the problem. This is especially useful in conditions like facet joint arthropathy, where pain can be tricky to pin down.

Where are steroid injections commonly used?
Steroid injections are used in many areas of the body. The most common include the back, knee, shoulder, hip and the small joints of the hands and feet. The specific type of injection depends on the target.
How long does a steroid injection last?
There is no single answer because it depends on the condition being treated, the location and your individual response. As a rough guide, many people notice improvement within a few days and the effect can last from a few weeks to several months. Some people experience relief for six months or longer. Others find the benefit wears off after just a few weeks.
The local anaesthetic component may give near-instant relief that fades within hours. There can then be a gap of a few days before the steroid takes full effect. This gap sometimes worries people, but it is normal.
If an injection gives only brief or no relief, it may mean the injection did not reach the right structure, or that the source of your pain lies elsewhere. This is one reason why accurate imaging before an injection matters.
What are the side effects of steroid injections?
Most steroid injections are straightforward, but they do carry risks. Your treating clinician should explain these before you consent.
- A short-lived flare of pain at the injection site for a day or two
- Temporary flushing of the face
- A small rise in blood sugar levels, especially in people with diabetes
- Mild bruising or skin colour change at the injection site
- Infection at the injection site (rare but serious)
- Weakening of nearby tendons with repeated injections
- Thinning of the skin or fat pad at the injection point
- Allergic reaction to the medication
Because of the risk to tendons and local tissues, most clinicians limit the number of steroid injections to a particular area. This is usually no more than two or three injections per year, though guidelines vary. Each injection should be a considered decision, not an automatic repeat.
Important: If you develop sudden weakness, numbness, or loss of bladder or bowel control after a spinal injection, seek urgent medical attention. Contact your GP, call 111, or go to A&E straight away.
Why does imaging matter before a steroid injection?
A steroid injection works best when the clinician knows exactly where your pain is coming from. Without clear imaging, there is a risk of injecting the wrong area, which may explain why some people find injections unhelpful.
Standard lying-down imaging such as X-ray, CT or MRI captures the anatomy while your muscles are relaxed and gravity is removed. This can miss alignment problems that only appear when you are upright and weight-bearing. Your body works as a connected chain from your feet to your head. A tilt or shift in one area can cause another part to compensate, and the pain often appears at the compensating site rather than the true source.
ScanAlign standing EOS imaging captures your full skeletal alignment in a natural standing position, using about 90% less radiation than a standard X-ray, around ten times less. This whole-body view can reveal whether a misalignment elsewhere is driving the inflammation you feel in your back, hip or knee. With that information, your treating clinician can target an injection more accurately, or decide that a different approach is more appropriate.
A note on MRI: EOS imaging is excellent for showing bones, joints and whole-body alignment. If your clinician needs to assess soft tissues, discs or nerves, MRI is usually the better tool. Both types of imaging play different, complementary roles in planning your care.
Frequently asked questions about steroid injections
The local anaesthetic often gives immediate but short-lived relief. The steroid itself usually takes between two days and two weeks to reach its full effect. A brief increase in pain after the anaesthetic wears off is common and does not mean the injection has failed.
Yes, but most clinicians limit the number per area, often to two or three per year. Repeated injections can weaken tendons and thin the tissues. Each repeat should involve a fresh clinical decision rather than being given automatically.
You will usually feel a sharp scratch followed by pressure. The local anaesthetic numbs the area quickly. Some people experience a dull ache or a flare of pain for a day or two afterwards. Your clinician can advise on simple pain relief during this period.
An epidural steroid injection delivers medication into the epidural space around the spinal nerves. It targets nerve-related pain such as sciatica. A joint injection places the medication directly into a joint like the knee, shoulder or a facet joint in the spine. The choice depends on which structure is inflamed.
No. A steroid injection reduces inflammation and pain, which can create a window for you to engage with physiotherapy or other rehabilitation. It does not fix the underlying structural cause of the problem. This is why understanding the root cause through proper imaging matters.
Corticosteroids can cause a temporary rise in blood sugar levels. If you have diabetes, let your clinician know before the injection so you can plan how to manage any changes. The effect usually settles within a few days.
Common reasons include the medication not reaching the exact source of pain, the pain being caused by a structural problem rather than inflammation, or the true pain source being in a different area from where the injection was given. Accurate imaging beforehand reduces this risk.
No. ScanAlign is a private, self-pay clinic. You can book an assessment directly without a GP or consultant referral.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. It captures your full standing skeleton in a single pass, so you avoid the multiple exposures often needed with conventional X-rays.
In many cases, yes. The injection can ease your pain enough to let you move more freely and benefit from targeted exercises. Research suggests that combining an injection with a structured physiotherapy programme often gives better long-term outcomes than an injection on its own.
Understand your pain before your next injection
A standing whole-body scan shows your full alignment under gravity, helping you and your clinician make better decisions about steroid injections or other next steps.
Book a free video consultationWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- National Institute for Health and Care Excellence (NICE). Low back pain and sciatica in over 16s: assessment and management (NG59). 2016, updated 2020.
- Chou R, Hashimoto R, Friedly J, et al. Epidural corticosteroid injections for radiculopathy and spinal stenosis: a systematic review and meta-analysis. Annals of Internal Medicine. 2015;163(5):373-381.
- NHS. Steroid injections. nhs.uk/conditions/steroid-injections. Accessed 2024.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.