
What Is Cervical Instability, and How Is It Assessed?
Cervical instability means there is more movement than normal between two or more vertebrae in your neck. It can cause neck pain, headaches and a feeling that your head is too heavy. The standard way to assess it is with flexion-extension X-rays, which capture the neck as you bend it forward and back, revealing movement that ordinary imaging may miss.
Key takeaways
- Cervical instability is excessive movement between neck vertebrae, not simply a stiff or sore neck.
- Flexion-extension X-rays are the accepted way to check for abnormal movement.
- It is more common in people with generalised hypermobility syndrome or connective tissue conditions.
- Imaging taken lying down can miss instability because gravity and muscle tone change when you stand.
- A specialist referral is usually needed for diagnosis and management.
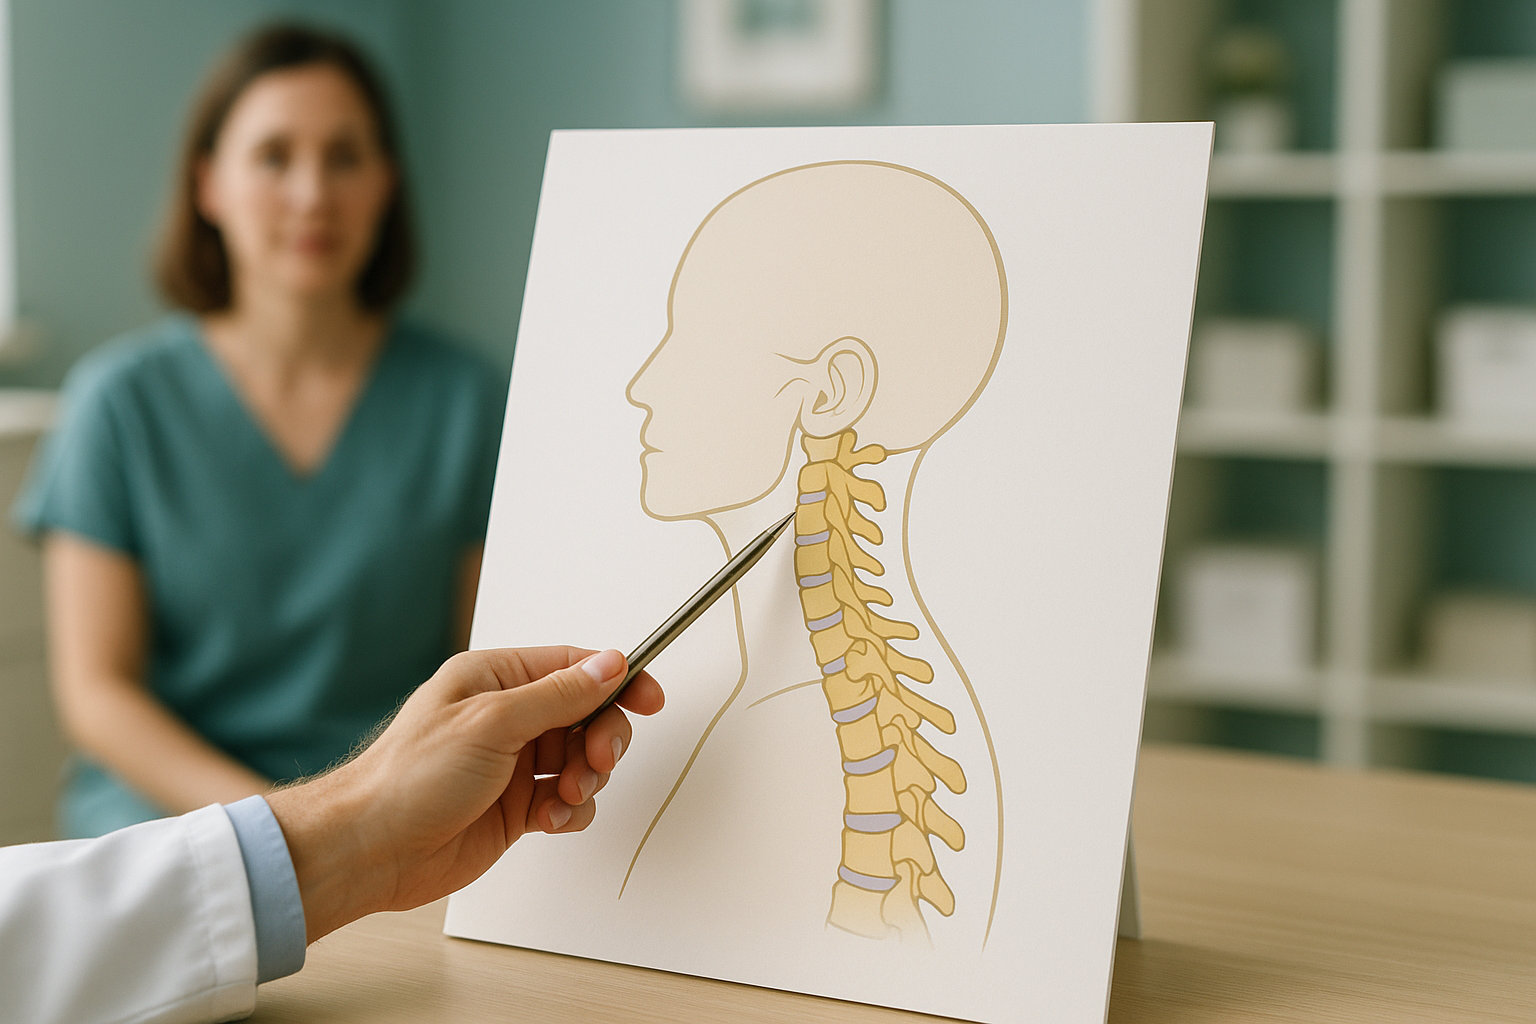
Your cervical spine is the top seven vertebrae of your neck. They support the weight of your head and allow you to look up, down and to either side. Between each pair of vertebrae, ligaments, small joints and discs keep everything in place. When those structures are damaged, stretched or naturally lax, the vertebrae can shift more than they should. That excess movement is cervical instability.
This term also covers two specific areas that specialists pay close attention to. Craniocervical instability describes excess movement where the skull sits on the top vertebra (C1). Atlantoaxial instability describes excess movement between C1 and C2, the two uppermost vertebrae. Both are assessed the same way, with careful imaging and clinical examination.
What are the symptoms of cervical instability?
Symptoms vary depending on which level of the neck is affected and how much excess movement there is. Many people describe a cluster of problems rather than a single symptom.
A constant sense that your head is too heavy for your neck, especially by the end of the day.
Deep aching in the upper neck, often worse after sitting upright or looking at a screen.
A feeling of being off-balance, light-headed or disoriented when turning your head.
Persistent headaches that start at the back of the head and can spread forward.
Some people report blurred vision, difficulty concentrating or a foggy feeling.
When to seek urgent help
If you develop sudden weakness or numbness in your arms or legs, difficulty walking, loss of bladder or bowel control, or severe worsening symptoms, contact your GP, call 111, or go to A&E straight away. These could indicate spinal cord compression, which needs immediate attention.
What causes cervical instability?
Cervical instability happens when the ligaments, joints or other structures that hold the neck vertebrae together cannot do their job properly. This can be the result of injury, degeneration over time, or an underlying condition that affects connective tissue.
Whiplash, falls or sports injuries can stretch or tear the ligaments that stabilise the upper neck.
Conditions such as hypermobile Ehlers-Danlos syndrome make ligaments throughout the body more lax, including in the neck.
Years of disc and joint wear can gradually reduce the support around individual vertebrae.
Rheumatoid arthritis, for example, can erode the ligaments at C1-C2 over time.
If you already have generalised joint hypermobility syndrome, your neck ligaments may be naturally more elastic. This does not automatically mean you have cervical instability, but it does mean the possibility should be considered if you have persistent symptoms.
How is cervical instability properly assessed?
The accepted standard for assessing cervical instability is a combination of clinical examination by a specialist and flexion-extension imaging. A specialist, usually a spinal surgeon or a consultant in musculoskeletal or neuroradiology, will examine your neck movements and neurological function before requesting the right imaging.
Flexion-extension X-rays
These are X-rays taken while you gently bend your neck forward (flexion) and backward (extension). The two images are then compared. If a vertebra slides further forward or backward than the accepted threshold, that segment is considered unstable. This is the standard test because a single static image, taken in a neutral position, may look perfectly normal even when significant movement is present.
Why a standard X-ray or MRI may not be enough
A routine neck X-ray captures one position only. An MRI is taken lying down, which removes the load of your head and lets muscles relax. Both can miss instability that only becomes apparent when the neck moves under its own weight. That is why flexion-extension views are so important. They test the neck while it is actually doing its job.
A note on MRI. EOS and X-ray are excellent at showing bone position and alignment. For soft tissue, discs, the spinal cord or nerves, MRI is usually the better tool. Many people with suspected cervical instability will need both types of imaging at different stages of their assessment.
A word of caution about overdiagnosis
Craniocervical instability has received a lot of attention online, particularly within the hypermobility community. While it is a real and sometimes serious condition, there is a risk of overdiagnosis. Not every headache or dizzy spell in someone with hypermobility means the upper neck is unstable. A proper assessment requires the right specialist, the right imaging, and careful clinical correlation. Be wary of any clinic that offers a diagnosis based on a single scan without a thorough clinical examination.
Can a standing scan help with neck and spine assessment?
Yes, but it is important to be clear about what a standing scan does and does not do. A standing whole-body EOS scan captures your entire spine, from skull to pelvis, while you are upright and weight-bearing. This shows how your cervical lordosis (the natural curve of your neck) relates to the rest of your spinal alignment and posture under gravity.
When you lie down for a standard X-ray or MRI, gravity is removed and muscles relax. This can mask the way your spine actually behaves in daily life. A standing image reveals compensatory patterns. For example, if your lower back is unusually flat, your neck may curve more than expected to keep your head balanced. Understanding this full-chain picture is valuable context for any specialist assessing your neck.
A standing EOS scan is not a replacement for dedicated flexion-extension views. It does not test movement. What it does is provide a detailed, low-dose standing image of your full spinal alignment, using about 90% less radiation than a standard X-ray, around ten times less. This broader picture can be shared with your specialist alongside other imaging to build a more complete understanding of your neck problem.
If you would like to see how your full spine aligns while standing, you can book a standing neck and spine scan at our Harley Street clinic. We will discuss your situation in a free video consultation first.
Book a free video consultationWhat can help with cervical instability?
Management depends entirely on the severity and the underlying cause, and it is guided by a specialist. ScanAlign is a diagnostic imaging clinic and does not provide treatment. The information below is general only.
- Specialist referral. A spinal surgeon, neurologist, or rheumatologist experienced with cervical instability should oversee your care.
- Physiotherapy. Strengthening the deep neck flexor muscles and improving postural control can provide more support to the cervical spine. This needs to be supervised by a physiotherapist who understands the condition.
- Collar use. In some cases a soft or rigid collar may be recommended for short periods, but this is a specialist decision. Prolonged collar use without guidance can weaken the muscles further.
- Further investigation. Depending on findings, upright or dynamic MRI, CT, or additional specialist imaging may be needed.
- Surgery. In severe or progressive cases, a spinal surgeon may discuss fusion to stabilise the affected segment. This is reserved for clearly confirmed instability with significant symptoms.
Frequently asked questions about cervical instability
Most people describe a heavy or wobbly feeling in the head, deep neck pain, headaches at the base of the skull, and sometimes dizziness or brain fog. Symptoms are often worse after being upright for a long time or after holding the head in one position.
Not quite. Cervical instability is a broader term covering any level in the neck. Craniocervical instability specifically describes excess movement at the junction between the skull and C1. Atlantoaxial instability refers to excess movement between C1 and C2. All are assessed in a similar way.
Generalised hypermobility syndrome and connective tissue conditions like hypermobile Ehlers-Danlos syndrome can make ligaments throughout the body more lax, including those in the cervical spine. This does not mean everyone with hypermobility has cervical instability, but it raises the possibility if symptoms are present.
Flexion-extension X-rays are the accepted standard. These capture the neck bending forward and backward, showing whether a vertebra moves beyond normal limits. An MRI may also be needed to assess the spinal cord, discs and ligaments. A single static X-ray in a neutral position is not sufficient.
A standard MRI taken lying flat shows the spine in an unloaded position. Instability often only becomes apparent under load or during movement, so a lying-down MRI alone may not capture the excess movement. That said, MRI remains essential for assessing soft tissue, the spinal cord and nerves.
An EOS scan is a single standing image. It does not test movement, so it cannot diagnose instability on its own. What it does is show your full spinal alignment under gravity, including the position and curve of your cervical spine, which can provide useful context for a specialist already investigating your neck.
No. You can self-refer. We offer a free video consultation first to discuss your situation and make sure a standing EOS scan is appropriate for you.
An EOS scan uses about 90% less radiation than a standard X-ray, around ten times less. This makes it one of the lowest-dose options for full-body skeletal imaging.
For current pricing and what is included, please visit our FAQs page.
A diagnosis should come from a qualified specialist using proper imaging, not from a single scan or an online assessment. If you have been given this diagnosis, ask to see the flexion-extension views and discuss the findings with a spinal surgeon or neurologist. Mild instability is often managed conservatively with physiotherapy. Severe cases may need closer monitoring or surgical input.
See how your whole spine aligns while standing
A free video consultation lets us discuss your symptoms and whether a standing EOS scan would add useful information for your specialist.
Book a free video consultationLearn more about ScanAlign standing EOS imaging and how whole-body alignment assessment works.
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- White AA, Panjabi MM. Clinical Biomechanics of the Spine. 2nd ed. Philadelphia: Lippincott; 1990. (The foundational reference for cervical stability criteria and measurement thresholds.)
- British Society of Skeletal Radiologists. Guidelines on flexion-extension radiography of the cervical spine. Available at: bssr.org.uk
- NHS. Neck pain: causes, treatment and when to get help. Available at: nhs.uk/conditions/neck-pain/
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.