
Disc Bulge or Disc Herniation: What Is the Difference?
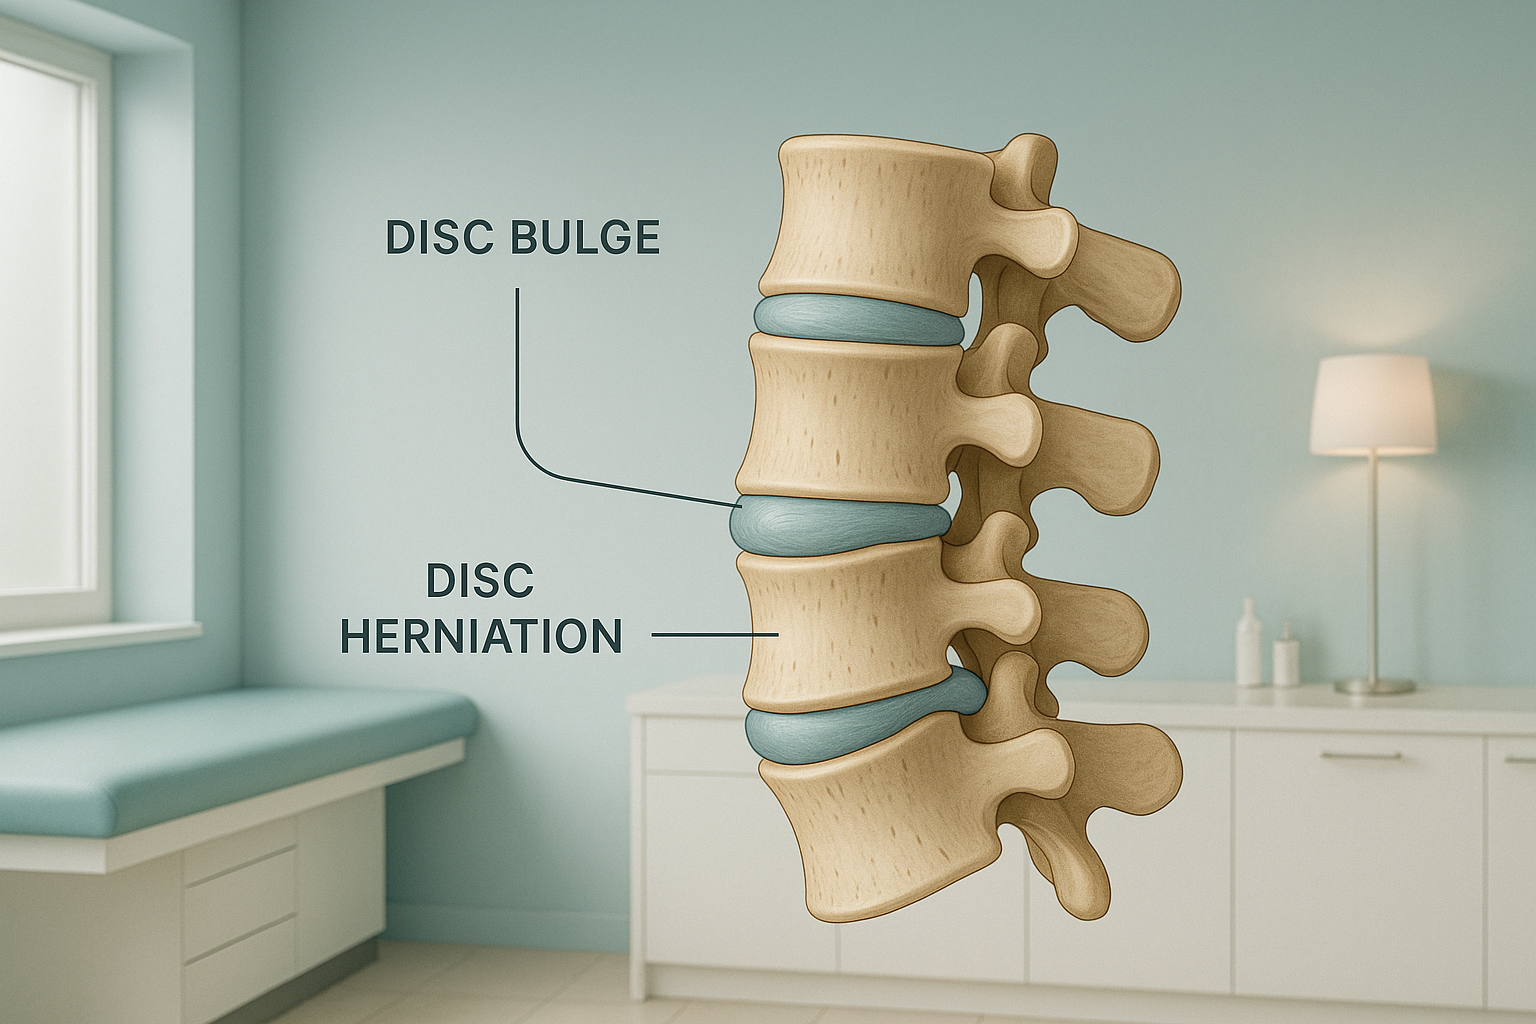
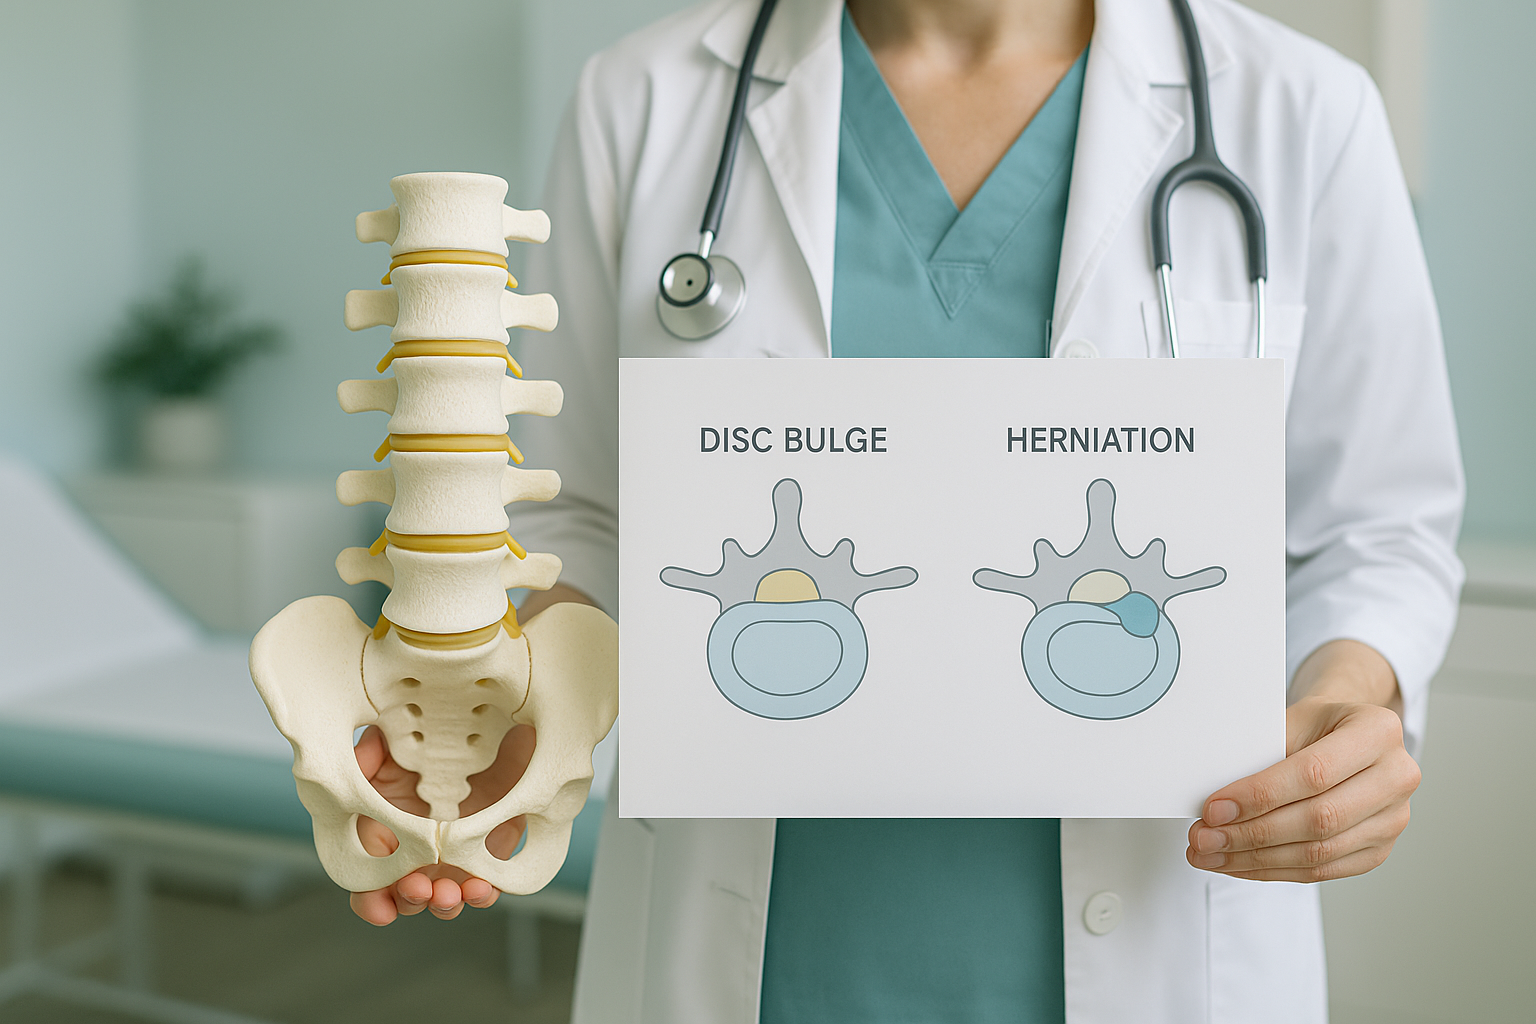
A disc bulge means the outer wall of a spinal disc has expanded outward broadly, like an under-inflated tyre. A disc herniation means the soft centre has pushed through a tear in that outer wall. A bulge is usually wider and flatter. A herniation is more focal and more likely to press on a nearby nerve, though many of both are painless.
Key takeaways
- A bulge involves the whole disc wall bowing outward. A herniation is a localised break-through of the inner material.
- Both can appear on imaging in people with no symptoms at all.
- When symptoms do occur, a herniation is more likely to cause a pinched nerve because it protrudes further.
- Lying-down scans can understate how much a disc is loaded. Standing imaging shows the spine under real weight.
- Most disc problems improve without surgery over time.
What does a spinal disc actually look like inside?
Each spinal disc is a tough, flexible pad that sits between two vertebrae. It has two parts. The outer ring, called the annulus fibrosus, is made of layered fibrous tissue, a bit like the layers of a car tyre. The inner core, the nucleus pulposus, is a gel-like substance that absorbs shock when you move, bend or carry weight.
When the outer ring stays intact but starts to sag outward, that is a bulge. When the outer ring tears and the gel pushes through, that is a herniation. The distinction matters because a herniation can release inflammatory chemicals near nerve tissue, even if the bulge itself is small.
What are the different types of disc problem?
Disc problems sit on a spectrum. A bulge is the mildest form. A herniation can be graded further depending on how far the inner material travels. You may see these terms on a scan report.
The disc wall bows outward over a wide area, often more than half the disc circumference. The outer ring is still intact.
A type of herniation where the base of the bulge is wider than the part that sticks out. The outer ring may be weakened but partially contains the material.
The inner gel has broken fully through the outer ring. The protruding part is narrower at its neck than at its tip.
A fragment of disc material has separated entirely and is now a free piece in the spinal canal. This is the most advanced stage.
Many reports also mention disc height loss, which is a sign of degenerative disc disease, the gradual wear that makes discs more vulnerable to bulging or herniating.
Does a bulging or herniated disc always cause pain?
No. Research consistently shows that many adults have disc bulges or even herniations on MRI but feel no pain at all. The finding alone does not mean you need treatment. Symptoms tend to arise when the disc material presses on or irritates a nearby nerve root, a situation often called nerve root compression.
Common symptoms when a disc does cause trouble
- Localised back or neck pain that worsens with sitting or bending forward.
- Pain, tingling or numbness radiating into the arm or leg, depending on which level is affected.
- Muscle weakness in the affected limb.
- Stiffness that eases with gentle movement but returns with prolonged posture.
When to seek urgent help
If you develop sudden loss of bladder or bowel control, numbness around the groin area, or rapidly worsening weakness in both legs, seek urgent medical attention. Contact your GP, call 111, or go to A&E. These signs may indicate a rare but serious condition called cauda equina syndrome.
What causes a disc to bulge or herniate?
Discs are under constant load. Over years of bending, lifting and sitting, the outer ring can weaken. Several factors speed this up.
Repeated bending, heavy lifting, or prolonged sitting adds strain over time.
Discs lose water content and flexibility naturally as you get older.
A fall, awkward twist, or heavy lift can tear the outer ring abruptly.
Poor posture or a tilt in the pelvis can overload one side of a disc more than the other.
Often there is no single dramatic event. The disc weakens gradually, and a minor movement triggers the final bulge or tear.
How does standing imaging help with disc problems?
Standing, weight-bearing imaging shows your spine under the same load it carries all day. When you lie down for a conventional scan, gravity is removed. The muscles relax, vertebrae shift, and a disc that bulges under load may look less severe, or even normal, on a lying-down image.
What standing shows. When you are upright, gravity compresses the discs and loads the joints. Any bulge, narrowing, or shift is visible in its real, functional state. The alignment of the whole spine, from the skull to the pelvis, is captured in a single image so your clinician can see whether a tilt or curve elsewhere is increasing the load on the affected disc.
What lying down can miss. Lying flat removes the weight from the spine. Discs decompress slightly, vertebrae may drift back into a more neutral position, and a misalignment that causes problems during the day can disappear. The scan may report "mild" findings that are actually more significant when you stand.
An EOS scan at ScanAlign captures a full-length standing image of your spine with about 90% less radiation than a standard X-ray, around ten times less. It does not replace MRI, but it adds the weight-bearing context that MRI cannot provide.
A note on MRI. EOS shows bones, joints and alignment under load. For soft tissue detail, such as the disc material itself, the spinal cord, or nerve roots, MRI is usually the better tool. The two complement each other. If your clinician needs to see both structure and alignment, combining MRI findings with a standing EOS image gives the fullest picture.
Wondering whether a standing spine image could help explain your symptoms? You can book a standing spine assessment with a free video consultation first, so we can check it is the right step for you.
Book a free video consultationCan a bulging or herniated disc get better on its own?
Yes, in many cases. Research shows that herniated disc material can shrink over time through a process called natural resorption, where the body gradually absorbs the protruding tissue. Many people find their symptoms ease significantly within weeks to months with conservative approaches such as physiotherapy, gentle movement, and pain management guided by their GP or specialist.
Accurate imaging helps your clinician decide on the best path. If there is a structural misalignment adding extra load to the affected disc, identifying and addressing that factor may be an important part of the plan.
Frequently asked questions
Generally, yes. A herniation means the inner gel has broken through the outer wall, so it is more likely to press on a nerve. But severity depends on location and symptoms, not just the label. Many herniations cause no pain.
It can. If the outer ring continues to weaken, the inner gel may eventually push through. This is not inevitable, and many bulges remain stable for years.
A disc protrusion is a type of herniation where the base of the displaced material is wider than the part that extends outward. It is a moderate stage, between a simple bulge and a full extrusion.
Most herniated discs improve without surgery. Your doctor or specialist will consider surgery only if symptoms are severe, progressive, or not responding to other approaches over several months.
Disc bulges and herniations are very common findings in people without symptoms, especially over the age of 40. The scan finding alone does not mean you need treatment. Symptoms matter more than the image.
In an extrusion, the inner gel has broken through the outer ring but is still connected to the disc. In a sequestration, a fragment has completely separated and is loose in the spinal canal.
EOS shows bones and alignment, not soft tissue detail. It will not show the disc material itself. However, it can reveal disc height loss, vertebral shifts, and overall alignment problems that contribute to disc overload. MRI is the standard tool for seeing the disc directly.
Yes. EOS uses about 90% less radiation than a standard X-ray, around ten times less. It is a very low-dose imaging system.
No. You can self-refer. The process starts with a free video consultation to make sure the scan is appropriate for you.
Pricing details are available on our FAQs and cost page.
Understand how your spine is loaded
A standing whole-body image shows your clinician the full picture. Start with a free video consultation to see if it is the right step for you.
Book a free video consultationSources
- Brinjikji W, Luetmer PH, Comstock B, et al. Systematic literature review of imaging features of spinal degeneration in asymptomatic populations. American Journal of Neuroradiology. 2015;36(4):811-816.
- Fardon DF, Williams AL, Dohring EJ, et al. Lumbar disc nomenclature: version 2.0. The Spine Journal. 2014;14(11):2525-2545.
- National Institute for Health and Care Excellence (NICE). Low back pain and sciatica in over 16s: assessment and management. NICE guideline NG59. 2016 (updated 2020).
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.