
What Is a Distal Femoral Osteotomy, and When Is It Chosen?
A distal femoral osteotomy is a joint-preserving knee surgery that reshapes the lower end of the thigh bone (femur) to correct valgus, or knock-knee, alignment. By shifting the weight-bearing line back towards the centre of the knee, it reduces overload on the outer (lateral) compartment and can delay or avoid a knee replacement in younger, active adults.
Key takeaways
- A distal femoral osteotomy (DFO) corrects valgus knee alignment by reshaping the femur, not the tibia.
- It is a joint-preserving option aimed at younger or more active adults who want to delay knee replacement.
- Accurate standing alignment imaging is essential for pre-operative planning.
- EOS imaging captures a full-leg standing x-ray in a natural weight-bearing position, with about 90% less radiation than a standard x-ray.
- ScanAlign does not perform surgery. It provides the diagnostic imaging that informs your surgical team.
What exactly is a distal femoral osteotomy?
A distal femoral osteotomy is a controlled surgical cut made near the lower end of the femur, just above the knee joint. The surgeon removes or adds a small wedge of bone, then fixes the new position with a plate. This changes the angle of the thigh bone so that the weight-bearing line of the leg passes through the centre of the knee rather than overloading the lateral (outer) compartment.
The word "distal" simply means "the end closest to the knee," and "osteotomy" means "bone cut." The procedure preserves your own joint surfaces rather than replacing them. This is why it is often described as joint-preserving knee surgery.
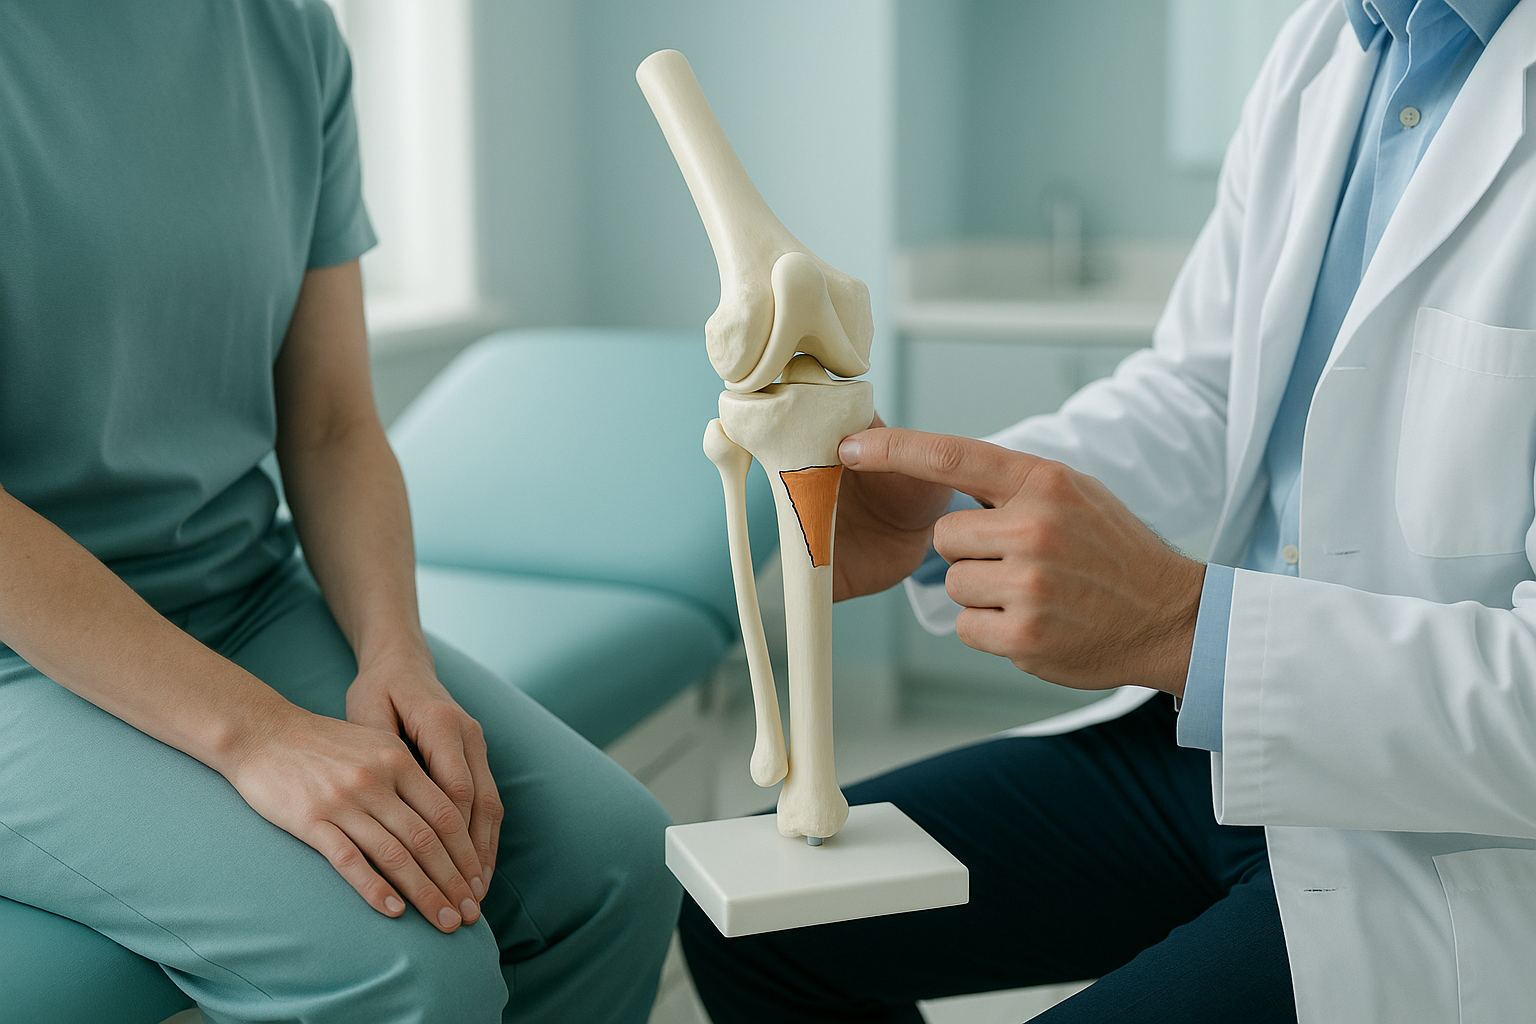
The goal is simple: redistribute load across the knee so that healthy cartilage carries more of the work and damaged cartilage is protected. For many younger adults, this buys valuable years of pain-free activity before a replacement becomes necessary.
How do you know your knee alignment might need correction?
Valgus alignment, commonly called knock knees, is not always obvious. Some people have lived with a mild angle for years before pain develops. The signs below may suggest that the outer compartment of your knee is under excess strain.
These signs do not confirm you need a distal femoral osteotomy. They simply suggest that a proper alignment assessment, ideally standing up, could help identify the structural cause.
What causes valgus knee alignment?
Valgus alignment develops when the weight-bearing line of the leg drifts to the outside of the knee centre. This can happen for several reasons.
Understanding the cause matters because it affects whether the problem sits in the femur, the tibia, or both. When the deformity originates in the femur, a distal femoral osteotomy addresses it at the source. If the tibia is the main contributor, a different procedure, such as knock knee surgery at the tibial level, may be more appropriate. Accurate imaging is the key to making that distinction.
What surgical techniques are used in a distal femoral osteotomy?
Surgeons typically choose between two approaches, depending on the pattern and size of the correction needed.
Opening wedge DFO. The surgeon makes a partial cut through the inner side of the femur, gently opens the gap, and fills it with bone graft or a substitute. A locking plate holds the new angle while the bone heals. This technique allows fine adjustment and preserves bone length.
Closing wedge DFO. A wedge of bone is removed from the outer side of the femur, and the two surfaces are brought together and fixed with a plate. Healing can be faster because bone meets bone directly, but the leg may shorten very slightly.
In both cases, the correction angle is calculated before surgery using precise standing images of the full leg. The surgeon traces the weight-bearing line, measures the current angle, and plans exactly how much correction is needed. This is why high-quality, weight-bearing imaging is so important.
Why does pre-operative planning need standing imaging?
When you lie down for a conventional x-ray or CT scan, gravity stops pulling on your joints. Your muscles relax and the leg may straighten slightly, masking the true valgus angle. A full-leg standing x-ray captures your alignment the way you actually use your legs, under real body weight.
EOS imaging takes this a step further. The scanner captures both legs from hip to ankle in a single upright exposure, with about 90% less radiation than a standard x-ray, around ten times less. Because the image is calibrated, surgeons can take accurate measurements directly from the scan without magnification errors.
At ScanAlign, standing EOS imaging in London, a specialist radiographer positions you naturally in the scanner and produces a detailed report covering your alignment from hip to foot. Your surgeon then uses this to plan the correction angle for a distal femoral osteotomy, or to decide whether a different approach is more suitable.
Considering a femoral osteotomy? Accurate alignment imaging is the starting point.
Book a free video consultationWhen MRI may also be needed. EOS is ideal for bone alignment and joint spacing. If your surgeon needs to assess soft tissue, cartilage thickness, ligaments or nerves in detail, MRI is usually the better tool. The two scans complement each other.
Who is a good candidate for a distal femoral osteotomy?
A DFO is typically recommended for adults who have valgus malalignment with damage mainly in the lateral compartment, but who still have healthy cartilage on the inner side. It suits people who want to stay active and delay a partial or total knee replacement.
- Younger, active adults with valgus alignment
- Lateral compartment cartilage loss with a healthy medial side
- Patients wanting to preserve their own knee joint
- Those with a deformity originating in the femur
- Advanced arthritis affecting both sides of the knee
- Significant stiffness or limited range of motion
- Smokers or those with poor bone healing potential (relative factor)
- Deformity originating in the tibia rather than the femur
Only your orthopaedic surgeon can decide if a DFO is right for you. What imaging provides is the objective alignment data your surgeon needs to make that decision with confidence. If you would like to book pre-operative alignment imaging, a short free video consultation is the first step.
What does recovery from a distal femoral osteotomy look like?
Recovery varies from person to person and depends on the technique used, the size of the correction, and your general health. In broad terms, most people follow a gradual path back to activity.
- Early weeks. Crutches and limited weight-bearing to protect the healing bone. Physiotherapy begins soon after surgery.
- Middle phase. Gradual return to weight-bearing as x-rays confirm bone healing. Swimming and cycling are often reintroduced before impact sports.
- Longer term. Full activity, including running and sport, may be possible once the bone has fully healed and the muscles have recovered strength.
Your surgical team will give you a personalised timeline. ScanAlign does not perform surgery or manage rehabilitation. Its role is to provide the standing alignment imaging that supports both pre-operative planning and, if your surgeon requests it, follow-up comparison scans.
Seek urgent help if needed. If you experience sudden severe knee pain, numbness, weakness in the leg, or loss of bladder or bowel control, contact your GP, call 111, or go to A&E. These symptoms need immediate medical attention, not a scan booking.
Frequently asked questions about distal femoral osteotomy
A distal femoral osteotomy corrects alignment by reshaping the lower femur and is used mainly for valgus (knock-knee) deformities. A high tibial osteotomy reshapes the upper tibia and is used mainly for varus (bow-leg) deformities. The choice depends on where the malalignment originates, which is determined by standing imaging.
It is a significant procedure performed under general anaesthetic. It involves cutting and repositioning bone, then fixing it with a metal plate. However, it is classified as joint-preserving surgery, meaning it keeps your own knee joint intact.
Recovery timelines vary. Most people use crutches for several weeks and gradually return to full weight-bearing over a few months. A full return to sport may take longer. Your surgeon will give you a personalised plan.
That is one of its main purposes. By redistributing load away from the damaged compartment, it can reduce pain and slow further cartilage wear, potentially delaying knee replacement by many years.
When you lie down, gravity is removed and your alignment can look different from when you stand. Standing imaging shows the true weight-bearing angle of the leg, which is the measurement surgeons use to calculate exactly how much correction is needed.
An EOS scan uses about 90% less radiation than a standard x-ray, around ten times less. This makes it a particularly low-dose option for full-leg imaging.
No. ScanAlign is a private, self-pay clinic. You can self-refer without needing a GP or consultant letter. The process begins with a free video consultation.
Pricing details are available on the ScanAlign website. You can find them on the FAQs and cost page.
EOS is designed for bones, joints and alignment. For detailed soft-tissue assessment, including cartilage, ligaments and nerves, MRI is usually the better tool. The two scans work well together.
No. EOS technology is available at a small number of UK clinics. ScanAlign is a private, self-pay clinic at 19 Harley Street, London, focused entirely on standing whole-body alignment imaging.
Understand your alignment before surgery
A standing EOS scan gives your surgeon the precise measurements needed to plan a distal femoral osteotomy. Start with a free video consultation.
Book a free video consultationSources
- Wylie JD, Jones DL, Hartwell MJ, et al. "Distal Femoral Osteotomy for the Valgus Knee: Medial Closing Wedge Versus Lateral Opening Wedge." Arthroscopy, 2016;32(10):2037–2047.
- British Orthopaedic Association. Patient information on osteotomy around the knee. boa.ac.uk
- Deschamps G, Chol C. "Fixed-bearing unicompartmental knee arthroplasty. Patients' selection and operative technique." Orthopaedics & Traumatology: Surgery & Research, 2011;97(6):648–661. (Comparative context for joint-preserving options.)
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.