

Do Flat Feet in Children Need Treating?
Most children with flat feet need no treatment at all. Flat feet are a normal stage of development. The arch usually forms on its own by the time a child is around six to eight years old. Treatment is only worth considering when flat feet cause pain, stiffness or difficulty walking, which is uncommon.
Key takeaways
- Nearly all toddlers have flat feet. It is part of normal growth.
- The arch typically develops between ages three and eight.
- Painless, flexible flat feet rarely need intervention.
- Rigid flat feet, pain, or difficulty walking are reasons to seek advice.
- Standing imaging shows foot and leg alignment under real body weight, which lying-down scans cannot.
What are flat feet in children?
Flat feet means the entire sole of the foot touches the ground when a child stands, with little or no visible arch. In medical terms this is called pes planus. It is extremely common in babies, toddlers and young children because the arch has not yet developed.
A pad of fat under the arch in younger children can also make the foot look flatter than it really is. As the child grows, this fat pad reduces and the muscles and ligaments of the foot strengthen, allowing the arch to appear.

When does the arch develop in children?
The arch usually begins to form around age three and continues developing until roughly age six to eight. Some children take a little longer, and some adults never develop a prominent arch at all, yet have no pain or functional problems.
Because the arch develops gradually, it is generally too early to be concerned about flat feet in a toddler. A GP or paediatric specialist will typically reassess at later stages rather than intervene early.
What signs suggest flat feet might be a problem?
Flat feet on their own are not a problem. They only become a concern when they cause symptoms or affect how a child moves. Look for the following.
Complaints of sore feet, ankles, knees or legs, especially after activity.
Walking on the outer edges of the feet, tripping often, or tiring quickly.
The foot feels rigid, or the child cannot stand on tiptoe comfortably.
Flat foot on just one side can suggest a structural difference worth investigating.
If your child has flat feet but no pain and moves freely, the most likely outcome is that the arches will develop in their own time.
What is the difference between flexible and rigid flat feet?
Flexible flat foot is by far the most common type. The arch disappears on standing but reappears when the child sits, stands on tiptoe, or when you gently lift the big toe. This is the type that almost always resolves on its own.
Flexible flat foot is normal in young children. The foot is supple, painless and the arch returns when the foot is not bearing weight. The tiptoe test (asking the child to rise onto their toes) is a simple way to check. If an arch appears on tiptoe, the flat foot is almost certainly flexible.
No treatment is usually needed. Supportive, well-fitting shoes are helpful, but expensive insoles or special footwear are rarely necessary.
Rigid flat foot is much less common. The foot stays flat whether the child is standing, sitting or on tiptoe. It can be caused by a bony bridge between two foot bones, known as a tarsal coalition, or other structural conditions.
Rigid flat feet are more likely to cause pain or difficulty walking. They warrant a proper assessment, and imaging can help a specialist understand the underlying structure.
How does standing imaging help assess flat feet in children?
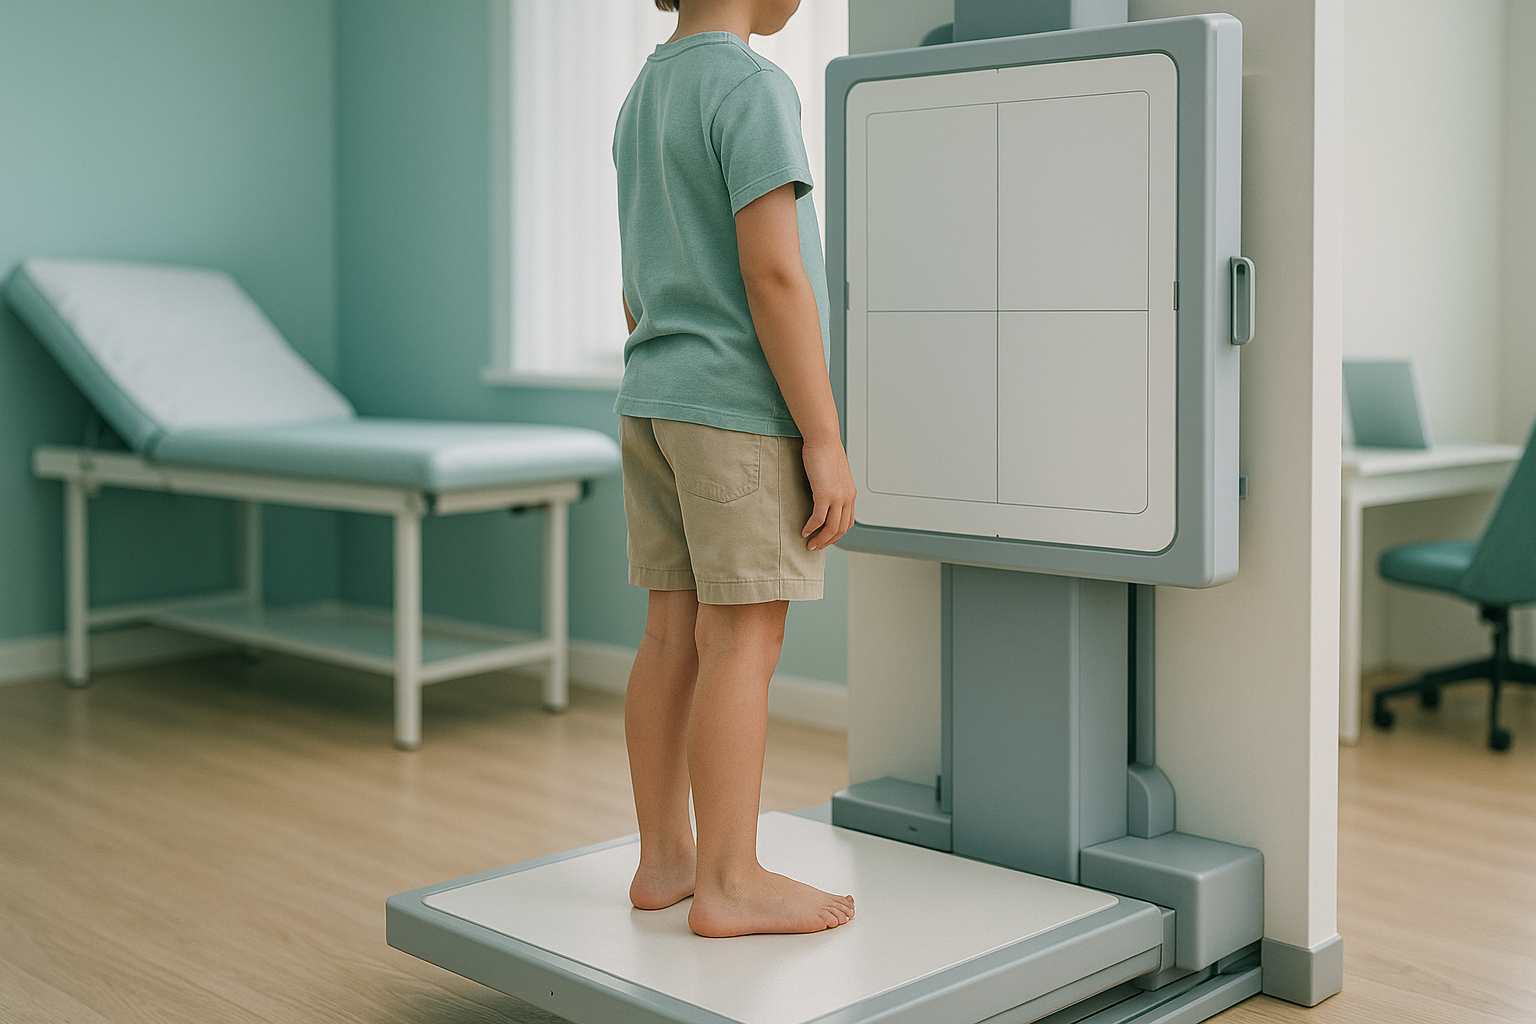
Standing, weight-bearing imaging shows the bones and joints of the foot and leg in the position they actually work in. When a child lies down for a standard X-ray, gravity is removed, muscles relax, and the foot can look different from how it behaves in real life.
An EOS scan captures the full lower limbs while the child stands naturally. This lets a specialist see how the feet, ankles, knees and hips relate to each other as a connected chain. A flat foot can change the alignment further up the leg, and standing imaging reveals those knock-on effects in a single image.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. For children, where minimising radiation exposure matters most, this is an important advantage. Learn more about paediatric imaging at ScanAlign.
When is MRI better? EOS shows bones, joints and alignment. If a specialist suspects a soft-tissue, ligament or tendon problem in your child's foot, MRI is usually the better tool for that. The two types of imaging answer different questions.
Do children with flat feet need insoles or orthotics?
For most children with painless, flexible flat feet, the evidence does not support routine use of insoles or orthotics. Multiple studies have found that arch supports do not speed up the natural development of the arch.
Orthotics may help if a child has painful flat feet or a specific structural issue identified by a specialist. In those cases, they are used to manage discomfort, not to "fix" the arch. Read more about orthotics and overpronation.
Well-fitting, supportive shoes are more important than expensive inserts. Letting younger children go barefoot on safe surfaces can actually encourage natural arch and muscle development.
- Your child has foot, ankle or knee pain
- The foot is stiff or rigid
- They cannot stand on tiptoe
- Only one foot is flat
- Symptoms are getting worse with age
- Both feet are flat but pain-free
- Your child is under six
- An arch appears on tiptoe
- They run and play normally
- There is no stiffness
Not sure whether your child's flat feet need looking into? A short video consultation with our specialist radiographer can help you decide whether imaging is worthwhile, or whether reassurance is the right answer.
Book a free video consultationWhat general advice helps children with flat feet?
For the vast majority of children, the best approach is simply time and reassurance. There are a few practical things that can support healthy foot development.
- Barefoot time. Walking barefoot on grass, carpet or sand helps strengthen the small muscles of the foot.
- Well-fitting shoes. Shoes should be the right size and offer support without being rigid. Avoid hand-me-down shoes that have moulded to another child's foot.
- Stay active. Running, climbing and varied movement all help build foot and leg strength naturally.
- Watch, do not worry. Reassess with your GP if pain develops or if the feet have not changed by age eight to ten.
If your child does need further investigation, a gait analysis or standing alignment scan can show how the feet relate to the knees, hips and overall posture under real weight-bearing conditions.
Frequently asked questions about flat feet in children
Most specialists suggest waiting until at least age six to eight before considering flat feet a concern. The arch is still developing before that age. If your child has pain or stiffness at any age, it is worth mentioning to your GP.
Ask your child to stand on their tiptoes. If an arch appears along the inner edge of the foot, the flat foot is likely flexible and normal. If the foot stays completely flat, or if your child cannot rise onto their toes, mention it to your GP.
Not always. Most toddlers develop an arch over time, but some children and adults have flat feet throughout life with no ill effects. A small number have a structural cause that may need specialist input.
There is a genetic component. If parents or close relatives have flat feet, a child is more likely to have them too. This does not mean they will cause problems.
For painless, flexible flat feet, special shoes are not necessary. Well-fitting, supportive everyday shoes are enough. Going barefoot in safe environments is also helpful for building foot strength.
In some cases, flat feet can affect how the leg is aligned, potentially contributing to discomfort further up the chain at the knee, hip or lower back. Standing alignment imaging can show whether this is happening.
A tarsal coalition is an abnormal bridge of bone, cartilage or fibrous tissue between two bones in the back of the foot. It can cause a rigid flat foot that does not correct on tiptoe. It is uncommon and usually diagnosed with imaging.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. This makes it particularly suitable for children, where keeping radiation exposure as low as possible is a priority. Learn more about paediatric imaging at ScanAlign.
No referral is needed. You can book a paediatric assessment directly. We always recommend discussing results with your child's GP or specialist afterwards.
Pricing details are available on our frequently asked questions page.
Wondering whether your child's flat feet need a closer look?
A free video consultation with our specialist radiographer will help you understand whether imaging is the right next step, or whether reassurance is all that is needed.
Book a free video consultationSources
- NHS. Flat feet. nhs.uk/conditions/flat-feet (accessed 2024).
- Pfeiffer M, et al. Prevalence of flat foot in preschool-aged children. Pediatrics. 2006;118(2):634-639.
- Evans AM, Rome K. A Cochrane review of the evidence for non-surgical interventions for flexible pediatric flat feet. European Journal of Physical and Rehabilitation Medicine. 2011;47(1):69-89.
Written by Abbas Dhami (Specialist Diagnostic Radiographer), ScanAlign, low dose standing imaging, 19 Harley Street, London.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.