
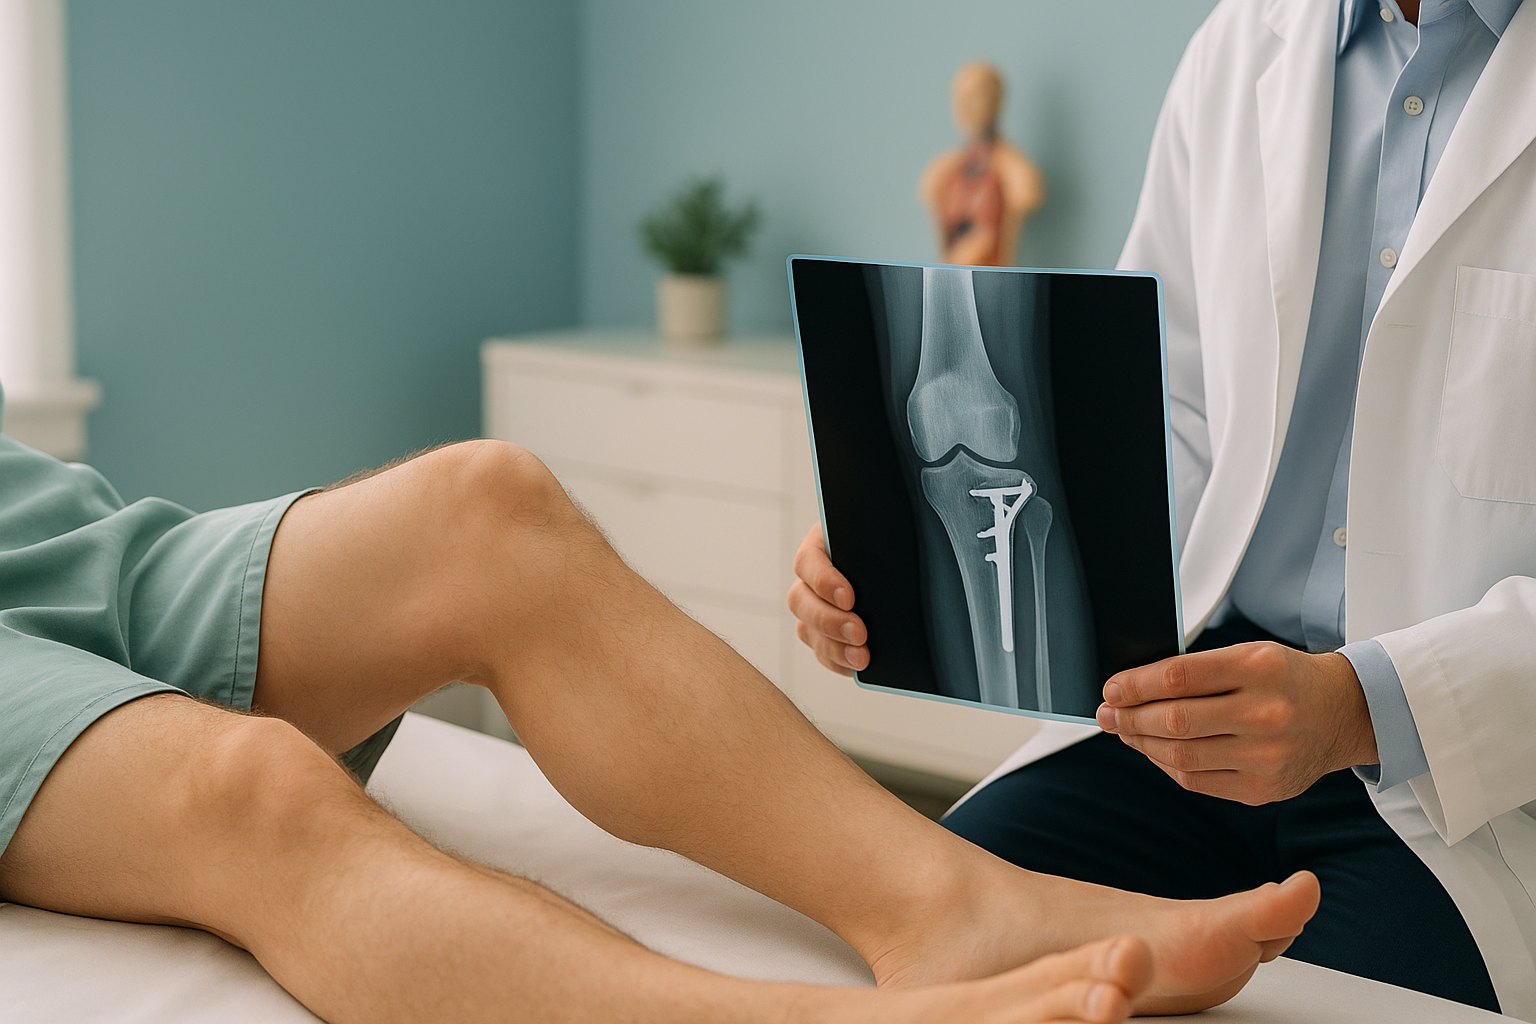
What Is a High Tibial Osteotomy, and Who Is It Suitable For?
A high tibial osteotomy is a knee realignment surgery that reshapes the top of the shinbone to shift weight away from a worn inner knee compartment. It is designed for younger, active adults who want to preserve their natural joint and delay or avoid a knee replacement. Precise standing imaging is essential for planning the correction.
Key takeaways
- High tibial osteotomy corrects bow-leg alignment to offload the worn inner side of the knee.
- It is best suited to active adults with early to moderate arthritis in one compartment only.
- The surgery preserves your own joint, potentially delaying a knee replacement by many years.
- Accurate pre-operative planning depends on a full-leg standing x-ray that maps the true weight-bearing line.
- EOS imaging uses about 90% less radiation than a standard x-ray, around ten times less.
What does a high tibial osteotomy do to the knee?
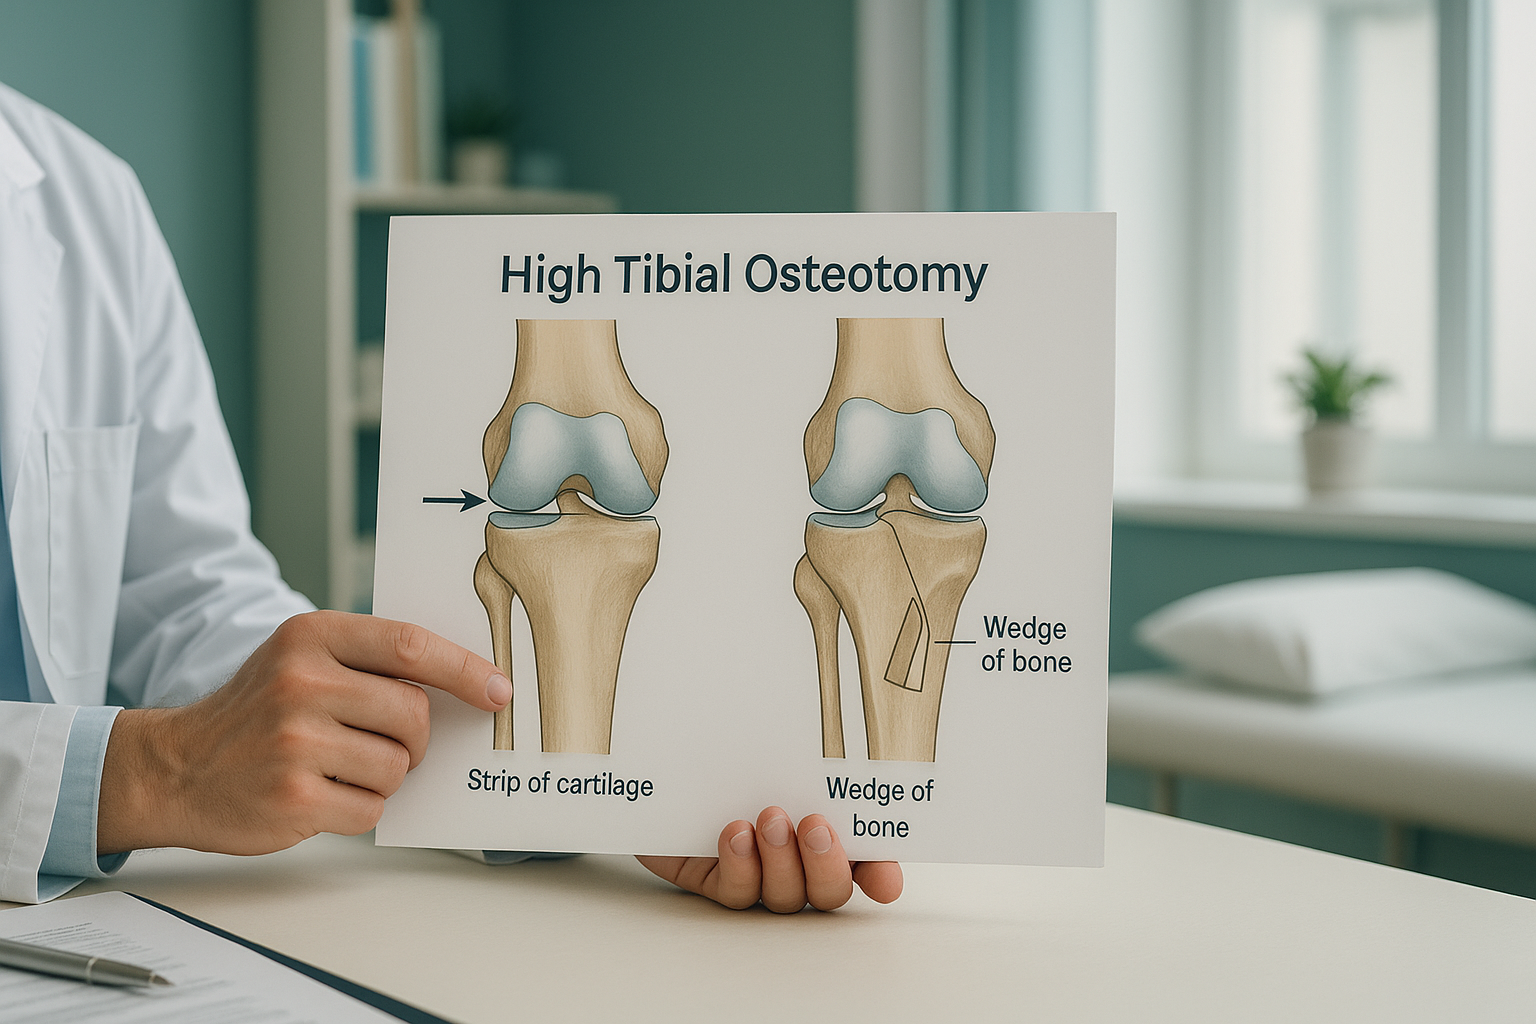
A high tibial osteotomy (often shortened to HTO) is a planned, controlled cut through the upper part of the tibia, your shinbone. The surgeon opens or closes a small wedge of bone to change the angle of the leg. This shifts the body's weight-bearing line from the damaged inner (medial) compartment of the knee to the healthier outer side.
Think of it like straightening a wonky table leg. When the leg is bowed inward, all your weight presses through one narrow strip of cartilage. By correcting the angle, the load spreads more evenly. The goal is joint preservation. Rather than removing the damaged surfaces and fitting an artificial joint, HTO keeps your own knee intact and working.
HTO is most commonly used for varus malalignment, the medical term for bow legs. If your knees angle outward instead (knock knees, or valgus alignment), a different procedure may be more appropriate. You can read more about knock knee surgery separately.
Who is a good candidate for a high tibial osteotomy?
The ideal candidate is a younger, active adult with early to moderate arthritis that is limited to the inner compartment of the knee. HTO is considered a joint-preserving option, so it works best when there is still healthy cartilage on the outer side.
- Active adults, typically under 60
- Bow-leg (varus) alignment
- Wear limited to the inner compartment
- Stable knee ligaments (or combined with ligament repair)
- Good range of movement in the knee
- Motivated to complete rehabilitation
- Widespread arthritis across the whole knee
- Severe cartilage loss on the outer side too
- Very limited knee bend (significant stiffness)
- Inflammatory arthritis such as rheumatoid disease
- Significant obesity that would overload the correction
Your surgeon will consider several factors before recommending HTO. Age alone does not rule you in or out, but the procedure is generally aimed at people who are too young or too active for a knee replacement to be the best first option.
What are the types of high tibial osteotomy?
There are two main techniques. Both achieve the same goal of realigning the leg, but they do it in different ways.
Opening wedge osteotomy is the more common technique today. The surgeon makes a cut on the inner side of the tibia and gradually opens a gap to correct the angle. A metal plate holds the bone in its new position while it heals. A bone graft or substitute may fill the gap.
Advantages include precise control of the correction and the ability to adjust the angle during surgery. It also avoids disturbing the outer compartment of the knee.
Closing wedge osteotomy removes a small wedge of bone from the outer side of the tibia, then closes the gap to straighten the leg. This technique has a long track record and heals quickly because the two bone surfaces are pressed together.
It is sometimes preferred when a large correction is needed or when the outer bone quality is better. However, it does change the height of the joint line slightly, which some surgeons prefer to avoid.
Your surgeon will choose the technique based on how much correction is needed, your bone quality, and whether any other procedures are being done at the same time.
What are the signs you might need a knee osteotomy?
Knee osteotomy is not usually the first thing your doctor considers. It typically enters the conversation after simpler measures have not given enough relief. Common signs include:
If you also experience sudden locking, giving way, numbness, weakness, or loss of bladder or bowel control, please seek urgent medical attention from your GP, 111, or A&E. These symptoms need prompt assessment rather than routine imaging.
Why does pre-operative planning need standing imaging?
Accurate planning is the single most important factor in a successful high tibial osteotomy. The surgeon needs to know exactly where your weight-bearing line falls and how much correction to apply. That information can only come from images taken while you are standing up, loaded through your skeleton as you would be in real life.
When you lie down for a standard x-ray or MRI, gravity is removed. Your muscles relax, joints decompress, and the true angle of your leg can shift. A full-leg standing x-ray captures the entire limb from hip to ankle in one image, under full body weight. This reveals the real mechanical axis your surgeon needs to plan around.
At ScanAlign, private standing imaging, EOS technology captures this full-length standing view with about 90% less radiation than a standard x-ray, around ten times less. It produces a single, calibrated image of both legs simultaneously, so the surgical team can compare sides and plan the correction with confidence.
Considering HTO surgery? Your surgeon may need standing alignment imaging before finalising the surgical plan. We can arrange this quickly, and your images can be shared directly with your surgical team.
Book a free video consultationWhen MRI is the better tool: EOS shows bones, joints and alignment clearly. If your surgeon also needs to assess soft tissue, cartilage, meniscus tears or ligament damage, MRI is usually the better choice. Many patients having HTO planning will need both types of imaging.
What does tibial osteotomy recovery look like?
Recovery from a high tibial osteotomy is a gradual process. The bone needs time to heal in its new position, and the muscles around the knee need rebuilding. Everyone recovers at a different pace, but here is a general outline of what to expect.
You will likely use crutches and may wear a brace. Weight-bearing is usually limited at first and increased gradually under your physiotherapist's guidance.
Bone healing progresses. Most people can begin putting more weight through the leg and transition off crutches. Gentle exercises help restore range of movement.
Strengthening work increases. Many people return to low-impact activities, office-based work, and driving during this period.
Return to sport and higher-impact activities is often possible, depending on the sport and your surgeon's guidance. Full recovery can take up to a year.
Follow-up imaging after the osteotomy can confirm that the bone has healed and the alignment is where the surgeon intended. Standing x-rays are especially useful for checking the corrected mechanical axis once you are fully weight-bearing again.
Frequently asked questions about high tibial osteotomy
Neither is universally better. HTO preserves your own joint and is aimed at younger, active people with wear on one side of the knee. A knee replacement is more appropriate when arthritis affects the whole joint. Your surgeon will help decide which is right for your situation.
Results vary. Many studies report the benefits lasting ten years or longer, particularly when patient selection and alignment correction are accurate. Some people may eventually need a knee replacement later in life, but HTO can significantly delay that step.
Many patients do return to sport, including running, cycling and skiing. The timeline depends on healing, your rehabilitation, and your surgeon's advice. Return to high-impact activities is typically considered from around nine to twelve months.
In an opening wedge, the surgeon cuts the bone and opens a gap on the inner side to correct the angle. In a closing wedge, a small piece of bone is removed from the outer side and the gap is closed. Both aim to straighten the leg and redistribute load.
A full-leg standing image shows the mechanical axis from hip to ankle under real body weight. This is the only reliable way to measure the exact angle of malalignment and plan how much correction is needed. Lying-down images can underestimate the true deformity.
Yes. EOS uses about 90% less radiation than a standard x-ray, around ten times less. It is a well-established system used in hospitals worldwide. You can read more about safety and what to expect on our FAQs page.
No. You can self-refer as a private patient. If your surgeon or physiotherapist would like to refer you directly, they can refer a patient for imaging through our clinician registration page.
We do not list prices on individual pages. You can find up-to-date information about scan costs, payment and what is included on our FAQs page.
HTO is primarily designed for varus (bow-leg) malalignment. If you have valgus (knock-knee) alignment, a different type of osteotomy around the knee may be more suitable. Read more about knock knee surgery for details on that correction.
Absolutely. Many patients and surgical teams arrange standing alignment imaging ahead of the operation so the plan is finalised well in advance. You can book pre-operative alignment imaging through a free video consultation to get started.
Need standing alignment imaging for your knee?
Whether you are exploring a high tibial osteotomy or your surgeon has asked for pre-operative planning images, we can help.
Book a free video consultationWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- Brinkman J-M, Lobenhoffer P, Agneskirchner JD, et al. "Osteotomies around the knee: patient selection, stability of fixation and bone healing in high tibial osteotomies." The Journal of Bone & Joint Surgery (British Volume), 2008.
- W-Dahl A, Toksvig-Larsen S, Roos EM. "Association between knee alignment and knee pain in patients surgically treated with high tibial osteotomy." Knee Surgery, Sports Traumatology, Arthroscopy, 2009.
- National Institute for Health and Care Excellence (NICE). "Osteoarthritis: care and management." Clinical guideline CG177, updated 2022.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.