
Why Does My Kneecap Keep Dislocating (Patella Subluxation)?
Patella subluxation happens when your kneecap partially slips out of the groove at the front of your thigh bone and then slides back. It is usually caused by a combination of a shallow groove, loose ligaments, and the way your leg bones are aligned. Standing whole-body imaging can reveal alignment factors that lying-down scans miss.
Key takeaways
- The kneecap sits in a groove called the trochlea. If that groove is too shallow, or the soft tissue around it is too loose, the kneecap can slip out of place.
- Once a dislocation has happened, the risk of it happening again rises significantly.
- Bone alignment from the hip down to the foot plays a major role, but standard lying-down imaging cannot show that alignment under load.
- An EOS standing scan captures the full leg in weight-bearing, giving your specialist the measurements they need to plan the right next step.
If your kneecap has slipped sideways even once, you know the sickening lurch it produces. For some people it becomes a recurring pattern, sometimes called an unstable kneecap. The medical term for a partial slip is patella subluxation. A full dislocation is when the kneecap moves completely out of the groove and does not come back on its own.
Understanding why it keeps happening is the key to stopping it. And that means looking at more than just the knee itself.
What does patella subluxation feel like?
It feels like your kneecap suddenly shifts to the outer side of your knee. You may feel a pop, a catch, or a sense of giving way, often followed by swelling and a deep ache at the front of the knee.
The kneecap visibly moves to the outside of your knee, sometimes called the "J sign" as the knee straightens.
Your knee suddenly buckles or feels as though it cannot support you, especially on stairs or uneven ground.
After an episode the knee swells quickly. You may find it painful to bend or straighten the leg fully.
A strong sense of anxiety or muscle guarding whenever you feel the kneecap start to move, even if it does not fully dislocate.
These episodes can range from mild and self-correcting to severe enough that someone else needs to help push the kneecap back. If your kneecap does not return on its own or your knee locks, seek urgent medical attention at A&E.
Repeated subluxation events are sometimes confused with patellar maltracking, where the kneecap drifts slightly off-centre without fully dislocating. The two overlap, but true instability carries a higher risk of cartilage damage over time.
What causes a kneecap to keep dislocating?
Kneecap dislocation recurrence is driven by a mix of structural and alignment factors, not just one single problem. Your body works as a connected chain from feet to head. When the bones of the leg are rotated, tilted, or set at an unusual angle, the kneecap is pulled away from its groove every time you stand or move.
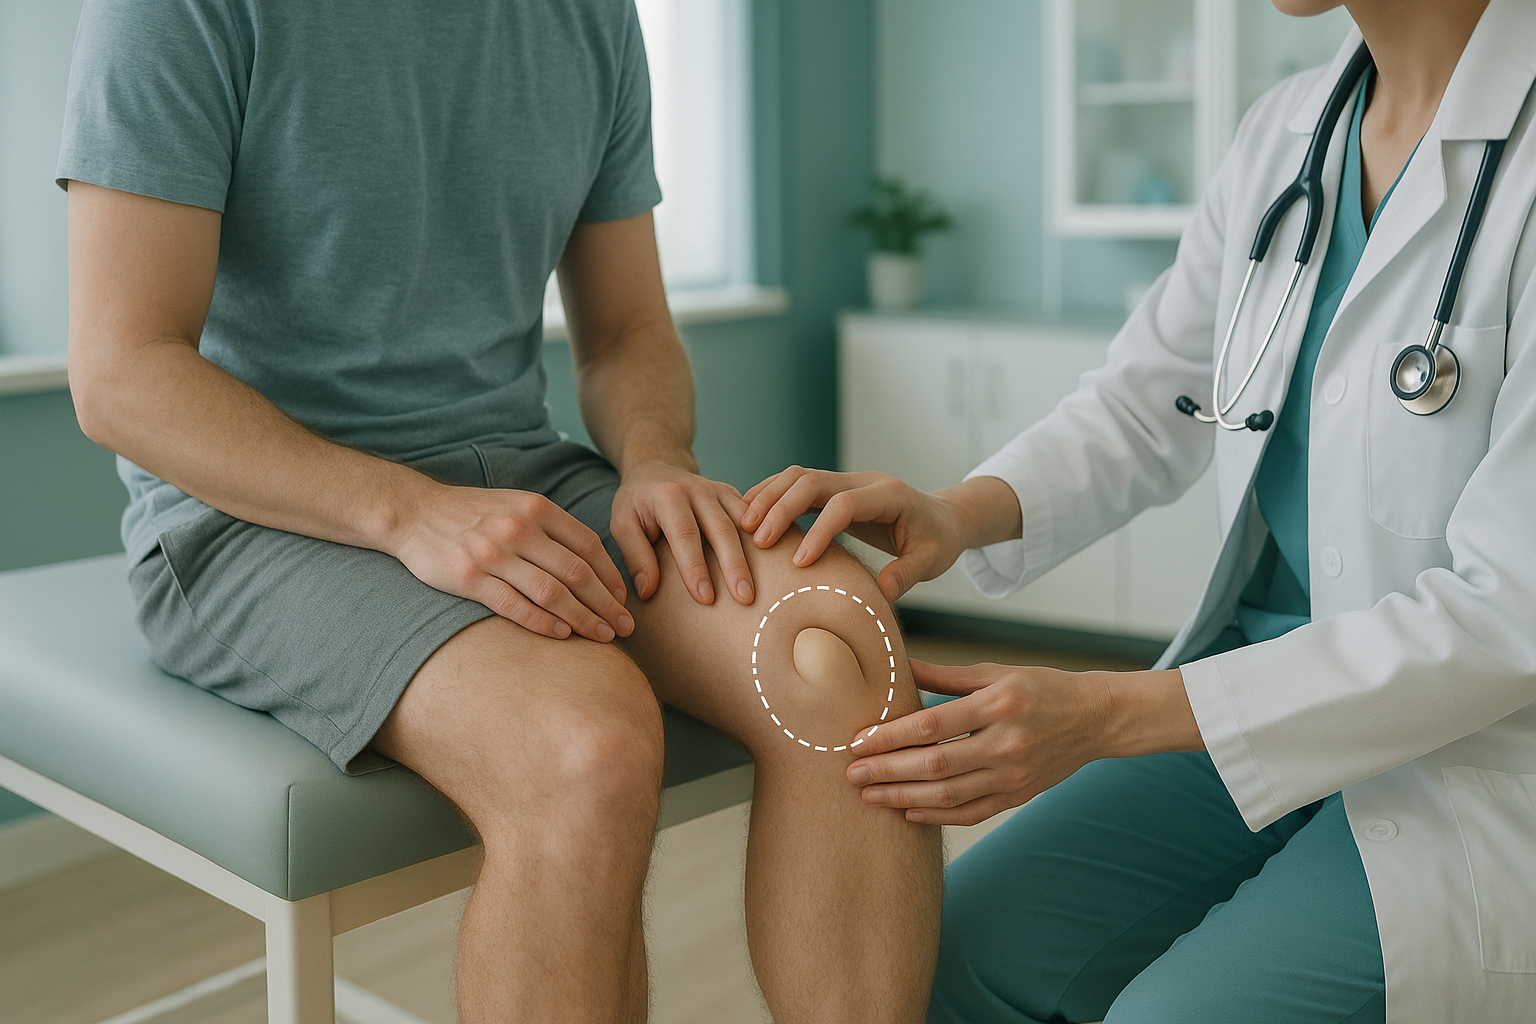
A shallow or flat groove in the thigh bone, meaning the kneecap has less of a rail to sit in.
The medial patellofemoral ligament (MPFL) is the main restraint holding the kneecap on the inner side. It often tears during the first dislocation.
A kneecap that sits higher than normal, so it enters the groove later during bending and is less stable at the start of movement.
Increased femoral anteversion in adults or excessive tibial torsion can change the angle of pull on the kneecap.
People with generalised joint laxity, sometimes part of hypermobility syndrome, are also at greater risk because their ligaments stretch more easily.
The important point is that these factors act together. A shallow groove alone might not cause problems if the ligaments and alignment are normal. But combine two or three of these elements and the kneecap has much less support.
Why does kneecap dislocation keep coming back?
Each dislocation stretches or tears the MPFL further, reducing the restraint that kept the kneecap in place. Research shows that after a first patellar dislocation, the chance of it happening again is significant, and that risk climbs higher with each subsequent episode.
Structural factors such as trochlear dysplasia and rotational malalignment do not improve on their own. If these underlying causes are not identified, physiotherapy and bracing may not be enough to prevent recurrence. That is why accurate imaging is so important before deciding on a management plan.
How does standing imaging help with an unstable kneecap?
Standing imaging reveals the rotational and alignment picture that lying-down scans cannot show. When you lie flat for a conventional X-ray, CT, or MRI, your muscles relax and gravity is removed. The angles between your hip, knee, and ankle change. Measurements taken in that position may not match what is actually happening when you stand and walk.
An EOS scan captures the full skeleton from head to foot while you stand. Your muscles are active, your joints are loaded, and your natural alignment is on full display. This lets your specialist measure the relationship between femoral version, tibial torsion, and the position of the kneecap under real-world conditions, with about 90% less radiation than a standard X-ray, around ten times less.
Lying-down X-rays and CT scans relax the muscles around the knee. The kneecap may sit more centrally than it does when you are upright. Important rotational measurements can appear normal in a position that removes the effect of gravity and body weight. This can lead to an incomplete picture of the instability.
ScanAlign standing EOS imaging captures this full weight-bearing picture in a single scan. It gives your orthopaedic surgeon or physiotherapist the alignment data they need to decide whether bracing, targeted rehabilitation, or surgical options like MPFL reconstruction are most appropriate.
When MRI is the better tool: EOS shows bones, joints, and alignment under load. If your specialist needs to assess cartilage damage, the MPFL itself, or other soft-tissue structures around the knee, MRI is usually the better choice. The two scans complement each other.
What are the next steps for recurrent patellar dislocation?
The right path depends entirely on what is causing the instability. That is why detailed imaging comes first. Common approaches your specialist may consider include targeted physiotherapy to strengthen the muscles that control the kneecap, bracing for activity, or surgical stabilisation procedures such as MPFL reconstruction or trochlear groove-deepening surgery. ScanAlign does not provide treatment. It provides the diagnostic imaging that helps your specialist choose the best route for you.
Not sure whether a standing alignment scan would help your kneecap problem? Talk to our specialist radiographer for free, with no obligation.
Book a free video consultationFrequently asked questions about patella subluxation
Subluxation means the kneecap partially slides out of the trochlear groove and then returns on its own. A full dislocation means it moves completely out and may need to be pushed back into place manually. Both are forms of patellar instability.
Yes. Some people have structural factors, such as a shallow trochlear groove or naturally loose ligaments, that allow the kneecap to slip during everyday activities like walking downstairs or turning quickly.
Strengthening the inner quadriceps muscle can help control the kneecap. However, if underlying bone alignment is a significant factor, physiotherapy alone may not prevent further dislocations. Accurate imaging helps your physiotherapist decide what is realistic.
MPFL reconstruction is a surgical procedure that replaces the torn medial patellofemoral ligament with a graft. It restores the main restraint that holds the kneecap on the inner side. Your surgeon will need precise alignment measurements before recommending this.
Trochlear dysplasia is a condition where the groove at the front of the thigh bone is shallower or flatter than normal. This means the kneecap has less of a channel to sit in, making it more likely to slip sideways.
As the knee straightens, the kneecap rides higher out of the groove and loses the bony support that keeps it centred. If the groove is shallow or the kneecap sits too high (patella alta), this transition is when subluxation is most likely to happen.
No. ScanAlign is a private self-pay clinic and you can self-refer. You start with a free video consultation with our specialist radiographer, who will discuss whether a scan is appropriate for you.
An EOS scan uses about 90% less radiation than a standard X-ray, around ten times less. It is one of the lowest-dose imaging options available for full-body skeletal assessment.
Yes. Your body is a connected chain. Increased inward twist of the thigh bone or outward twist of the shin bone changes the angle of pull on the kneecap. Flat feet can also contribute. A full standing scan captures these relationships in one image.
You can book a rotation and alignment scan through our booking page. Pricing details are discussed during your free video consultation.
Find out what is behind your kneecap instability
A free video consultation with our specialist radiographer will help you understand whether a standing alignment scan is the right next step.
Book a free video consultationWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- Fithian DC, Paxton EW, Stone ML et al. "Epidemiology and natural history of acute patellar dislocation." Am J Sports Med. 2004;32(5):1114-1121.
- Dejour H, Walch G, Nove-Josserand L, Guier C. "Factors of patellar instability: an anatomic radiographic study." Knee Surg Sports Traumatol Arthrosc. 1994;2(1):19-26.
- NHS. "Dislocated kneecap." nhs.uk. Available at: https://www.nhs.uk/conditions/dislocated-kneecap/
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.