
What Is Blount's Disease, and When Do Bow Legs Need Treating?
Blount's disease is a growth plate disorder at the top of the shinbone (tibia) that causes one or both legs to bow progressively. Unlike normal bowing in toddlers, which straightens on its own, Blount's disease gets worse over time without treatment. A standing full-leg standing x-ray is the clearest way to assess the bowing and track whether it is progressing.
Key takeaways
- Blount's disease (tibia vara) is a progressive bowing of the legs caused by abnormal growth at the inner part of the upper tibia.
- It is different from normal infant bowing, which almost always corrects by age three to four.
- Early detection matters. The younger it is caught, the simpler the treatment options tend to be.
- Standing imaging shows the true weight-bearing shape of the legs, which lying-down scans can understate.
- Treatment ranges from bracing to surgery, depending on age and severity.
What does Blount's disease look like?
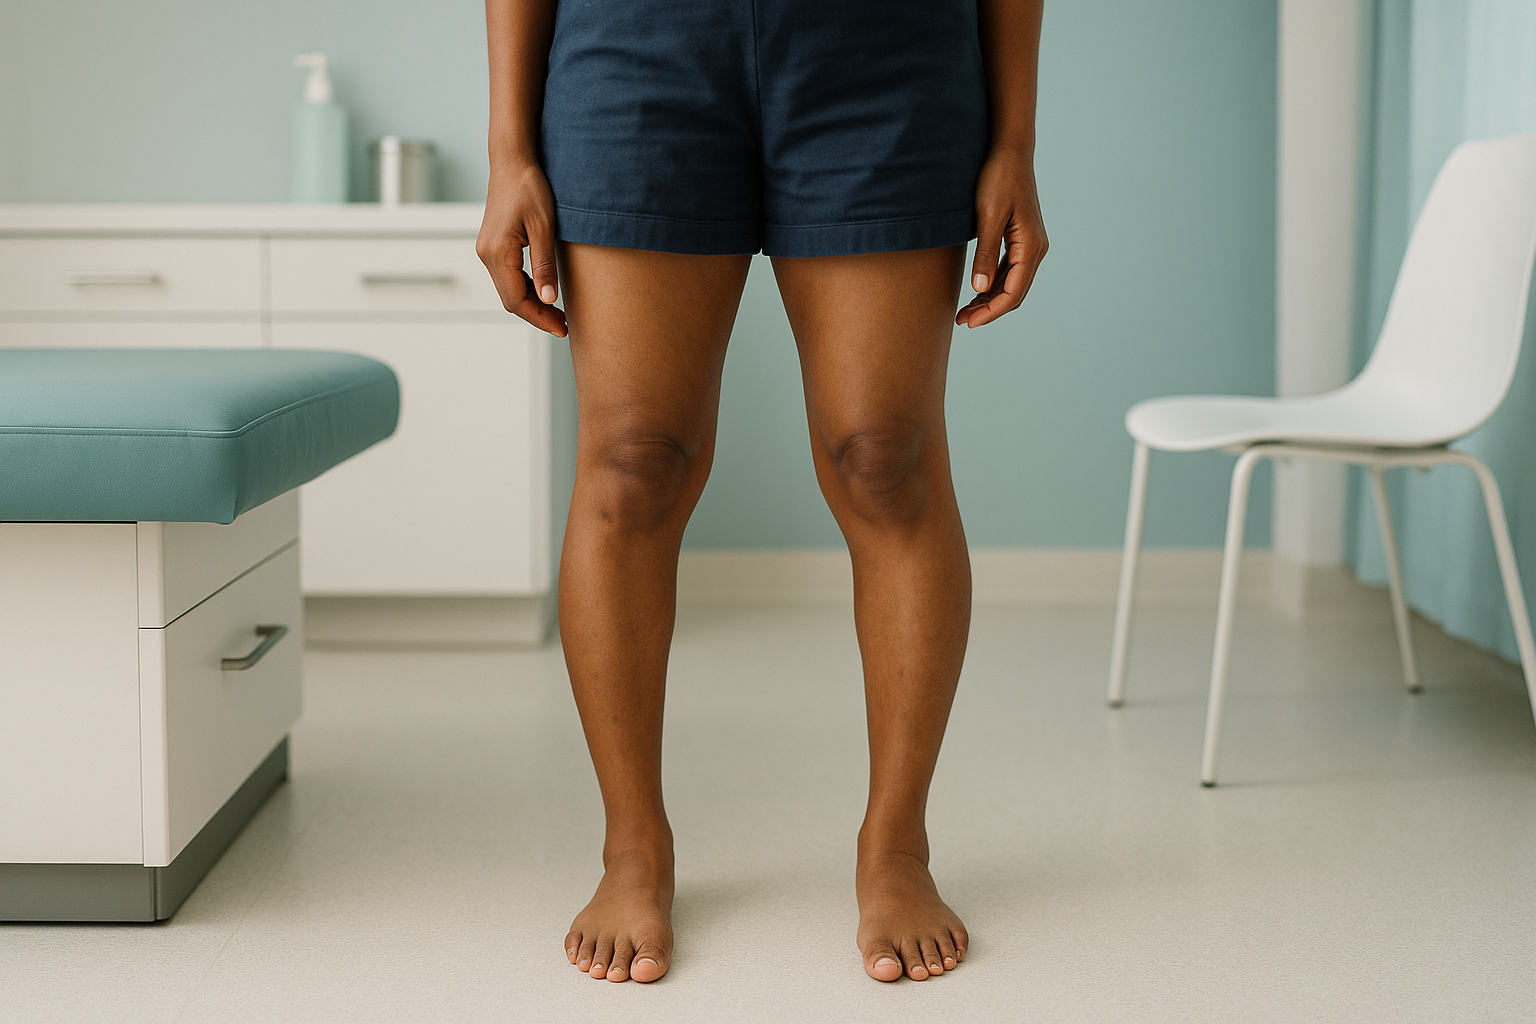
Blount's disease causes a visible inward bowing of one or both shins, usually just below the knee. The bowing is sharper and more angular than the gentle curve you see in a toddler who is still developing. Over time, the affected leg may also develop an inward twist, making the foot point inward. Children and adolescents may limp, complain of knee pain, or simply look "more bowed" than their peers.
One or both legs bow outward at the knee, and the curve deepens over months or years rather than improving.
Pain along the inner knee, sometimes with a feeling that the knee "gives way" during walking or running.
A noticeable limp or waddling walk, especially if only one leg is affected.
The foot on the affected side may turn inward because of tibial torsion (a twist in the shinbone).
How is Blount's disease different from normal bow legs?
Almost all babies are born with some degree of bowing. This is called physiological genu varum, and it straightens naturally by around age three or four. In many children, the legs even swing into a mild knock knees phase before settling into their adult alignment.
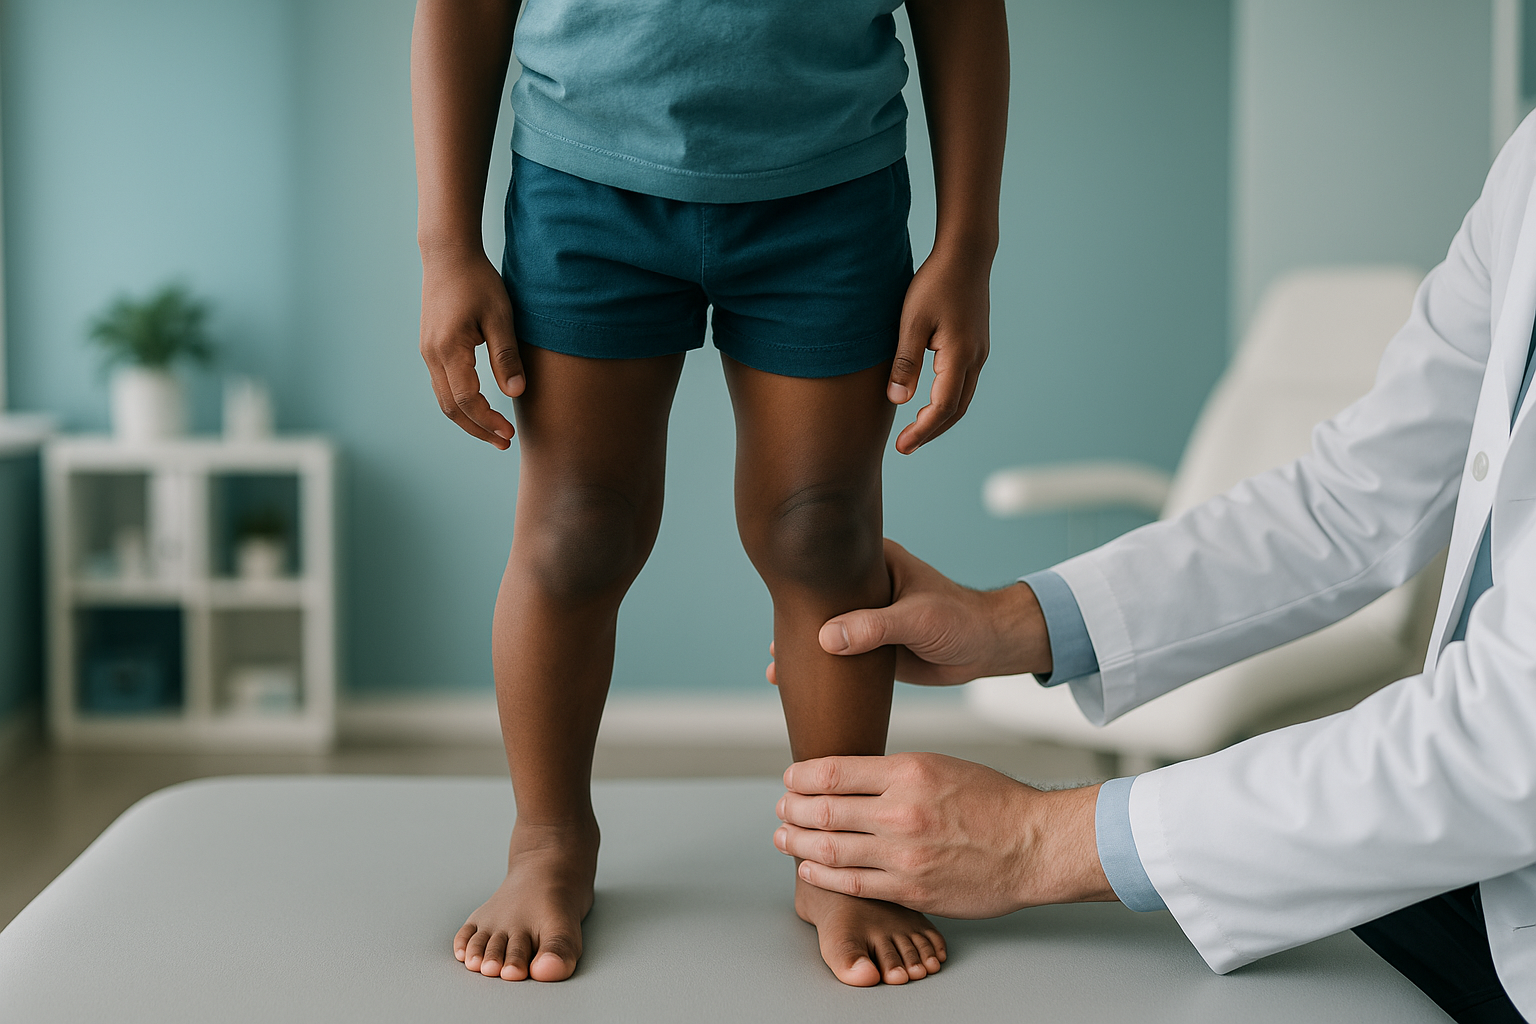
Blount's disease is different because the bowing does not improve. It worsens. The growth plate on the inner side of the upper tibia (the proximal tibial physis) stops growing normally, while the outer side keeps going. This creates an increasingly sharp angle just below the knee. A child whose bow legs are getting worse after age two, or are clearly worse on one side, should be assessed.
What causes Blount's disease?
The exact cause is not fully understood, but it centres on excessive pressure on the growth plate at the top of the tibia. This abnormal loading disrupts normal bone development. Several factors raise the risk.
Higher body weight puts more stress on the growth plate, making it a strong risk factor for both infantile and adolescent forms.
Children who walk very early may load the growth plate before it is ready, particularly if combined with higher body weight.
Blount's disease is more common in certain populations and can run in families, suggesting a hereditary component.
Are there different types of Blount's disease?
Yes. Blount's disease is usually classified by the age it appears. The two main forms behave differently and respond to different approaches.
Infantile tibia vara appears before age four. It often affects both legs. If detected early, bracing can be effective. If bowing continues beyond age four or is severe, surgery is usually considered. This is the more common form overall.
Adolescent Blount's disease develops after age ten, typically in one leg only. It is strongly linked to higher body weight. Bracing is rarely effective at this stage because much of the skeletal growth has already happened. Surgery, such as guided growth or an osteotomy (a controlled bone cut to correct the angle), is the usual treatment path.
How is Blount's disease diagnosed with imaging?
Diagnosis relies on a clinical examination plus imaging of the full legs. An x-ray of the upper tibia shows characteristic changes at the growth plate, including beaking or widening on the inner side. Your consultant will look at the overall leg alignment to measure how severe the bowing is and whether it has changed since the last image.
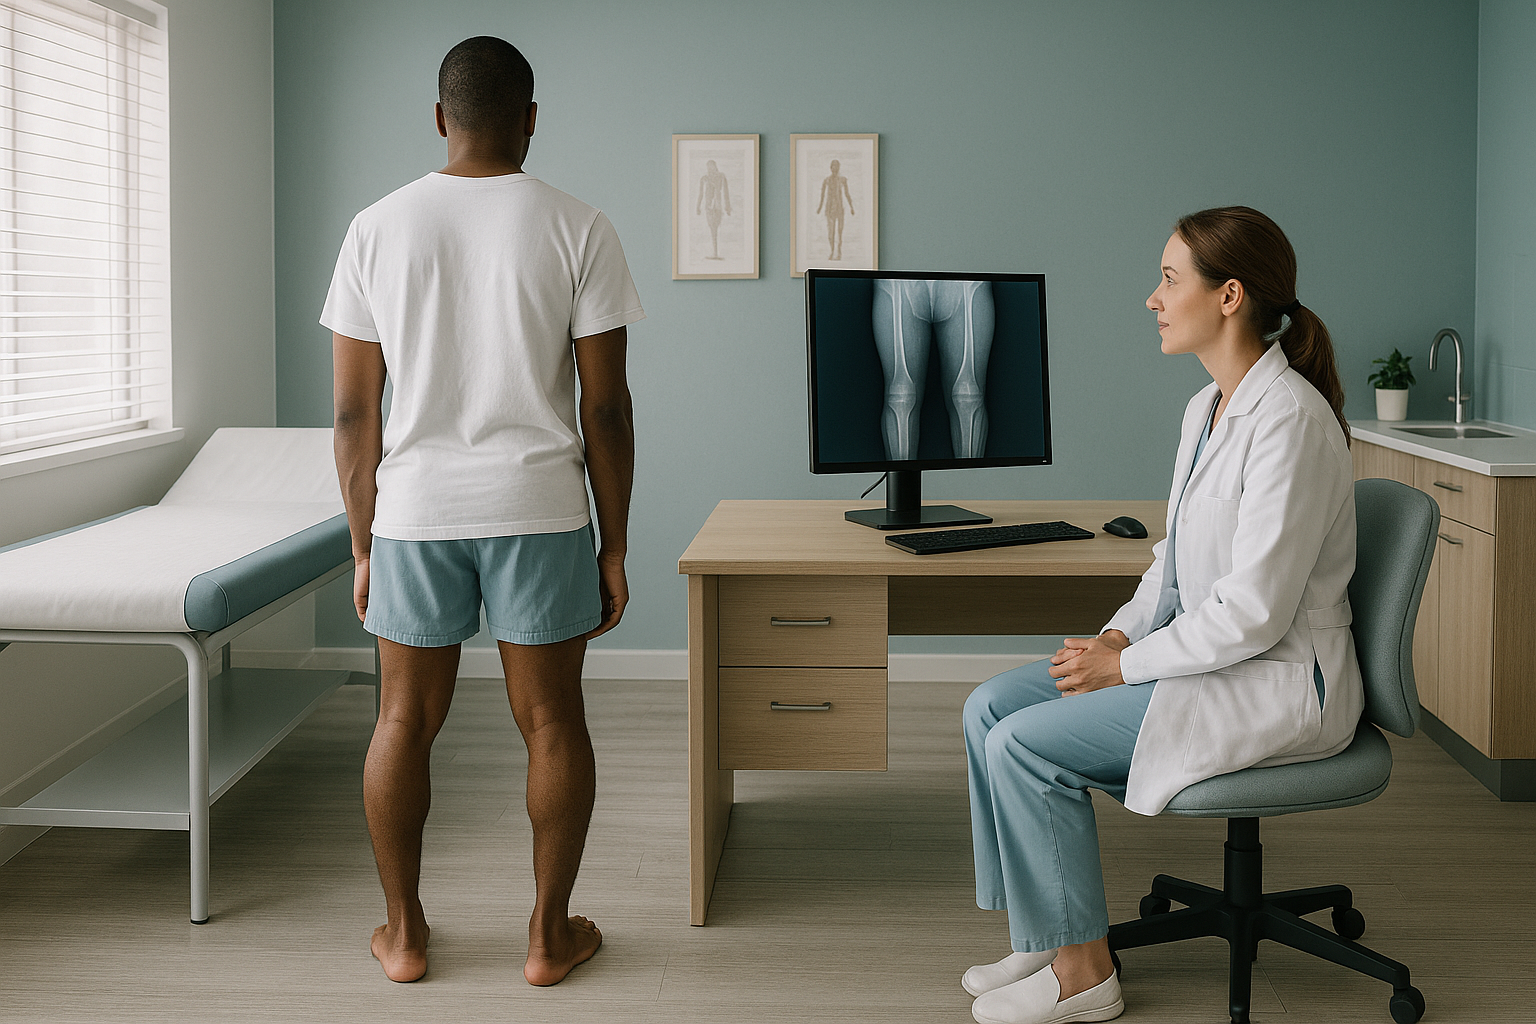
Crucially, this imaging should be done while the person is standing. When you lie down for a scan, your body weight is removed from the equation and the true bowing angle is reduced. A full-leg standing x-ray captures the legs from hip to ankle in a single weight-bearing image, giving the most accurate picture of the deformity.
At ScanAlign, low dose standing imaging, we use EOS technology, which produces standing full-leg images with about 90% less radiation than a standard x-ray, around ten times less. For growing children and adolescents who may need repeat imaging over time, that lower dose matters.
When is MRI the better choice? EOS shows bones, joints and overall alignment clearly. If your consultant needs to look at soft tissues, cartilage, or the growth plate in fine detail, MRI is usually the better tool. In many cases of Blount's disease, both types of imaging are used together.
When do bow legs from Blount's disease need surgery?
Not every case requires an operation. The decision depends on the child's age, how severe the bowing is, and whether it is getting worse. Here is a general guide to the pathway.
Observation and monitoring
For very young children with mild bowing, the first step is often regular monitoring with clinical review and standing imaging to see whether the bowing resolves on its own.
Bracing
In infantile Blount's disease (before age four), a knee-ankle-foot brace worn at night may help guide growth. Bracing is less effective if the child is older or if the deformity is severe.
Guided growth surgery
A small plate or staple is placed on the outer growth plate to slow it down temporarily, allowing the inner side to catch up and straighten the leg. This works best while there is still significant growth remaining.
Osteotomy
For severe or late-presenting cases, the surgeon cuts the tibia and realigns it into a straighter position. This is a bigger procedure but can correct significant deformity.
ScanAlign is a diagnostic imaging clinic. We do not provide treatment, but our standing full-leg images give your orthopaedic surgeon or consultant the detailed alignment data they need to plan the right approach.
Concerned about progressive bowing? A standing full-leg image gives your specialist the clearest picture of the deformity.
Book a paediatric leg alignment scanFrequently asked questions about Blount's disease
Most children's bow legs straighten naturally by age three to four. If bowing is still present or worsening after this age, it is worth having the legs assessed by a specialist.
Normal bowing is symmetrical and gradually improves. Blount's disease typically causes a sharper, more angular bow just below the knee. It may affect one leg more than the other and worsens rather than improves over time.
No. Rickets is caused by a vitamin D or calcium deficiency that softens all the bones. Blount's disease is a localised growth plate problem at the top of the tibia. They look different on imaging, though both can cause bowing.
The infantile form often affects both legs. The adolescent form more commonly affects just one. Even when both legs are involved, the severity can differ between them.
Blount's disease is diagnosed during growth. However, adults who had untreated or partially treated Blount's disease as children may still have residual bowing and related joint problems that benefit from alignment assessment.
When you lie down, gravity no longer acts on the bones. A standing image shows the real angle of bowing under your full body weight, giving the surgeon the most accurate measurement to plan treatment.
EOS uses about 90% less radiation than a standard x-ray, around ten times less. This is particularly helpful when a young person needs repeat imaging to monitor the deformity over time.
No. You can self-refer. We offer a free video consultation first so we can understand the concern and confirm that a standing full-leg image is the right next step.
Details about scan costs are on our FAQs page. The initial video consultation is free of charge.
Recurrence is possible, particularly in the infantile form or if the child still has significant growth remaining. Regular monitoring with standing imaging helps detect any return of bowing early.
Worried about progressive leg bowing?
A free video consultation lets us understand the concern and advise whether a standing full-leg image is the right next step.
Book a free video consultationSources
- Sabharwal S. Blount disease. Journal of Bone and Joint Surgery (American). 2009;91(7):1758-1776.
- NHS. Bow legs. NHS Health A to Z. Available at: nhs.uk.
- Langenskiöld A. Tibia vara (osteochondrosis deformans tibiae): a survey of 23 cases. Acta Chirurgica Scandinavica. 1952;103(1):1-22.
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.