
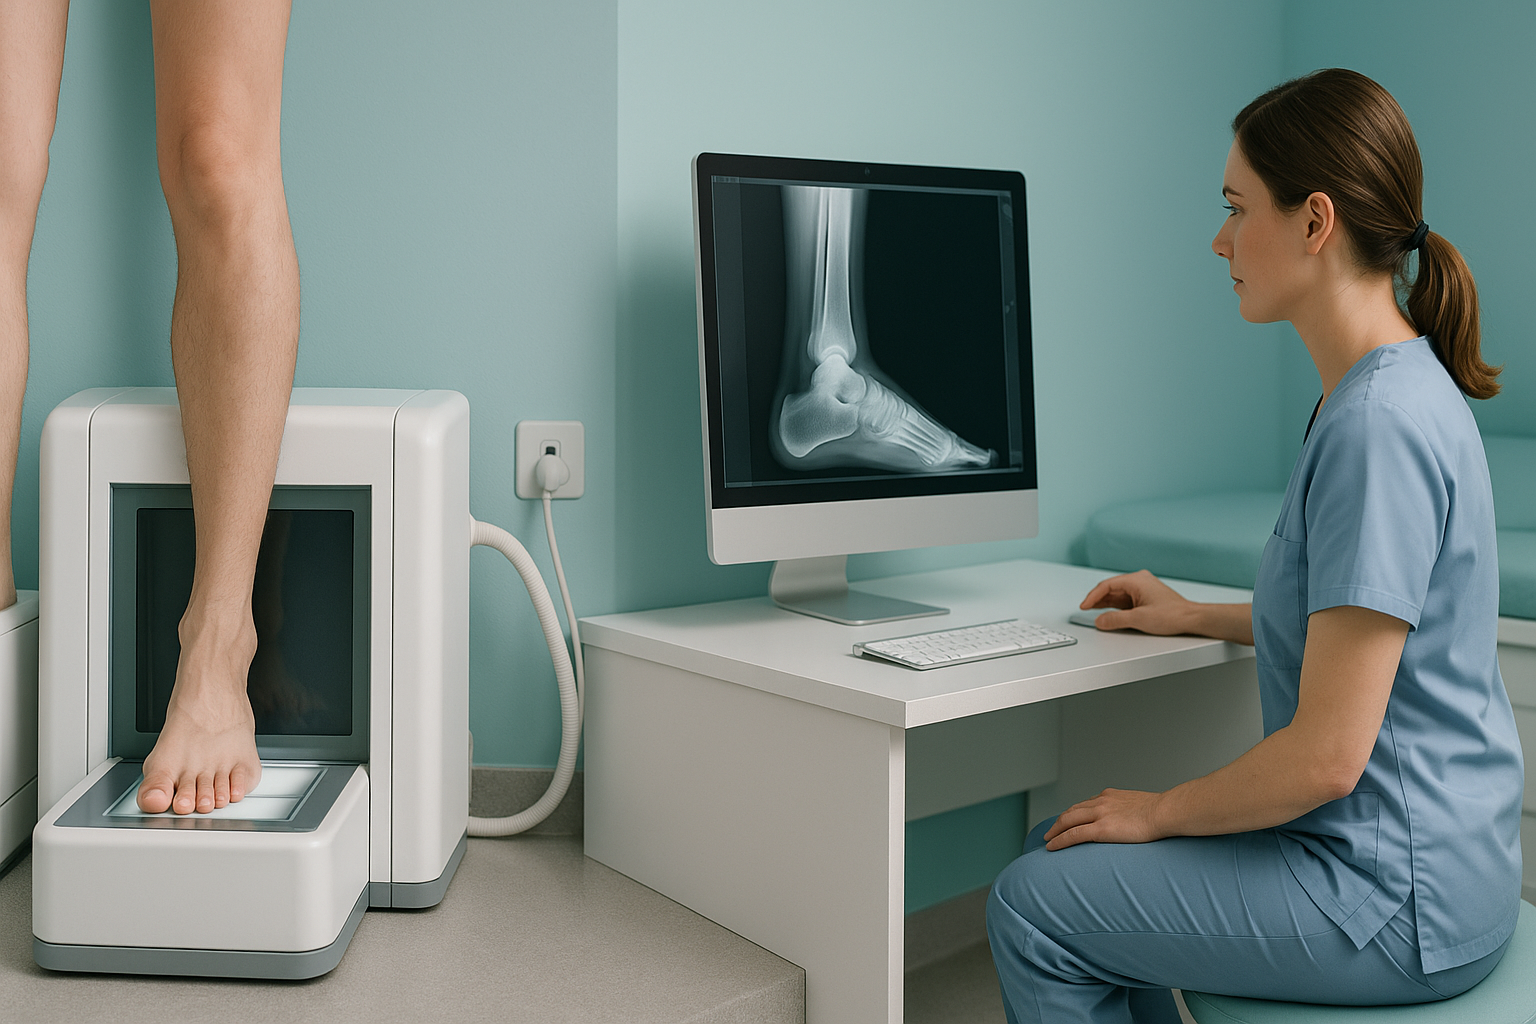
What Is the Evidence Base for Weight-Bearing Imaging?
A growing body of peer-reviewed research shows that imaging the body while standing reveals alignment changes, joint-space differences, and spinal curvatures that are hidden when a patient lies down. Studies consistently find clinically significant differences between supine and standing measurements, making weight-bearing imaging more representative of how your skeleton actually functions.
Key takeaways
- Standing radiographs often show larger spinal curves and narrower joint spaces than lying-down images of the same patient [1, 2].
- Biplanar EOS imaging delivers about 90% less radiation than a standard X-ray, around ten times less, while producing full-length, weight-bearing images [3].
- Research supports higher measurement reliability (lower intra-observer variation) with calibrated standing systems compared with conventional films.
- Weight-bearing imaging has recognised limitations. It shows bones and alignment, not soft tissue, and most studies use moderate sample sizes.
- For soft-tissue, disc, or nerve problems, MRI remains the better tool.
If you have an ongoing back, hip, or knee problem, you may have already had scans that came back "normal." One reason for that: many conventional scans are taken lying down. The evidence summarised on this page explains why that matters, what the research actually shows, and where the current limits of the evidence sit. For a plain-language comparison, see the guide to weight-bearing versus lying imaging.
Why does position matter when you take an X-ray?
Position matters because gravity changes the shape and loading of your skeleton. When you lie flat on a table, your muscles relax, your spine straightens slightly, and your joints decompress. This means an image taken supine (lying down) may not reflect what is happening when you stand, walk, or sit, the positions where you actually feel pain.
Multiple studies have documented measurable differences between supine and standing radiographs in both the spine and the lower limbs [1, 2]. These are not subtle academic points. A curve that looks mild when lying down may cross a clinically relevant threshold when the patient stands. A knee joint that appears well-spaced supine may show significant narrowing under load.

What does the research say about standing spinal imaging?
Research consistently shows that spinal curvatures are larger when measured standing than when measured lying down. A systematic review published in European Spine Journal found that sagittal parameters, the natural front-to-back curves of the spine, change significantly between supine MRI and standing radiographs [1]. This has direct clinical relevance because decisions about surgery and bracing are based on these measurements.
Understanding sagittal balance, the way the spine's curves work together to keep your head centred over your pelvis, is a good example. Sagittal balance can only be assessed properly when the patient is upright and weight-bearing. An MRI or CT taken lying down simply cannot capture it.
Biplanar EOS systems address this by producing a calibrated, full-length standing image of the spine from head to pelvis in a single exposure. Published studies report high intra-observer and inter-observer reliability for spinal measurements made from EOS images, meaning different radiologists measuring the same image tend to arrive at very similar numbers [3].
What it captures well: Detailed cross-sectional anatomy of discs, nerves, and soft tissue (MRI). Bone detail in fine slices (CT).
What it may miss: True spinal curvature under gravity. Sagittal balance. Compensatory patterns between regions. The way adjacent joints load under body weight.
What it captures well: Real-world alignment under gravity. Full-length skeletal geometry from head to feet. Joint spacing as it occurs when you stand and walk.
What it may miss: Soft-tissue detail (discs, ligaments, muscles). Internal organ structures. Subtle bone-marrow changes.
Is there evidence for weight-bearing imaging of the knee and hip?
Yes. Research in lower-limb orthopaedics has long recognised that weight-bearing radiographs show joint-space narrowing more accurately than supine images. A study in Knee Surgery, Sports Traumatology, Arthroscopy found that standing knee radiographs revealed greater and more clinically representative joint-space loss compared with supine films of the same patients [2]. This influences how arthritis is graded and whether surgery is recommended.
For lower limb alignment, a full-length standing image captures the mechanical axis of the entire leg, from hip to ankle. Surgeons planning knee or hip replacements increasingly use this information to guide implant positioning. Conventional short-film X-rays cannot show the whole mechanical axis in one exposure, which limits their usefulness for pre-operative planning.
| Research area | Standing finding | Clinical relevance |
|---|---|---|
| Knee joint space | Narrower under load vs. supine | More accurate arthritis grading |
| Mechanical axis (full leg) | Visible only on full-length standing film | Better surgical planning |
| Spinal sagittal parameters | Curves larger standing than supine | Truer assessment of deformity |
| Pelvic tilt | Changes between lying and standing | Affects hip and spine interaction |
How accurate is EOS imaging and what is the radiation dose?
EOS imaging uses about 90% less radiation than a standard X-ray, around ten times less. This low dose is well documented in the manufacturer's published data and in independent dosimetry studies [3]. It matters because full-length imaging from head to foot would involve a significant dose on a conventional system, especially if multiple views are needed.
Accuracy studies have examined both 2D measurements (distances and angles on the flat image) and 3D reconstructions generated by the EOS software. Published research reports high measurement reliability, with low intra-observer variation, meaning the same clinician measuring the same image on different occasions gets consistent results [3]. Inter-observer reliability (agreement between different clinicians) is also reported as strong, though the specific figures vary by study and by which parameter is being measured.
It is worth noting that most of these studies use moderate sample sizes, typically dozens to low hundreds of patients. Large-scale randomised controlled trials comparing clinical outcomes (not just measurement accuracy) between standing and supine imaging are still relatively few. The evidence supports standing imaging as more representative, but the field would benefit from larger outcome studies.
What are the limitations of the current evidence?
Honest appraisal of the evidence is important. Here are the main limitations to be aware of.
Many studies involve moderate cohorts. Larger, multi-centre trials would strengthen the evidence further.
Most studies demonstrate that standing measurements are different and more reliable. Fewer studies show that this leads to better clinical outcomes, such as improved surgical results.
Weight-bearing X-ray systems, including EOS, show bones and joints. They do not image discs, nerves, ligaments, or muscles. MRI is needed for these.
A patient who cannot stand unaided, or who has significant pain standing still, may not produce an optimal weight-bearing image.
None of these limitations invalidates the core finding. They simply mean the evidence is still maturing, and clinicians should interpret results alongside the full clinical picture.
A note on MRI. EOS and other standing X-ray systems show bones, joints, and alignment beautifully. For soft-tissue problems, such as disc herniations, nerve compression, ligament tears, or muscle injuries, MRI is usually the better tool. The two types of imaging answer different questions, and the best assessment often uses both. If you want to understand whether weight-bearing or traditional imaging is the right starting point for you, a short consultation can help.
If you are a clinician wanting to refer a patient, or if you would like to understand whether standing imaging is appropriate for your situation, you can discuss a referral with our team at no cost.
Book a free video consultationFrequently asked questions
Yes. Multiple peer-reviewed studies and systematic reviews confirm that standing images reveal alignment differences and joint-space changes that supine imaging misses [1, 2, 3]. The evidence base is growing, though larger outcome trials are still needed.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. This is documented in published dosimetry studies and makes full-length imaging practical with a very low dose.
Yes. Research consistently shows measurable differences. Spinal curves tend to be larger standing, and knee joint spaces tend to be narrower under load. These differences can change clinical decisions.
No. EOS shows bones, joints, and skeletal alignment. MRI shows soft tissue such as discs, nerves, and ligaments. They answer different questions. Many patients benefit from both.
Published studies report high intra-observer and inter-observer reliability for EOS measurements, meaning different clinicians measuring the same image reach similar results. Reliability varies slightly depending on which parameter is being measured.
EOS is uncommon in the UK but is available at a small number of private clinics. ScanAlign, standing EOS imaging, is based at 19 Harley Street, London, and offers self-referred appointments.
No. You can self-refer. The process starts with a free video consultation where a specialist radiographer reviews your history and confirms whether a standing scan is appropriate.
Most studies have moderate sample sizes and focus on measurement differences rather than long-term clinical outcomes. Patients who cannot stand unaided may not be suitable. Soft-tissue problems require MRI.
One common reason is that conventional scans taken lying down can mask alignment problems that only appear under gravity. A standing image shows your skeleton as it actually functions, which may reveal a cause your previous scan did not capture.
Pricing details are available on the ScanAlign website. The initial video consultation is free and carries no obligation.
See what standing imaging could show
Start with a free, no-obligation video consultation. A specialist radiographer will review your history and advise whether a standing scan is appropriate.
Book a free video consultationSources
- Le Huec, J.C., et al. "Sagittal balance of the spine." European Spine Journal, 2019. A systematic review examining differences in sagittal parameters between supine and standing imaging.
- Brouwer, R.W., et al. "Association between valgus and varus alignment and the development and progression of radiographic osteoarthritis of the knee." Arthritis & Rheumatism, 2007. Demonstrates the clinical significance of weight-bearing lower-limb alignment assessment.
- Illés, T. and Somoskeöy, S. "The EOS imaging system and its uses in daily orthopaedic practice." International Orthopaedics, 2012. A review of EOS dosimetry, measurement reliability, and clinical applications.
Written by Abbas Dhami (Specialist Diagnostic Radiographer).
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.