
Knee Anatomy: What Every Ligament and Bone Actually Does
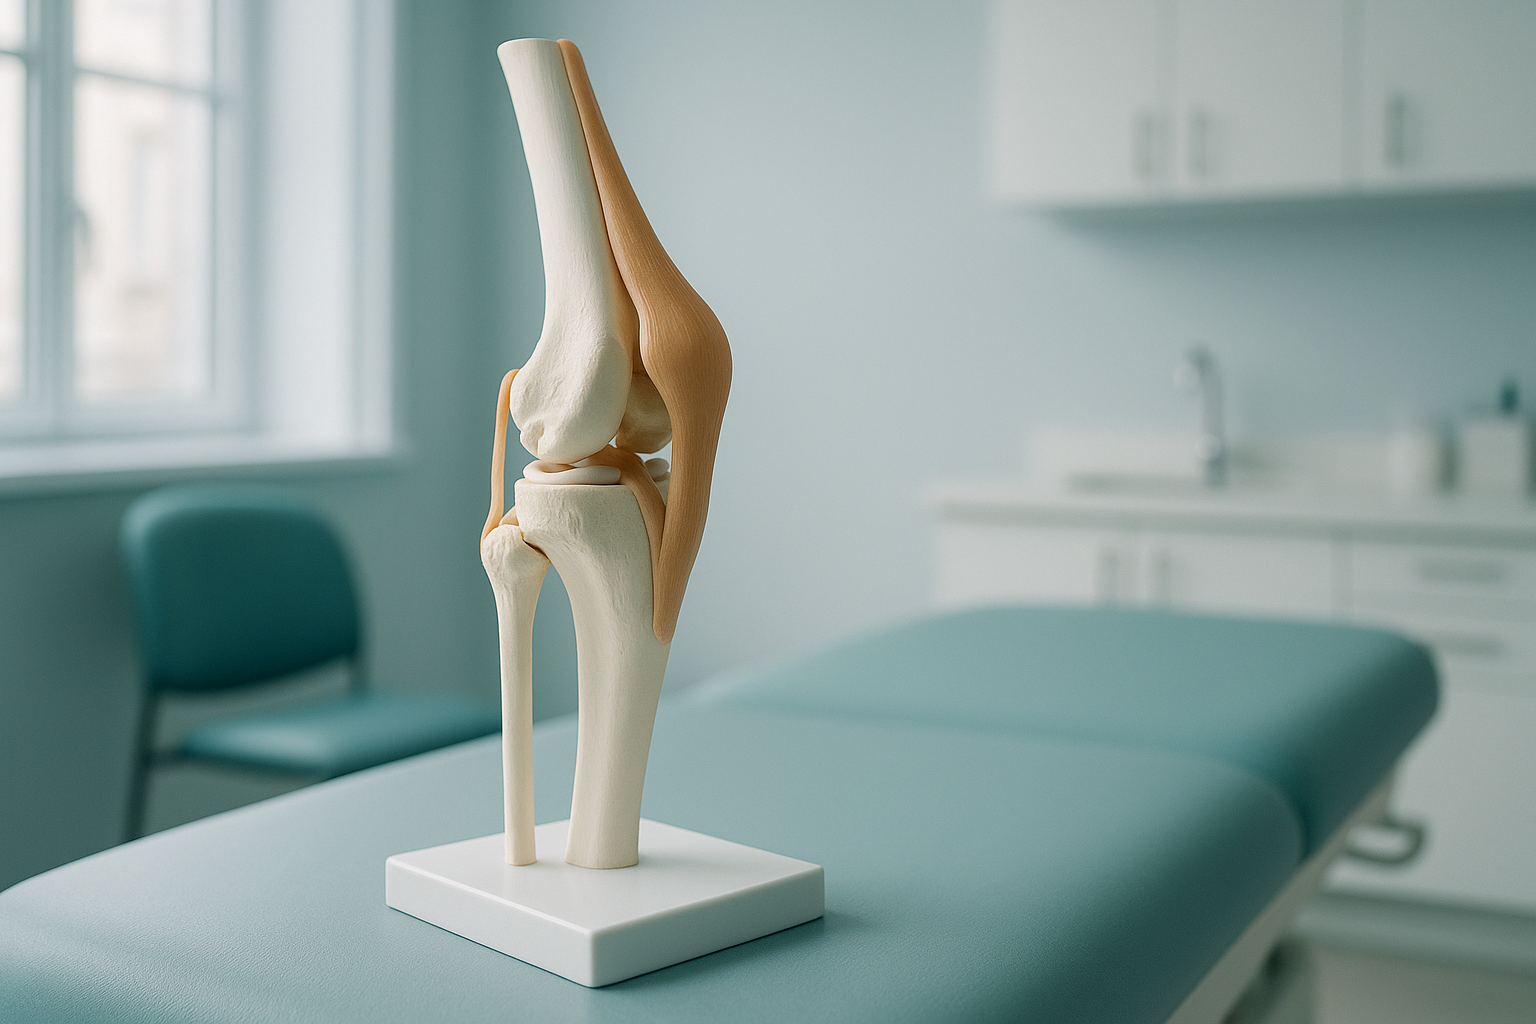
Your knee joint is where the thighbone (femur), shinbone (tibia) and kneecap (patella) meet. Four main ligaments hold them together, two types of cartilage cushion and protect the surfaces, and several tendons connect your muscles to the bones so you can bend, straighten and bear weight.
Key takeaways
- The knee relies on three bones, four main ligaments, two types of cartilage and several tendons working together.
- Pain often appears away from its true cause because the whole leg shares the load.
- Lying-down scans can miss alignment problems that only appear when you stand and bear weight.
- EOS standing imaging captures the full leg in one low-dose image so your clinician can see how every part lines up under real conditions.
Understanding your knee anatomy helps you make sense of a diagnosis, ask sharper questions and choose the right next step. Below is a plain-English guide to every major part of the knee, what it does, and why alignment matters more than most people realise.
What bones make up the knee joint?
Three bones form the knee joint: the femur (thighbone), the tibia (shinbone) and the patella (kneecap). A fourth bone, the fibula, sits alongside the tibia on the outer side and provides an anchor point for one of the ligaments, but it does not bear your body weight directly.
The longest, strongest bone in your body. Its rounded lower end rests on the tibia and glides when you bend or straighten the knee.
The main weight-bearing bone of the lower leg. Its flat upper plateau is where the femur sits, cushioned by cartilage.
A small, shield-shaped bone that sits inside the quadriceps tendon. It protects the front of the joint and acts as a lever, giving your thigh muscles more power when you straighten the knee.
Even a small shift in how these bones line up can change where force travels through the joint. That is why alignment assessment matters, especially when problems have been difficult to explain.
What do the four main knee ligaments do?
Ligaments are tough bands of tissue that connect bone to bone. The knee has four main ligaments, and each one prevents a specific type of unwanted movement.
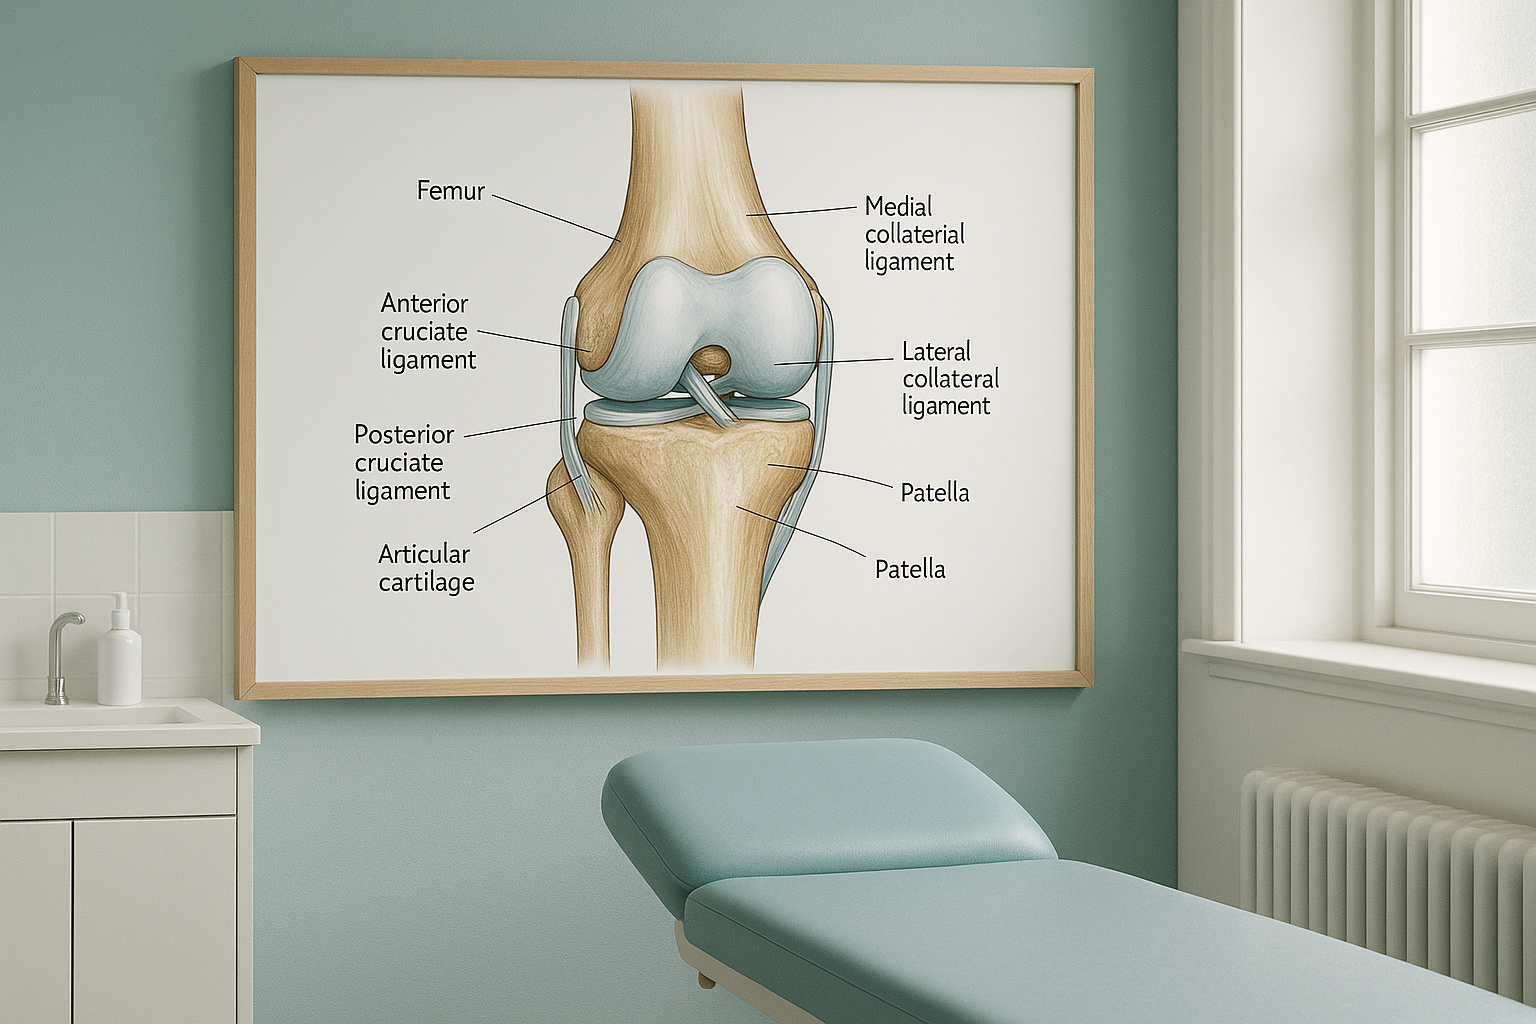
Anterior cruciate ligament. Stops the shinbone from sliding forwards under the thighbone and helps control rotation.
Posterior cruciate ligament. Prevents the shinbone from sliding backwards. A PCL strain is less common than an ACL tear but can cause deep instability.
Medial collateral ligament. Resists forces pushing the knee inward. An MCL injury is one of the most common knee ligament problems.
Lateral collateral ligament. Resists forces pushing the knee outward. It runs on the outer side, linking the femur to the fibula.
When one ligament is weakened or torn, the others work harder to compensate. Over time, this extra load can cause cartilage wear and pain that seems unrelated to the original injury.
What does the cartilage in your knee do?
There are two types of cartilage inside the knee, each with a different job.
Articular cartilage is the smooth, slippery coating on the ends of the femur, the top of the tibia and the underside of the patella. It lets the bones glide over each other with almost no friction. When this layer wears thin or softens, you might hear the term chondromalacia patella, which refers to damage on the underside of the kneecap.
Each knee has two menisci, the medial (inner) and lateral (outer). These are crescent-shaped pads of tough, rubbery cartilage that sit between the femur and tibia. They act as shock absorbers, spread load evenly across the joint, and help keep the femur stable on the tibia. A torn meniscus is one of the most common knee injuries.
Cartilage does not show up on a standard X-ray. However, when standing imaging reveals uneven joint spacing, it gives a strong clue that cartilage on one side is thinner than the other.
What are the main tendons around the knee?
Tendons connect muscles to bones. Two tendons are especially important for knee function.
- Quadriceps tendon. Connects the four muscles at the front of your thigh to the top of the patella. It is the primary driver when you straighten your knee.
- Patellar tendon. Runs from the bottom of the patella to the front of the tibia. When the quadriceps contracts, force passes through this tendon to extend the lower leg. Overuse or poor tracking of the kneecap can lead to patellar tendonitis.
Other tendons, including the hamstring tendons at the back and the iliotibial band on the outer side, also play important roles in stabilising the knee during movement.
What is the joint capsule and synovium?
The joint capsule is a tough, fibrous sleeve that wraps around the entire knee. Inside that sleeve is a thin lining called the synovium (or synovial membrane). The synovium produces a small amount of synovial fluid, which lubricates and nourishes the cartilage. If the synovium becomes inflamed, extra fluid is produced, and the knee swells. This is what people call "water on the knee."
When is MRI the better choice? EOS standing imaging shows bones, joint spacing and overall alignment brilliantly. For soft-tissue detail, such as a suspected meniscus tear, ligament damage, or inflamed synovium, MRI is usually the better tool. Your clinician may recommend one or both, depending on the question they need to answer.
Why does whole-leg alignment matter for your knee?
Your knee does not work in isolation. It sits between the hip and the ankle, and the alignment of the entire leg decides how force travels through the joint. If the hip tilts or the foot rolls inward, the knee is forced to compensate. Over time, uneven loading wears one side of the cartilage faster and overloads certain ligaments or tendons.
An EOS standing scan captures your full leg, from hip to ankle, in a single weight-bearing image. Because you are upright and your muscles are working, the image shows how the bones and joints actually line up under real conditions. This often reveals misalignment that a lying-down scan would miss.
Conventional X-rays, CT and MRI are usually taken while you lie down. In that position, gravity is removed and your muscles relax. The joint can look well aligned on the image, even when it shifts significantly under your body weight. That is why some knee problems are hard to explain with lying-down scans alone.
EOS imaging also uses about 90% less radiation than a standard X-ray, around ten times less. That makes it suitable when your clinician needs repeated follow-up images over time.
Want to see how your knee aligns under your own body weight? ScanAlign offers EOS standing imaging at 19 Harley Street, London.
Book a free video consultationFrequently asked questions about knee anatomy
Three bones form the knee joint itself: the femur (thighbone), tibia (shinbone) and patella (kneecap). The fibula sits alongside the tibia and anchors one ligament, but it is not a direct part of the joint surface.
A ligament connects bone to bone and stabilises the joint. A tendon connects muscle to bone and transmits the force that moves your leg. Both are made of tough connective tissue, but they have different jobs.
Each meniscus is a rubbery, crescent-shaped pad that sits between the femur and tibia. The two menisci absorb shock, spread load across the joint and help keep the femur stable on the flat tibial surface.
Yes. Your body is a connected chain. If the hip tilts or the ankle rolls, the knee compensates to keep you upright. Over time, that extra stress can cause pain, cartilage wear or tendon overload at the knee, even though the root cause is elsewhere.
When you lie down, gravity is removed and your muscles relax. The joint can look well aligned on the image even though it shifts under your body weight. A standing scan shows the real picture, which is why alignment problems are sometimes only visible in a weight-bearing image.
Articular cartilage is the smooth, glassy coating on the ends of the femur, the top of the tibia and the underside of the patella. It allows the bones to glide with almost no friction. When this layer wears thin, you may hear terms like osteoarthritis or chondromalacia.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. This makes it a good option when multiple views or follow-up images are needed.
No. ScanAlign is a private, self-pay clinic. You can book a standing knee assessment yourself without a GP referral. Your images and report can then be shared with any clinician you choose.
EOS is designed for bones and alignment. For soft-tissue detail, such as a meniscus tear, ligament damage or nerve problems, MRI is usually the better tool. Your clinician may recommend one or both depending on what they need to see.
Pricing details are on the ScanAlign FAQs and cost page. A free video consultation is available first so you can check whether the scan is right for you before committing.
See how your knee really lines up
A free video consultation helps you understand whether a standing scan is the right next step for your knee.
Book a free video consultationWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- NHS. "Knee pain." nhs.uk. Accessed 2024.
- American Academy of Orthopaedic Surgeons (AAOS). "Knee Ligament Injuries." orthoinfo.aaos.org. Accessed 2024.
- Drake RL, Vogl AW, Mitchell AWM. Gray's Anatomy for Students. 4th ed. Elsevier; 2019.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.