
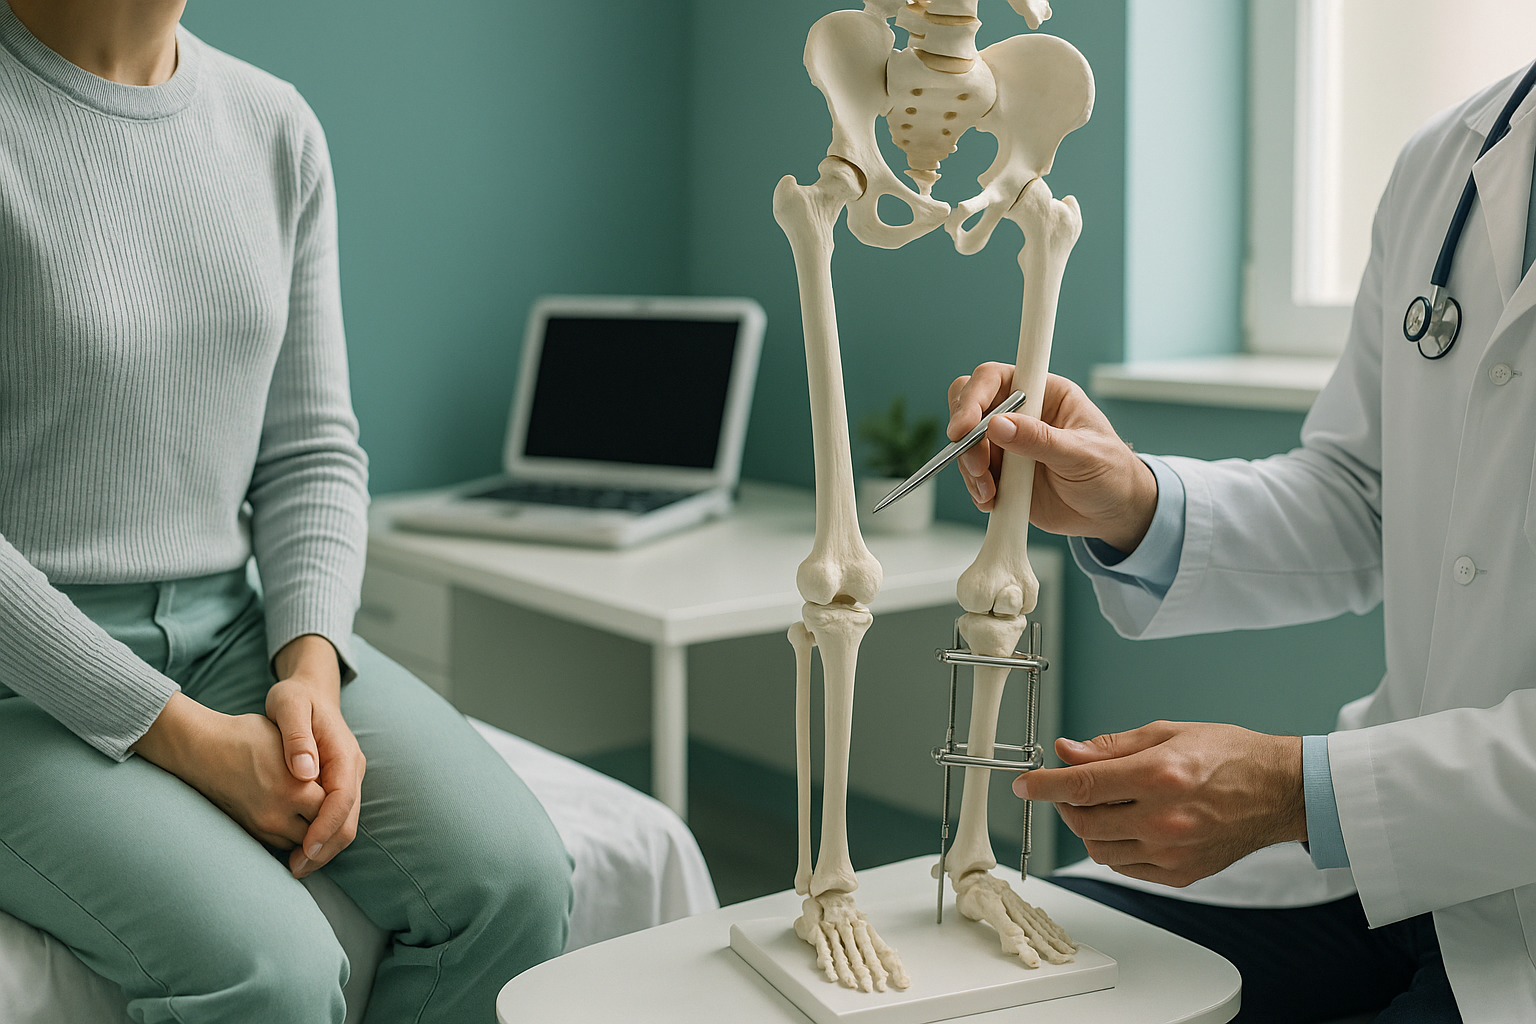
What Does Limb Lengthening Surgery Involve?
Limb lengthening surgery uses a controlled process called distraction osteogenesis. A surgeon cuts the bone, then gradually pulls the two ends apart so new bone grows in the gap. The procedure can correct a leg length discrepancy, straighten a deformity, or increase height for cosmetic reasons. Recovery takes many months and carries real risks.
Key takeaways
- Limb lengthening relies on distraction osteogenesis, where the body grows new bone between separated bone ends.
- An external fixator (such as an Ilizarov frame) or an internal lengthening nail is used to control the separation.
- Recovery commonly takes six to twelve months or longer, with intensive physiotherapy.
- Cosmetic leg lengthening carries the same surgical risks as reconstructive lengthening, and these risks should be weighed carefully.
- Accurate full-limb imaging before surgery helps the surgeon plan the cut and predict lower limb alignment after lengthening.
If you have one leg noticeably shorter than the other, a limb deformity, or you are considering cosmetic height increase, you have probably come across the term limb lengthening surgery. This page explains what the procedure actually involves, what recovery looks like, and the risks you should understand before deciding.
How does limb lengthening surgery work?
Limb lengthening surgery works by carefully cutting through a bone (an osteotomy), then slowly separating the two ends so the body fills the gap with new bone. This biological process is called distraction osteogenesis. It was pioneered in the 1950s by Professor Gavriil Ilizarov and remains the foundation of all modern lengthening techniques.
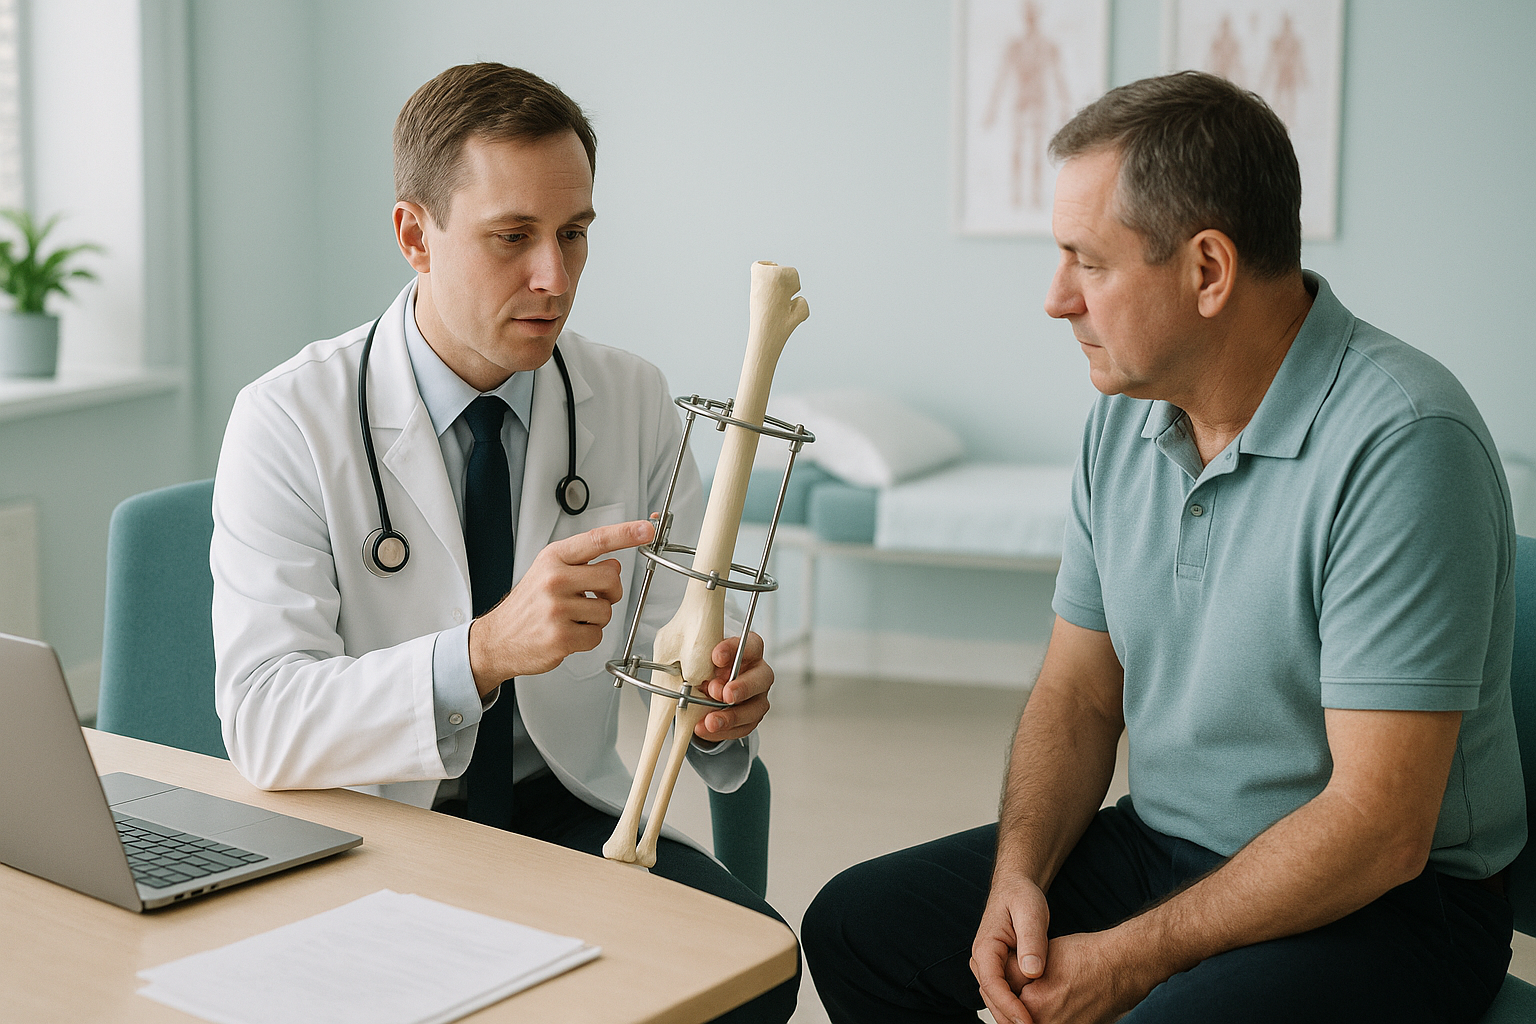
The procedure has three phases:
- Osteotomy. The surgeon makes a controlled cut through the bone, usually the tibia (shin) or femur (thigh).
- Distraction. After a few days of rest, a device gradually separates the bone ends, typically by about one millimetre per day. New bone, blood vessels and soft tissue form in the widening gap.
- Consolidation. Once the desired length is reached, the new bone needs time to harden and mature. This phase is often the longest part of recovery.
External fixator vs internal nail
Two main devices control the separation. An external fixator, such as the Ilizarov frame, is a metal ring-and-wire structure attached outside the leg. It is highly adjustable and allows the surgeon to correct angular deformities at the same time as lengthening. An intramedullary lengthening nail sits inside the bone and is adjusted with a magnet or motorised mechanism. The nail is less visible and generally more comfortable, but it cannot correct all types of deformity and is more expensive.
What are the risks of limb lengthening surgery?
Limb lengthening surgery carries meaningful risks, and you should understand them fully before consenting. These apply whether the procedure is for reconstructive or cosmetic reasons.
Pin-site infections are common with external fixators. Deep bone infection (osteomyelitis) is rarer but serious.
Stretching nerves and blood vessels too quickly can cause numbness, weakness or circulatory problems.
Muscles and tendons tighten as the bone lengthens. Without constant physiotherapy, joints can become permanently stiff.
The new bone may form too slowly (delayed union) or not at all (non-union), sometimes needing further surgery.
Other possible complications include misalignment during lengthening, premature bone fusion that stops the process early, and psychological difficulty coping with a long, painful recovery. If you experience sudden numbness, weakness, or loss of sensation during recovery, seek urgent medical attention through your surgical team, your GP, 111 or A&E.
How long is limb lengthening recovery?
Limb lengthening recovery typically takes six to twelve months as a minimum, and full return to sport or heavy activity can take longer. Recovery is not just about bone healing. It includes intensive daily physiotherapy, pain management and gradual return to weight-bearing.
Surgery and latency (days 1 to 7)
The bone is cut and the fixator or nail is fitted. A short rest period allows the first healing response before distraction begins.
Distraction phase (weeks to months)
The bone is separated gradually. Daily physiotherapy is essential to keep joints moving and prevent contractures. Regular X-rays monitor progress.
Consolidation phase (months)
New bone hardens and matures. External fixators remain in place until the bone is strong enough, which is often the most frustrating part of the process.
Rehabilitation
Ongoing physiotherapy rebuilds strength and flexibility. Full recovery is a commitment measured in months, not weeks.
The consolidation phase alone is often roughly twice as long as the distraction phase. Smoking, poor nutrition and certain medical conditions can slow bone healing further.
Is cosmetic leg lengthening safe?
Cosmetic leg lengthening uses the same surgical techniques as reconstructive lengthening, so it carries the same risks. The difference is context. In reconstructive surgery, the benefit is correcting a functional problem, a significant leg length discrepancy or a deformity that affects walking. In cosmetic surgery, the benefit is increased height in someone whose legs are structurally normal.
That distinction matters because complications like infection, nerve damage and joint stiffness carry more weight when the starting point is a healthy, functioning leg. No surgical procedure is risk-free, and the recovery is genuinely hard, often involving months of limited mobility, daily pain and reliance on crutches or a frame.
If you are considering cosmetic limb lengthening, it is worth asking yourself honest questions about your expectations, your ability to take months away from work and activity, and whether you have discussed the decision with someone you trust. A thorough consultation with an experienced limb reconstruction surgeon, not just a cosmetic surgery clinic, is strongly recommended.
A note on soft-tissue imaging. EOS and standing X-rays show bones, joints and alignment clearly. For soft-tissue concerns such as muscles, nerves or blood vessels, MRI is usually the better tool. Your surgeon may request both types of imaging as part of pre-operative planning.
Why does pre-operative imaging matter for limb lengthening?
Accurate pre-operative imaging is essential because the surgeon needs to know exactly how much length to add and how the mechanical axis of the leg will change. Getting this wrong risks creating new alignment problems, such as a knock-knee or bow-leg, that may need further correction.
A full-leg standing x-ray captures both legs from hip to ankle on a single image while you are upright and weight-bearing. This gives the surgeon a true picture of your bone lengths, joint angles and overall lower limb alignment under real loading conditions.

Lying-down imaging can relax the muscles and flatten out alignment problems that only appear when you stand. This is why standing imaging provides better data for surgical planning. EOS technology uses about 90% less radiation than a standard X-ray, around ten times less, making it a practical choice when multiple images are needed before and after surgery.
If you are preparing for limb lengthening or want to understand your leg alignment, you can book full-limb measurement imaging at ScanAlign, standing EOS imaging in London. Your images and report can be shared directly with your surgical team.
Book a free video consultationFrequently asked questions about limb lengthening surgery
Distraction osteogenesis is the biological process used in limb lengthening. After a bone is surgically cut, the two ends are gradually pulled apart. The body responds by growing new bone, blood vessels and soft tissue to fill the gap. The rate of separation is usually about one millimetre per day.
An Ilizarov frame is an external fixator made of metal rings connected by rods and wires that pass through the bone. It allows very precise control of lengthening and angular correction. It stays attached to the leg throughout the distraction and consolidation phases.
The amount depends on the bone being lengthened and individual factors. Surgeons typically aim for a few centimetres per bone segment. Going beyond what the soft tissues can tolerate increases the risk of complications. Your surgeon will discuss realistic limits during planning.
Costs vary widely depending on the hospital, surgeon, device used and whether the procedure is reconstructive or cosmetic. ScanAlign provides pre-operative imaging, not surgery. We do not publish surgical costs, but your surgeon or hospital will provide a full breakdown.
No. ScanAlign is a self-referral clinic, so you can book directly without a GP or consultant referral. Many people book imaging to bring accurate measurements to their first surgical consultation.
Most people experience significant discomfort during the distraction phase, particularly as soft tissues are stretched. Pain is managed with medication and careful adjustment of the distraction rate. The consolidation phase is generally less painful but can be frustrating because of limited mobility.
Weight-bearing during recovery depends on the technique used and the surgeon's protocol. Many patients use crutches or a wheelchair for weeks or months. Physiotherapy is essential throughout to maintain joint movement and muscle strength.
EOS captures the full leg from hip to ankle in a single standing image with about 90% less radiation than a standard X-ray, around ten times less. Because you are upright and weight-bearing, the image shows your true alignment under load, which lying-down X-rays can miss.
Generally no. The NHS typically funds limb lengthening only for medical reasons, such as correcting a significant leg length discrepancy or deformity. Cosmetic lengthening is usually available only through private clinics.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. It is a very low-dose imaging system. The scan takes only a few seconds and you simply stand still inside the machine. There is no injection or contrast dye involved.
Planning limb lengthening? Start with accurate imaging.
A standing full-leg scan gives your surgeon precise bone lengths and alignment measurements. No referral needed.
Book a free video consultationWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- Paley, D. (2002). Principles of Deformity Correction. Springer. A widely referenced textbook on distraction osteogenesis and limb reconstruction planning.
- British Orthopaedic Association. Guidance on limb reconstruction surgery standards in the United Kingdom.
- Ilizarov, G.A. (1989). The tension-stress effect on the genesis and growth of tissues. Clinical Orthopaedics and Related Research, 238, 249-281.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.