
Osteotomy or Knee Replacement: Which Is Right for Your Knee?
Osteotomy reshapes the bone around your knee to shift load away from worn cartilage, preserving the joint. Knee replacement removes the damaged surfaces and caps them with an implant. The right choice depends on your age, activity level, how much of the joint is affected, and your overall leg alignment. Your surgeon decides based on accurate imaging and clinical assessment.
Key takeaways
- Osteotomy is a joint-preserving option that corrects alignment, buying time before a future replacement.
- Knee replacement removes damaged surfaces entirely and is better suited when wear is widespread.
- Age, activity demands and the number of compartments affected are the main deciding factors.
- Accurate standing alignment measurement helps the surgeon plan either procedure with precision.
- The decision is always made by your surgeon based on your individual examination and imaging.
What is a knee osteotomy and how does it differ from a replacement?
A knee osteotomy is a surgical procedure that cuts and repositions the bone above or below the knee joint. It changes the angle of the leg so that your body weight passes through the healthier side of the cartilage rather than the worn side. The joint itself stays intact.
A knee replacement takes a different approach. The surgeon removes the damaged bone and cartilage surfaces and replaces them with metal and plastic components. It can be a total or partial knee replacement, depending on how many compartments of the knee are affected.
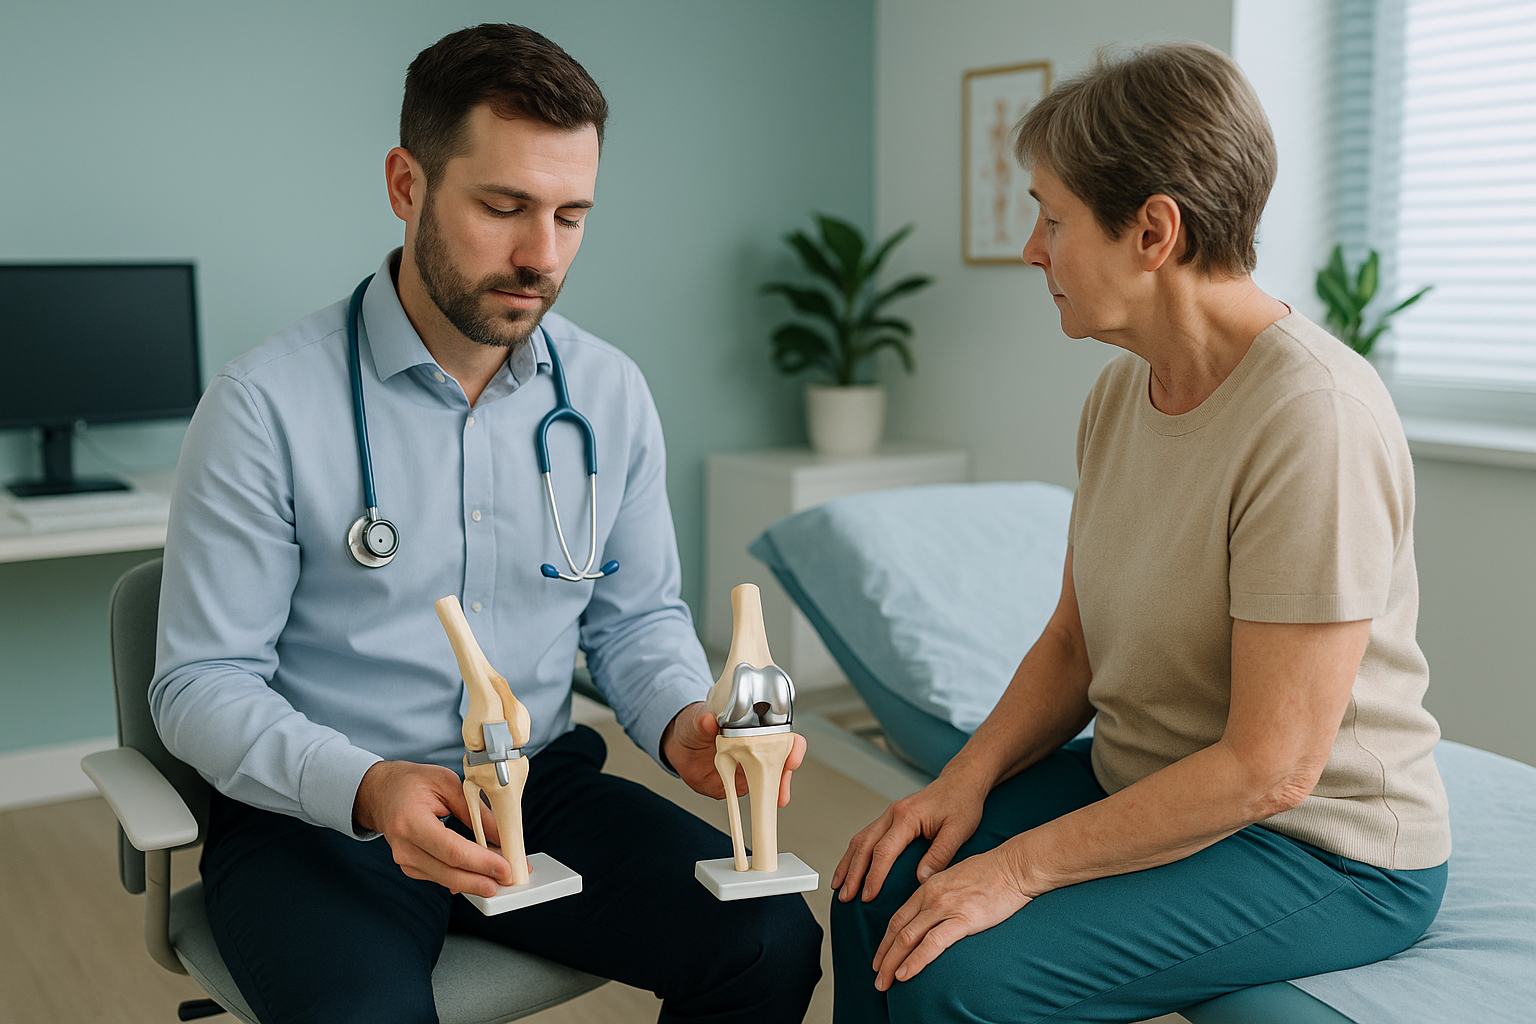
In short, osteotomy preserves your own joint by changing the mechanical environment around it. Replacement removes the worn parts and substitutes them with manufactured components.
How do osteotomy and knee replacement compare?
Both surgeries aim to reduce pain and improve function, but they suit different situations. Below is a side-by-side look at the key differences.
Knee osteotomy
- Goal: Redistribute load to healthy cartilage by correcting alignment.
- Best suited for: Wear limited to one compartment (usually the inner side), in an active person.
- Joint: Preserved. Your own cartilage and ligaments stay.
- Activity after: Many people return to higher-impact activities, including some sports.
- Lifespan: Often considered a bridge. It may delay the need for replacement by many years, though a replacement may still be needed eventually.
Knee replacement
- Goal: Replace worn surfaces with implant components for reliable pain relief.
- Best suited for: Widespread wear, or when alignment correction alone would not be enough.
- Joint: Replaced. Damaged bone and cartilage are removed.
- Activity after: Most people walk, cycle and swim comfortably. High-impact sport is generally discouraged.
- Lifespan: Modern implants last well, but they do wear over time. Revision surgery may be needed eventually, especially if the replacement is done at a younger age.
Am I too young for a knee replacement, or is osteotomy better?
Age is one factor, but it is not the only one. Surgeons weigh several things together before recommending osteotomy vs knee replacement.
Younger, more active people are often better candidates for osteotomy because it preserves the joint and delays the need for an implant with a limited lifespan.
Osteotomy works best when only one compartment (usually the medial, or inner, side) is worn. If two or three compartments are damaged, replacement is usually the more reliable option.
A bow-legged or knock-kneed alignment can accelerate wear on one side. Correcting that angle through osteotomy may be more logical than replacing the joint surfaces if the cartilage is otherwise reasonable.
Osteotomy requires intact ligaments (particularly the anterior cruciate ligament) for a good outcome. If the ligaments are significantly damaged, replacement may be preferred.
There is no strict age limit for a knee replacement. However, the younger you are when you have one, the more likely it is that the implant will need to be revised during your lifetime. That is why joint-preserving surgery, such as osteotomy or knock knee surgery, is often considered first in younger or very active patients.
Why does leg alignment matter when choosing between osteotomy and replacement?
Leg alignment is central to both procedures. When your leg is not straight, weight passes unevenly through the knee. Over time, the overloaded side wears faster. That wear pattern is what the surgeon needs to see clearly before recommending one procedure over the other.
Your body is a connected chain from your feet to your head. A misalignment at the hip or ankle can shift load through the knee in ways that are not obvious from looking at the knee alone. Pain in one place may be driven by a mechanical problem elsewhere in the chain.
Standard lying-down X-rays, CT and MRI are taken with the muscles relaxed and gravity removed. That means they can miss or understate the malalignment that is actually present when you stand and walk. A standing, weight-bearing image shows how the leg loads in real life.
How does standing imaging help plan an osteotomy or knee replacement?
Standing whole-body imaging captures the alignment of your entire leg, from hip to ankle, while you are upright and weight-bearing. This gives the surgeon a true picture of how your body loads the knee in real life.
For an osteotomy, the surgeon needs to know exactly how many degrees to correct. Too little, and the symptoms return. Too much, and the other side of the knee starts to wear. For a replacement, alignment data helps the surgeon position the implant components so that the mechanical axis of the leg is restored properly.
EOS imaging, available at ScanAlign, standing EOS imaging in London, captures the full leg in a single standing exposure with about 90% less radiation than a standard X-ray, around ten times less. Because it images you head to toe while you stand, it shows the true alignment that lying-down scans often miss.
If you are considering osteotomy or replacement and want your surgeon to have precise standing alignment data, you can book pre-operative alignment imaging at ScanAlign.
Book a free video consultationWhen MRI is the better tool: EOS shows bones, joints and alignment clearly. For soft tissue detail, such as cartilage thickness, meniscus tears, ligament damage or nerve involvement, MRI is usually the better choice. Your surgeon may request both types of imaging to get the full picture.
Frequently asked questions
Osteotomy reshapes the bone around the knee to shift load away from the worn area, preserving your own joint. Knee replacement removes the damaged surfaces and replaces them with an artificial implant.
There is no strict lower age limit. However, the younger you are, the more likely the implant will need revision during your lifetime. That is why surgeons often consider joint-preserving options like osteotomy first in younger patients.
Yes. Osteotomy is often seen as a bridge procedure. If wear progresses over the years, conversion to a replacement is a recognised and well-documented pathway.
Results vary by individual, but research suggests many osteotomies provide good pain relief for a decade or more. The outcome depends on factors like the accuracy of the correction, the condition of the remaining cartilage, and your activity level.
It is a significant surgical procedure carried out under anaesthetic. Recovery typically takes several months, with a period of restricted weight-bearing while the bone heals. Your surgeon will explain the specific recovery plan.
Many people return to moderate or even higher-impact activities after recovery. This is one of the advantages of preserving your own joint. Your surgeon will advise on what is realistic for you.
A standing X-ray shows how your leg actually loads under gravity. Lying-down images remove the effect of body weight, which can hide or understate malalignment. Accurate alignment data is essential for planning both osteotomy corrections and implant positioning.
An EOS scan uses about 90% less radiation than a standard X-ray, around ten times less. This makes it especially suitable when full-leg or whole-body images are needed.
No. You can self-refer. The process starts with a free video consultation where a specialist radiographer reviews your situation and confirms whether the scan is appropriate for you.
Pricing details are available on the ScanAlign website. You can find current information on the FAQs page.
Considering osteotomy or replacement?
Standing alignment imaging gives your surgeon the precise measurements needed to plan either procedure. Start with a free video consultation to find out if an EOS scan is right for you.
Book a free video consultationSources
- Brouwer, R.W. et al. "Osteotomy for treating knee osteoarthritis." Cochrane Database of Systematic Reviews, 2014. Cochrane Library.
- National Institute for Health and Care Excellence (NICE). "Osteoarthritis: care and management." Clinical guideline CG177, updated 2022.
- Paley, D. "Principles of Deformity Correction." Springer, 2002. Widely cited reference on limb alignment and osteotomy planning.
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.