
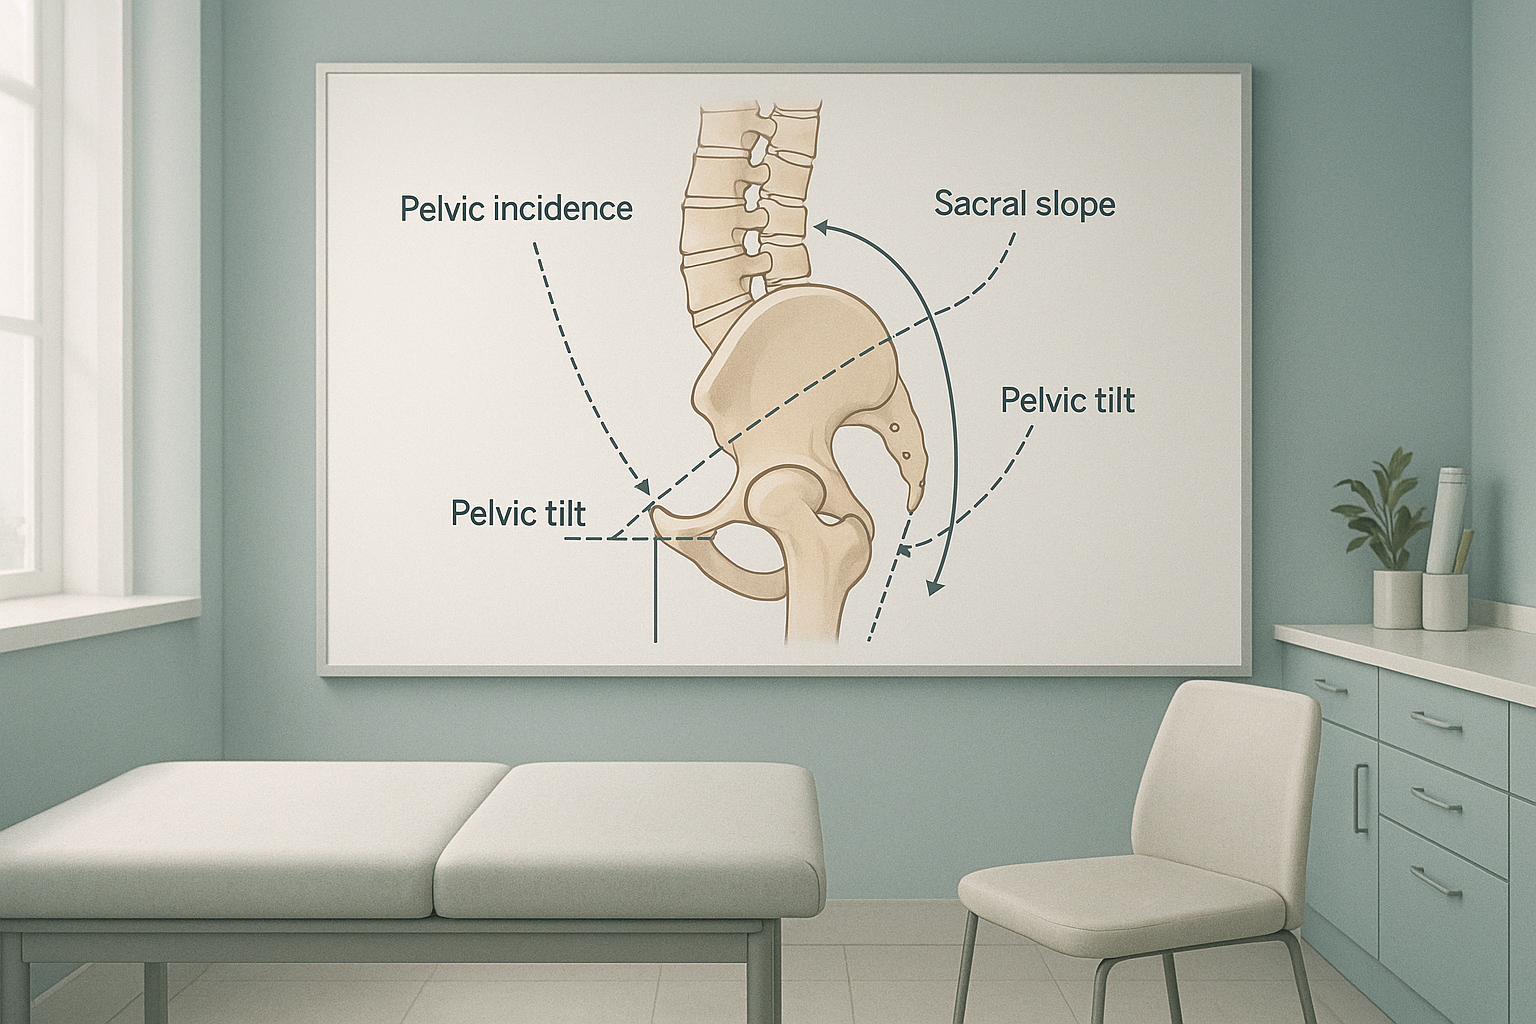
What Are Pelvic Incidence, Sacral Slope and Pelvic Tilt?
Pelvic incidence, sacral slope and pelvic tilt are three measurements taken from your pelvis and the base of your spine. Together they describe the shape and angle of your pelvis, which directly controls the curves of your spine. They can only be measured accurately on a standing, weight-bearing image of your whole body.
Key takeaways
- Pelvic incidence (PI) is a fixed value set by your bone anatomy. It does not change after you stop growing.
- Sacral slope and pelvic tilt are position-dependent. They shift when you stand, sit or lean.
- PI always equals sacral slope plus pelvic tilt. If one changes, the other must compensate.
- A mismatch between PI and lordosis is one of the most common causes of sagittal balance problems.
- These values can only be measured properly on a standing, full-body radiograph.
What do pelvic incidence, sacral slope and pelvic tilt each measure?
Each of the three spinopelvic parameters captures a different aspect of your pelvic geometry. They work as a linked trio: change one, and the others must adjust.
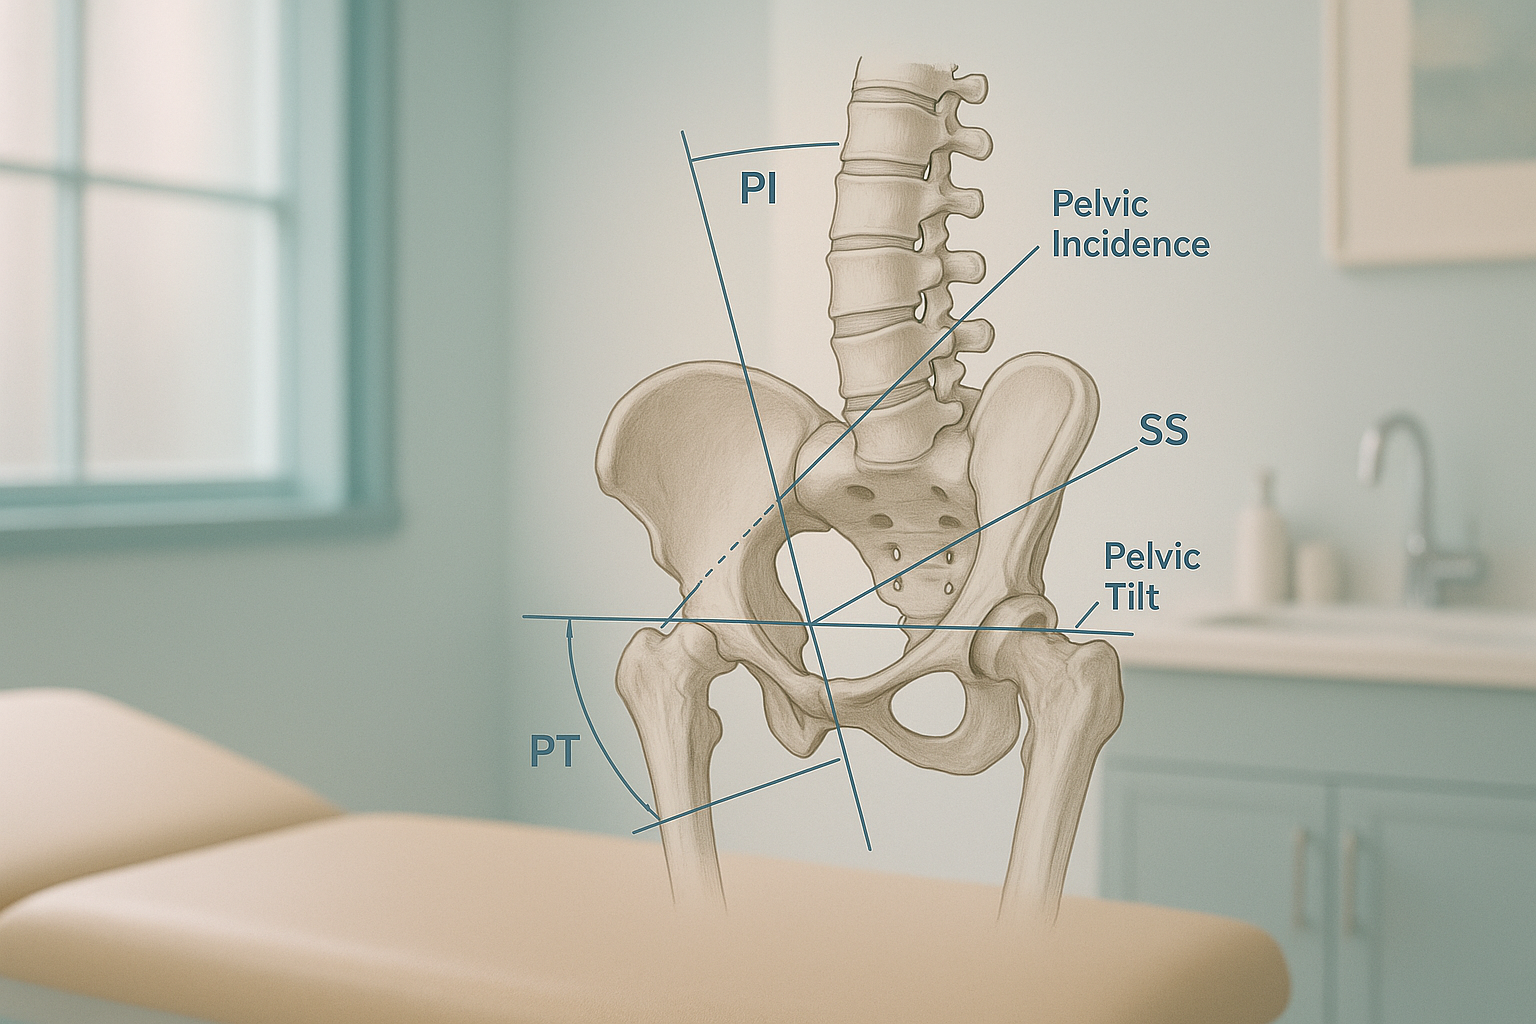
A fixed anatomical value that describes the overall shape and orientation of your pelvis. It is set by your bone structure and does not change with posture. A higher PI means your body needs a deeper lower-back curve to stay balanced.
The angle at which the top surface of your sacrum (the triangular bone at the base of the spine) tilts forward. A steeper sacral slope usually goes hand-in-hand with a deeper lumbar curve.
The amount the pelvis has rotated backward (retroversion) or forward relative to the hip joints. Your body adjusts pelvic tilt to compensate when the spine loses its natural curves.
Because PI is fixed and equals sacral slope plus pelvic tilt, your body can only redistribute the balance between the other two. If the sacral slope drops (the sacrum becomes more horizontal), the pelvic tilt must increase. This is exactly what happens when someone develops flatback syndrome: the pelvis tilts backward to keep the head over the feet.
Why do spinopelvic parameters matter for back pain?
Spinopelvic parameters matter because they dictate the size and shape of every curve above the pelvis. Your spine is a chain. The pelvis is its foundation. If the foundation is steeply angled (high PI), the lumbar spine must curve more to compensate. If the curves do not match the pelvis, the whole chain falls out of sagittal balance, and muscles, joints and discs take extra strain.
Many people with persistent low back pain, hip pain or difficulty standing upright have a mismatch between these values. The pain they feel in the lower back, hips or even the knees is often the result of compensation, not a problem at the painful spot itself. Understanding the pelvis is frequently the key to understanding the pain.
What is a PI-LL mismatch and why does it cause problems?
A PI-LL mismatch occurs when pelvic incidence and lumbar lordosis are not well matched. In a balanced spine, the depth of the lumbar curve should closely follow the pelvic incidence value. When lordosis is significantly less than PI, the body's centre of gravity shifts forward.
To keep your head over your feet, your body compensates. It may tilt the pelvis backward (increased pelvic tilt), flatten the mid-back, bend the knees, or tighten the hip extensors. You might feel this as:
- Difficulty standing upright for more than a few minutes
- A constant feeling of falling forward
- Aching in the lower back, buttocks or backs of the thighs
- Fatigue after walking short distances
PI-LL mismatch is one of the most studied indicators in spinal surgery planning. Surgeons rely on this relationship to decide how much correction is needed and where. Without accurate spinopelvic numbers from a standing image, surgical plans can miss the target.
How are pelvic incidence and sacral slope measured accurately?
Accurate measurement requires a standing, full-length radiograph that captures the spine, pelvis and hips in a single weight-bearing image. When you lie down for a standard X-ray, CT or MRI, gravity no longer acts on your spine and pelvis. Muscles relax, curves flatten or shift, and the sacral slope and pelvic tilt values change from their real, functional positions.
Shows real, loaded alignment. With your full body weight pressing through your skeleton, the pelvis, sacral slope and every spinal curve sit in their true functional position. The sagittal parameters captured here reflect exactly what your body deals with during walking and standing. This is the gold-standard method for spinopelvic assessment.
Relaxes muscles and removes gravity. When you lie flat, the pelvis can tip into a neutral position that it never actually adopts in daily life. Sacral slope and pelvic tilt readings may look normal even when there is a significant standing mismatch. This is why lying-down imaging alone can underestimate alignment problems.
EOS technology captures the full skeleton from head to foot in a single standing exposure, using about 90% less radiation than a standard X-ray, around ten times less. The result is a calibrated image from which all three spinopelvic parameters, plus the sagittal vertical axis and many other alignment values, can be measured together. ScanAlign standing EOS imaging provides exactly this type of assessment at 19 Harley Street, London.
Want to know whether your spinopelvic alignment explains your symptoms? A radiographer can walk you through the process.
Book a free video consultationWhat are the signs that your spinopelvic alignment may be off?
You cannot feel your pelvic incidence directly. But you can often feel the consequences of a mismatch between your pelvis and your spine. Common signs include:
Difficulty standing up straight, especially after sitting or walking.
Pain that doesn't improve despite standard treatment and normal MRI findings.
Pain in the hips, knees or thighs from compensating for poor spinal balance.
If any of these sound familiar and previous scans have not explained the cause, a full standing alignment assessment may reveal what has been missed.
When MRI is the better choice: EOS shows bones, joints and alignment under load. For soft-tissue problems such as disc herniations, nerve compression or ligament injuries, MRI is usually the better tool. In many cases both types of imaging work together to give the full picture.
Who should have their spinopelvic parameters measured?
A standing spinopelvic assessment is most useful for people whose symptoms suggest an alignment or balance problem rather than a single structural injury.
- Have chronic lower back pain with no clear cause on lying-down scans
- Are considering or planning spinal surgery
- Have had spinal surgery and still feel unbalanced
- Struggle to stand upright or walk without fatigue
- Have been told you have a flat back or loss of lordosis
- Sudden numbness or weakness in your legs
- Loss of bladder or bowel control
- Sudden severe pain after an injury
These may be emergencies. Contact your GP, call 111 or go to A&E.
Frequently asked questions
No. Pelvic incidence is determined by your bone anatomy and becomes fixed once you reach skeletal maturity. It does not change with age, exercise or posture. However, the way your body responds to it (through sacral slope and pelvic tilt) can and does change.
Pelvic incidence is a fixed structural measurement that never changes. Pelvic tilt is a position-dependent value that shifts as you stand, sit or lean. Think of pelvic incidence as the shape of the pelvis and pelvic tilt as how the pelvis is currently oriented in space.
Standard X-rays usually image only one region at a time and are often taken lying down. MRI scans are always performed lying flat. Both remove the effect of gravity. A standing full-body image captures the pelvis and spine under real weight-bearing load, giving accurate sacral slope and pelvic tilt readings alongside the fixed pelvic incidence.
It means the natural inward curve of your lower back (lumbar lordosis) does not match the shape your pelvis expects. When the curve is too flat for your pelvis, your body's centre of gravity shifts forward and other areas have to compensate, which can cause pain and fatigue.
No. ScanAlign is a private, self-pay clinic. You can refer yourself directly. Many people book after discussing their needs in a free video consultation with our radiographer.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. The scan takes only a few seconds while you stand still in the machine. It is one of the lowest-dose skeletal imaging methods available.
Pricing details are available on the book a standing spine and pelvis scan page. You can also discuss costs during a free video consultation before committing.
Yes. Surgeons increasingly rely on standing spinopelvic parameters to plan corrections. Knowing your exact pelvic incidence, sacral slope and pelvic tilt helps them determine the right amount of correction so the spine and pelvis work together after surgery.
You stand naturally inside the EOS machine at 19 Harley Street. Two low-dose beams capture front-to-back and side views in a single pass that takes just a few seconds. There is no enclosed tunnel, no injection and no need to change into a gown in most cases.
Your report will include your spinopelvic measurements alongside a clear explanation written by a specialist radiographer. If you are sharing the report with a surgeon or physiotherapist, they will have the precise values they need for planning.
Understand your alignment before your next step
Whether you are exploring why you hurt, preparing for a surgical opinion, or reviewing a previous procedure, a standing spinopelvic assessment provides the numbers that matter.
Book a free video consultationSources
- Legaye J, Duval-Beaupère G, Hecquet J, Marty C. Pelvic incidence: a fundamental pelvic parameter for three-dimensional regulation of spinal sagittal curves. European Spine Journal. 1998;7(2):99-103.
- Schwab F, Patel A, Ungar B, Farcy J-P, Lafage V. Adult spinal deformity: postoperative standing imbalance. How much can you tolerate? An overview of key parameters in assessing alignment and planning corrective surgery. Spine. 2010;35(25):2224-2231.
- Roussouly P, Pinheiro-Franco JL. Biomechanical analysis of the spino-pelvic organization and adaptation in pathology. European Spine Journal. 2011;20(Suppl 5):609-618.
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.