
What Is a Periacetabular Osteotomy (PAO) for Hip Dysplasia?
A periacetabular osteotomy (PAO) is a hip preservation operation for adults with hip dysplasia. The surgeon carefully cuts and repositions the hip socket so it covers the ball of the thigh bone more fully. This improves joint stability, reduces pain, and can delay or prevent the need for a hip replacement later in life.
Key takeaways
- PAO repositions the hip socket to improve coverage of the femoral head, preserving your own joint.
- It is most suitable for younger adults whose hip joint cartilage is still in reasonable condition.
- Accurate pre-operative imaging of the pelvis under load helps the surgeon plan the correction.
- Recovery is gradual and typically involves several months of protected weight-bearing.
- EOS standing imaging shows your pelvis and hip alignment as it truly is when you are upright.
How does a periacetabular osteotomy work?
A PAO works by reshaping the position of your hip socket (the acetabulum) so it sits more securely over the top of the thigh bone. In hip dysplasia in adults, the socket is too shallow. That means the ball of the hip joint is not properly contained, leading to instability, labral tears, and eventually arthritis.
During surgery, the surgeon makes precise cuts around the acetabulum, freeing it from the rest of the pelvis. They then rotate the socket into a better position and fix it with screws. Your own bone and cartilage stay in place. This is why it is called a hip preservation procedure, because it keeps your natural joint.
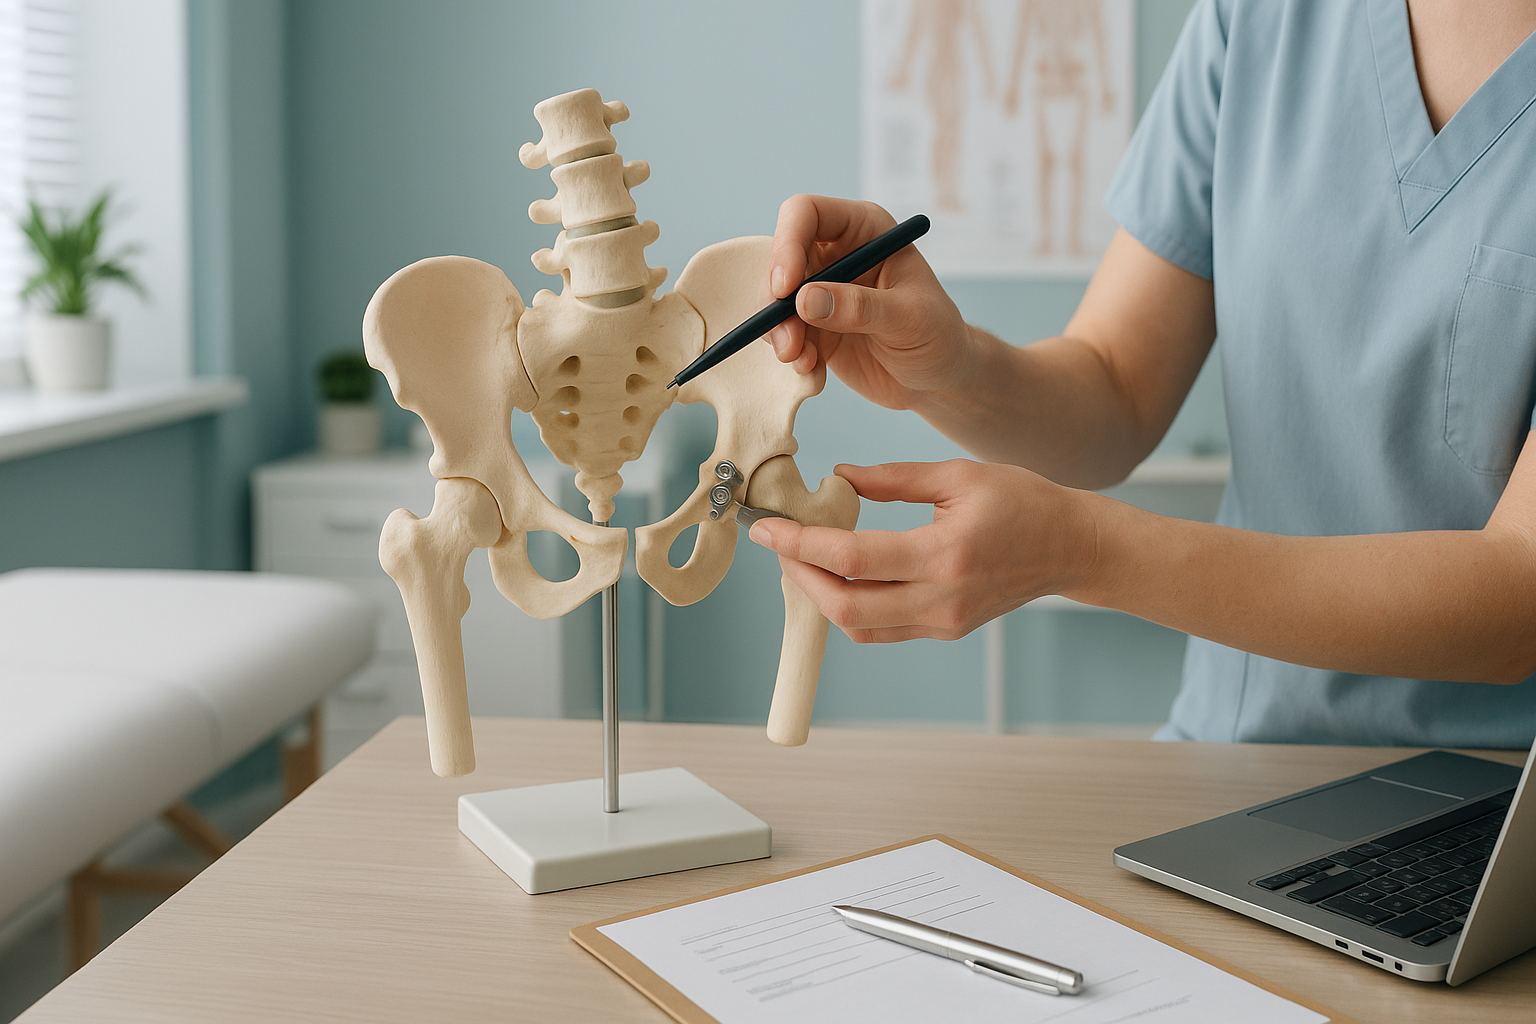
The operation is sometimes called a Ganz osteotomy after the Swiss surgeon who developed the modern technique. It is a major procedure, but for the right patient it can be life-changing, offering years of improved function on your own hip joint.
What symptoms suggest you might need a PAO?
Most people being considered for a periacetabular osteotomy have been living with hip dysplasia, sometimes without knowing it, for years. Symptoms tend to build gradually.
A deep ache in the groin or front of the hip, often worse after walking or sitting for a long time.
A sensation of the hip catching or giving way, which may indicate a labral tear from the instability.
Difficulty keeping up with exercise, sport, or everyday activities you used to manage without pain.
A feeling of tightness or limited range, particularly when rotating the hip inward or bending deeply.
These symptoms can overlap with many other hip problems, which is why accurate imaging is important before any decision about surgery. The condition may be linked to developmental dysplasia of the hip, which sometimes goes undetected until adulthood.
Who is a good candidate for PAO surgery?
A PAO works best for adults whose hip cartilage is still in reasonable condition. The goal is to preserve the joint before arthritis takes hold. It is not suitable for everyone.
- Young adults (typically under 40 to 50) with confirmed hip dysplasia
- Good remaining cartilage on imaging
- Pain or instability not responding to physiotherapy
- Wanting to delay or avoid a hip replacement
- Significant cartilage loss or established arthritis
- Older adults where a replacement may give a better outcome
- Other medical conditions that make major surgery risky
- Hip dysplasia that is very mild and manageable without surgery
The decision is always made by a specialist hip preservation surgeon, not by an imaging clinic. ScanAlign provides the diagnostic images. Your surgeon interprets them and advises you on whether a PAO, a hip replacement, or continued conservative management is the right path.
A note on MRI. EOS shows bones, joints, and whole-body alignment under load. For assessing cartilage, labral tears, or soft tissue around the hip, MRI is usually the better tool. Your surgeon may ask for both types of imaging before planning a PAO.
Why does standing imaging matter before a PAO?
Standing imaging matters because your pelvis behaves differently when you are upright and bearing your full body weight compared with when you are lying down on a scanning table. Standard X-rays and CT scans taken lying flat can relax the muscles and allow the pelvis to shift into a position it does not actually hold during daily life.
A PAO is all about repositioning the socket to the right angle. If the planning images show the pelvis in a relaxed, artificial position, the surgical plan may not match how you actually stand and move. EOS takes a full-length standing image of both hips and the entire pelvis in a single low-dose exposure, using about 90% less radiation than a standard X-ray, around ten times less.
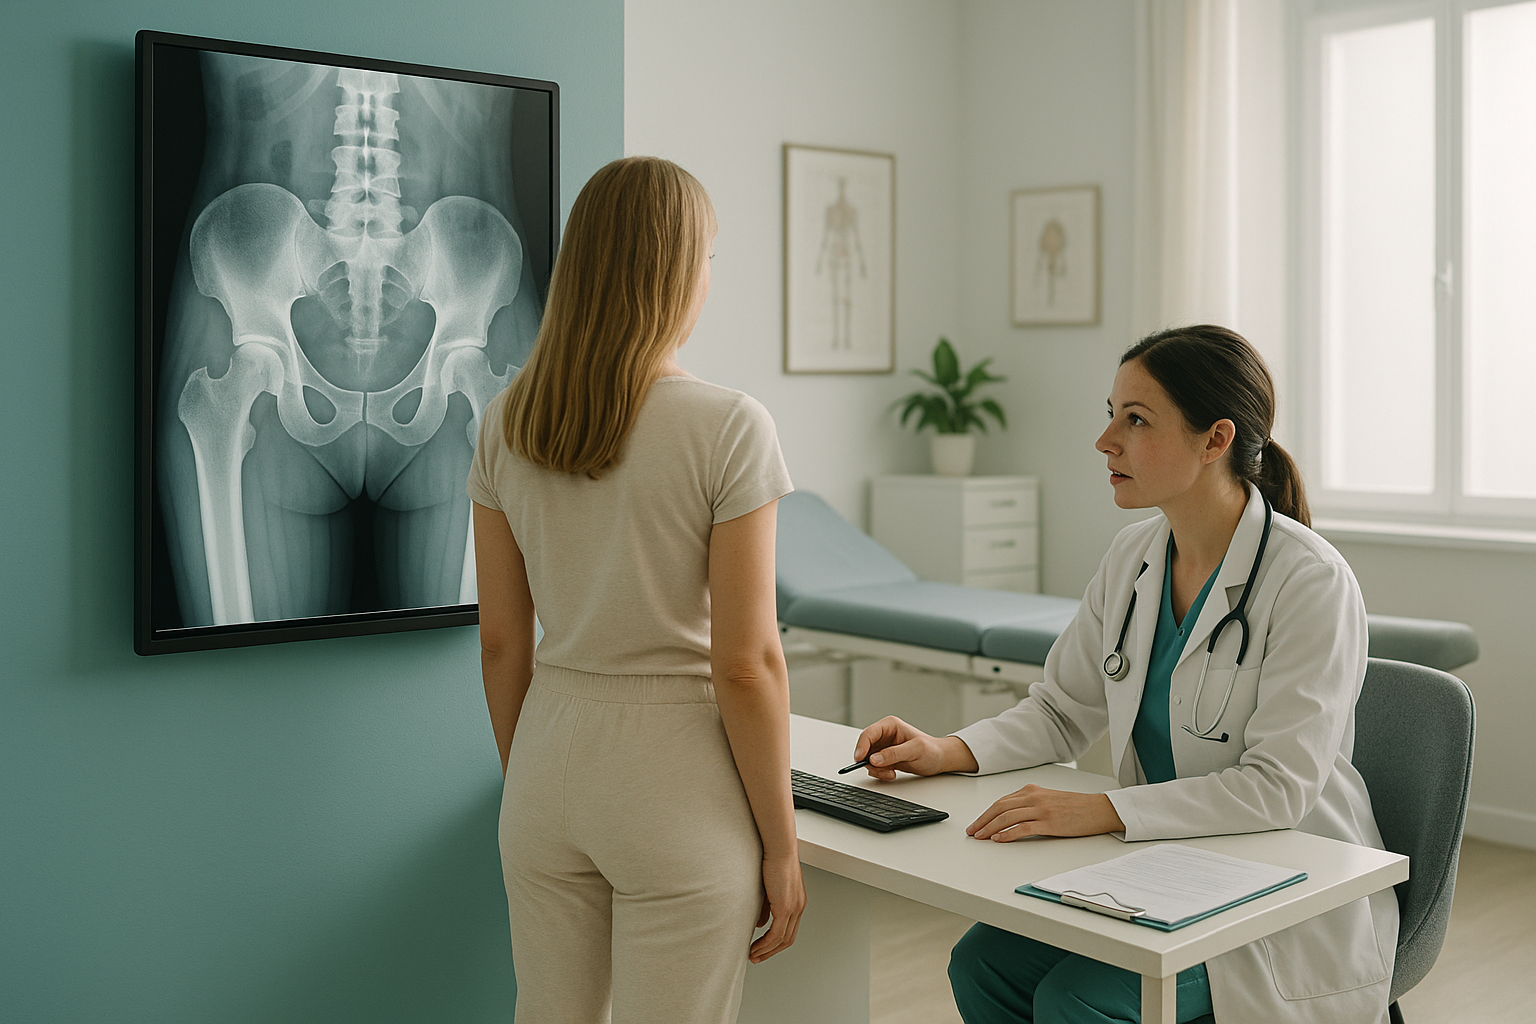
Your body is a connected chain. If your pelvis tilts forward or backward when you stand, the effective coverage of the hip socket changes. A socket that looks adequate lying down might look inadequate standing up, or vice versa. For a procedure as precise as a PAO, that difference matters.
Considering PAO surgery and want standing pelvic imaging to support your surgical planning?
Book a free video consultationWhat does PAO recovery look like?
Recovery from a periacetabular osteotomy is gradual. It is a major operation involving bone cuts and internal fixation, so your body needs time to heal properly.
First weeks
Hospital stay of several days, followed by protected weight-bearing with crutches. Focus is on wound healing and gentle range-of-motion exercises.
Weeks 6 to 12
Gradual return to weight-bearing as the bone heals. Physiotherapy becomes more active, building strength around the hip.
Three to six months
Most people return to everyday activities. Strengthening and mobility work continues. Follow-up imaging may be taken to check bone healing.
Six months onward
Gradual return to sport or higher-impact activities, guided by your surgeon and physiotherapist. Full recovery can take nine to twelve months.
Every patient is different. Your surgeon and physiotherapy team will tailor the timeline to your specific situation. Standing imaging after surgery can show how the correction has changed your alignment under load, giving your team a clear picture of how the hip is settling.
Frequently asked questions about PAO surgery
It is an operation that repositions the hip socket so it covers the ball of the thigh bone more completely. The surgeon cuts around the socket, rotates it into a better angle, and fixes it with screws. It preserves your own joint instead of replacing it.
PAO is most commonly performed on younger adults, often in their twenties or thirties, because they tend to have better cartilage. However, some patients in their forties may still be suitable. The key factor is the condition of the cartilage, not just age alone.
Most people use crutches for around six to twelve weeks. Return to everyday activities usually happens within three to six months. Full recovery, including higher-impact sport, can take nine to twelve months. Your surgeon will guide your individual timeline.
A successful PAO can significantly delay the need for a hip replacement, sometimes by decades. It does not guarantee you will never need one. The outcome depends on factors like cartilage condition at the time of surgery and your activity levels afterwards.
The pelvis tilts differently when you are standing versus lying down. That tilt changes how much the socket covers the femoral head. Standing imaging, such as EOS, shows the true pelvic position under load, helping the surgeon plan the exact correction needed.
EOS uses about 90% less radiation than a standard X-ray, around ten times less. This makes it particularly suitable when multiple images are needed before and after surgery.
No. At ScanAlign, standing EOS imaging in London, you can self-refer. Many patients bring their images to their orthopaedic surgeon afterwards. You can also be referred directly by your consultant or physiotherapist.
Current pricing and packages are listed on our frequently asked questions page. We are a private, self-pay clinic.
Mild arthritis does not automatically rule out a PAO, but moderate to severe cartilage loss usually does. Your surgeon will assess your imaging carefully. In some cases, a hip replacement may be the more predictable option.
Sudden numbness, weakness, or loss of bladder or bowel control are red-flag symptoms. Do not wait for a scan. Contact your GP, call 111, or go to A&E immediately for urgent medical attention.
Considering PAO surgery?
Standing pelvic imaging can give your surgeon a clearer picture of your hip alignment under real weight-bearing conditions. Start with a free video consultation to find out whether EOS imaging could support your surgical planning.
Book a free video consultationWritten by Abbas Dhami (Specialist Diagnostic Radiographer)
Sources
- Ganz R, Klaue K, Vinh TS, Mast JW. A new periacetabular osteotomy for the treatment of hip dysplasias. Clinical Orthopaedics and Related Research. 1988;(232):26-36.
- Clohisy JC, Schutz AL, St John L, Schoenecker PL, Wright RW. Periacetabular osteotomy: a systematic literature review. Clinical Orthopaedics and Related Research. 2009;467(8):2041-2052.
- International Hip Dysplasia Institute. Adult Hip Dysplasia: Information for Patients. hipdysplasia.org.
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.