

What Is the Q Angle, and Does It Really Explain Knee Pain?
The Q angle (quadriceps angle) measures the direction of pull your thigh muscle exerts on the kneecap. It has been used for decades to explain front-of-knee pain, especially in women. However, research now shows that a single static number is a poor predictor of pain. Whole-body standing alignment gives a far more complete picture.
Key takeaways
- The Q angle measures how your quadriceps pull on the kneecap, from hip to knee to shin.
- It has been widely used but is not a reliable predictor of knee pain on its own.
- Hip rotation, femoral version and overall alignment matter more than a single angle.
- Standing, weight-bearing imaging reveals alignment issues that lying-down scans hide.
- EOS imaging captures the full chain from feet to hips in one low-radiation scan.
What is the Q angle and how is it measured?
The Q angle is the angle formed between two imaginary lines. The first runs from the bony point at the front of your hip (the ASIS) down to the centre of your kneecap. The second runs from the centre of your kneecap down to the bump at the top of your shin (the tibial tuberosity). Where those two lines meet at the kneecap, they form the quadriceps angle.
Clinicians have traditionally measured this with a protractor while the patient lies flat or stands still. The idea is simple: a larger angle means the quadriceps pull the kneecap outward more forcefully, which could lead to poor patellar tracking and front-of-knee pain.
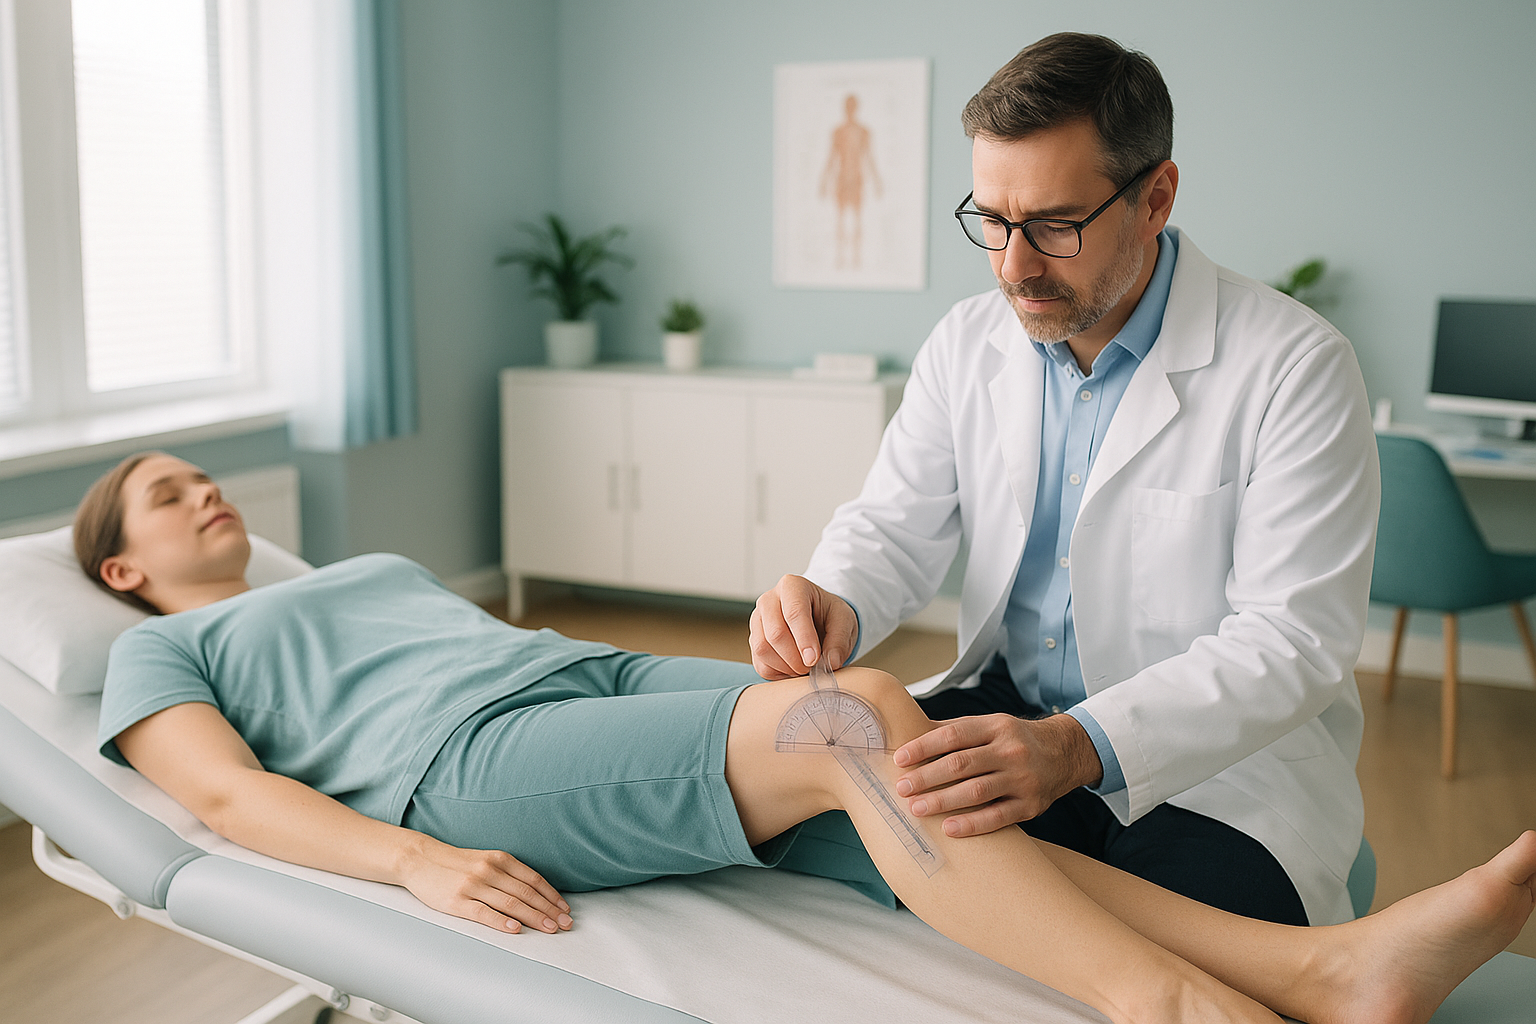
Textbooks often cite a "normal" range that is somewhat higher in women than in men, largely because of wider pelvis proportions. For years, a higher Q angle was used to explain why women experience more front-of-knee pain. That assumption is now being seriously questioned.
Why is the Q angle considered unreliable for diagnosing knee pain?
The Q angle is considered unreliable for several well-documented reasons. It is a static measurement taken in one position, yet knee pain usually happens during movement. Research has found that the same person can produce noticeably different Q angle readings depending on whether they are lying down, standing, or being measured by different clinicians.
Perhaps the biggest problem is that the Q angle ignores everything above and below the knee. Your hip rotation, femoral version (whether the thighbone twists inward or outward more than usual), foot posture and trunk alignment all influence how force passes through the kneecap. A single number at the knee cannot capture that complexity. To understand how the thighbone's twist affects knee loading, read about anteversion versus retroversion.
What actually causes front-of-knee pain if not the Q angle?
Front-of-knee pain is usually the result of several factors working together, not a single measurement. The body works as a connected chain from feet to hips. When alignment is off at one level, another area compensates, and the kneecap often bears the cost.
These factors often combine to produce patellofemoral pain syndrome, one of the most common causes of front-of-knee pain. Focusing only on the Q angle risks missing the real driver.
How does standing imaging show what the Q angle misses?
Standing, weight-bearing imaging reveals the alignment your body actually works with. When you lie down for a conventional X-ray or MRI, gravity is removed, muscles relax, and joints settle into positions they never hold in real life. A tilted pelvis may flatten out. A rotational twist through the leg may disappear. The result is an image that looks more normal than reality.
What it captures: Full leg alignment from hips to ankles under your actual body weight. Pelvic tilt, rotation through the femur, knee alignment, and foot position are all visible in one image.
An EOS scan uses about 90% less radiation than a standard X-ray, around ten times less. ScanAlign standing EOS imaging captures the whole picture in seconds while you stand naturally.
What it misses: When you lie flat, gravity no longer loads the joints. A leg-length difference, a subtle pelvic tilt, or a rotational alignment problem may all straighten out and look normal on the resulting image.
This is the main limitation of measuring the Q angle on a lying-down examination. The number you get may not reflect what is happening when you stand and walk.
When MRI is the better tool: EOS shows bones, joints and alignment. For soft-tissue problems such as cartilage damage behind the kneecap, ligament tears, or nerve irritation, MRI is usually the better choice. Your clinician can advise which scan you need.
Who should consider a standing alignment scan instead of relying on Q angle?
Anyone whose front-of-knee pain has not improved after physiotherapy or whose imaging so far has only looked at the knee in isolation should consider a full standing assessment. The goal is to see whether the knee is compensating for a problem elsewhere in the chain.
- Persistent front-of-knee or kneecap pain
- Previous scans showed "nothing wrong" but pain continues
- Told your Q angle is high but not offered further investigation
- Knee pain that worsens with stairs, squatting or running
- Sudden knee locking or giving way (see your GP promptly)
- Suspected ligament or meniscus tear (MRI is usually needed first)
- Acute injury with significant swelling
Not sure whether a standing alignment scan is right for your knee? Talk it through at no cost.
Book a free video consultationFrequently asked questions about the Q angle and knee pain
Textbooks typically describe a range that is somewhat higher in women than in men, reflecting wider pelvis proportions. However, there is a lot of natural variation, and the number on its own does not reliably predict whether someone will have knee pain.
Not necessarily. Large studies have found no consistent link between a higher Q angle and knee pain. Other factors, including hip strength, femoral version and dynamic movement patterns, play a much bigger role.
Women generally have a wider pelvis relative to their height, which increases the angle between the hip and the kneecap. This anatomical difference is normal and does not automatically mean greater risk of knee problems.
The Q angle is largely determined by bone structure, so exercise will not change the angle itself. However, strengthening the hips and improving movement patterns can significantly reduce the abnormal forces that cause kneecap pain, which is usually more important than the angle.
Some clinicians still measure it as one of many data points, but it is rarely used as a standalone diagnostic tool. Modern practice places far more emphasis on hip strength testing, dynamic movement analysis and whole-limb alignment imaging.
Patellar maltracking means the kneecap does not glide smoothly in its groove during movement. A high Q angle was once thought to be the main cause, but we now know maltracking can happen regardless of Q angle, often driven by hip control and soft-tissue balance. Read more about patellar maltracking.
An EOS scan captures the full skeleton from feet to hips (or higher) while you stand. This shows true weight-bearing alignment, including leg rotation, pelvic tilt and joint spacing, all in one image with about 90% less radiation than a standard X-ray, around ten times less.
No. ScanAlign is a self-referral clinic. You can book a measured alignment scan directly without a GP letter.
Yes. EOS uses about 90% less radiation than a standard X-ray, around ten times less. It is one of the lowest-dose skeletal imaging systems available.
ScanAlign is a private, self-pay clinic. You can start with a free video consultation to discuss whether a scan is right for you. The consultation is at no cost and with no obligation.
See the full picture, not just one angle
A free video consultation lets you discuss your knee pain with a specialist radiographer and find out whether a standing alignment scan could help.
Book a free video consultationSources
- Smith TO, et al. "The Q angle: a systematic review." The Knee. 2011;18(3):166-171. PubMed.
- Powers CM. "The influence of abnormal hip mechanics on knee injury: a biomechanical perspective." Journal of Orthopaedic & Sports Physical Therapy. 2010;40(2):42-51.
- NHS. "Knee pain." nhs.uk. Accessed 2024.
Written by Abbas Dhami (Specialist Diagnostic Radiographer)
This page is general information and not a diagnosis.
ScanAlign is the trading name of CoreMed Solutions Ltd and operates under The Harley Street Hospital's CQC licence.